Categories
Uncategorized

Pharmacology Basics for the IV Technician: What You Must Know

Pharmacology Basics for the IV Technician: What You Must Know

Nancy Kimmel, MSN, FNP, RN, PhD CHMM, MSN-FNP-BC — National IV Association

Introduction: Why IV Pharmacology Matters for the IV Technician

Intravenous (IV) therapy is a cornerstone of modern medical care — used for blood collection, chemotherapy, immunosuppressant delivery, vitamin therapy, fluid resuscitation, and continuous medication infusions. As an IV technician, your work directly affects systemic physiology because fluids and medications introduced intravenously circulate rapidly throughout the vascular compartment. Small errors can therefore produce large, immediate consequences: systemic infections, tissue necrosis from extravasation, air embolism, fluid overload, or life‑threatening arrhythmias.

This article provides a comprehensive pharmacology foundation tailored to the IV technician, with practical clinical guidance, detailed anatomy and insertion technique, medication and fluid principles, complications and monitoring, legal/professional responsibilities, and teaching strategies for instructors. It is written for student nurses, nurses, anesthesia techs, veterinary techs, and dentists involved with IV access and management.

Scope and Audience

This content is intended for allied health personnel responsible for IV access or assisting with infusion therapy: student nurses, nurses, anesthesia techs, veterinary techs, and dentists. It is not a replacement for institutional policies or prescriber orders. Always work within your facility’s protocol and your defined scope of practice. Medical assistants and other non‑licensed personnel must consult supervisors or licensed clinicians before performing tasks outside their authorized scope. If you lack knowledge or comfort with a task, admit it and seek supervision — patient safety depends on that honesty.

Anatomy and Tissue Planes Traversed During IV Insertion

Understanding the layers the needle passes through and the venous wall structure is essential to safe cannulation and minimizing complications.

Surface Layer Description
Epidermis The outermost skin layer; barrier to microbes. Requires proper skin antisepsis prior to insertion.
Dermis Contains blood vessels, nerves, and connective tissue; local pain receptors are dense here.
Hypodermis (Subcutaneous Tissue) Fat layer with variable thickness; the needle traverses this to reach superficial veins.
Venous Tunica Vein wall layers (intima, media, adventitia). Proper needle angle and control help entry into the lumen without transfixion.

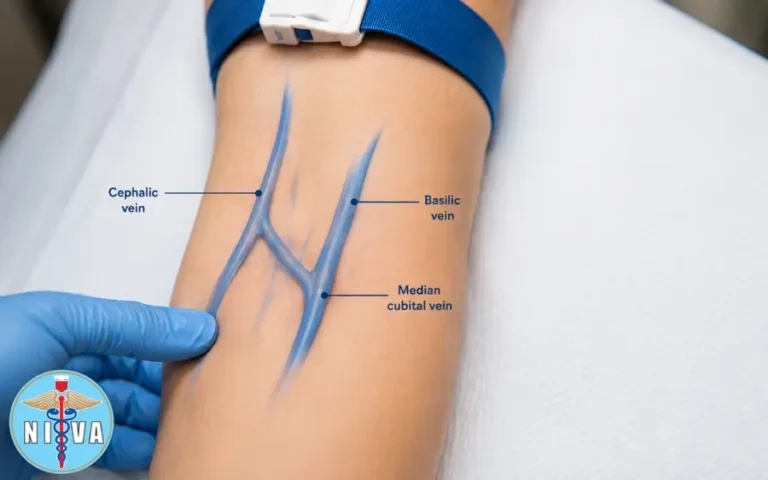
Common peripheral veins for cannulation include the cephalic, basilic, and median cubital veins within the antecubital fossa. Trace the vein for at least an inch proximally and distally to identify a straight segment for cannulation. Avoid hands and lower extremities except when necessary, and avoid lower extremities particularly in patients with diabetes or peripheral vascular disease due to increased risk of complications.

IV Insertion Technique and Asepsis: The Pharmacokinetic Gateway

IV therapy is effective because it bypasses absorption barriers — but that also removes many of the body’s protective checks. Therefore, meticulous aseptic technique is mandatory.

  • Perform a targeted assessment and obtain physician authorization for IV placement and specific therapies (e.g., chemotherapy, immunosuppressants, vitamin therapy).
  • Skin antisepsis: chlorhexidine is preferred when not contraindicated. Clean the site with 0.5%–2% chlorhexidine with appropriate alcohol concentration; allow at least 30 seconds to 1 minute of contact time per institutional policy. A one‑minute scrub is commonly taught and effective to reduce skin flora. Do not touch the site after antisepsis.
  • Needle angle: advance the catheter at a 15°–28° angle with the bevel up to enter the vein smoothly. Lower the angle as the flashback appears to thread the catheter into the lumen.
  • Flashback: a visual indicator of venous entry. Once seen, do not advance forcefully — advancing too far risks perforation and transfixion. If you feel a “give” then a sudden lack of resistance and see flashback, lower the angle and advance the catheter slightly while stabilizing the skin.
  • Do not “push too hard” — moving through the vein means the catheter or needle may transect the posterior wall causing infiltration, hematoma, or failure of the device.
  • When flushing after placement, resistance indicates the catheter is not fully intraluminal — stop, do not force a flush, and reassess line position.

Practical insertion checklist

  • Confirm order/indication and allergies; verify patient identity.
  • Gather supplies; perform hand hygiene and don gloves.
  • Apply antiseptic (chlorhexidine) and allow full contact time (≈1 minute).
  • Use appropriate gauge catheter for therapy (table below).
  • Insert bevel up at 15°–28°; watch for flashback; stabilize and advance catheter.
  • Secure catheter, label with time, gauge, and insertion site.
  • Document per institutional policy: time placed, gauge, site, patient response, and any special instructions.
Catheter Gauge Typical Use
14–16G Major trauma, rapid transfusion, surgery
18G CT contrast, blood transfusion, most adult infusions
20G General IV therapy, most medications
22–24G Pediatrics, elderly with fragile veins, routine maintenance

Pharmacology Principles for IV Administration

IV administration is distinct pharmacokinetically and pharmacodynamically from other routes. Key principles every IV technician should understand:

  • Onset and bioavailability: IV administration delivers 100% bioavailability with immediate onset of action. This makes timing and dose accuracy critical.
  • Volume of distribution: intravenous drugs distribute into vascular and extravascular compartments depending on their physicochemical properties; some stay mainly intravascular (e.g., albumin-bound drugs) while others diffuse into tissues.
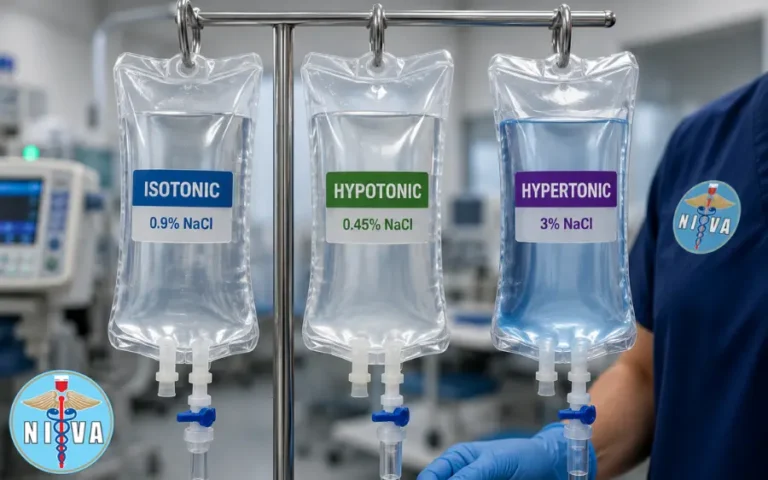
  • Concentration and tonicity: the tonicity of IV fluids (isotonic, hypertonic, hypotonic) has immediate effects on intravascular volume and cellular fluid shifts.
  • Compatibility: many drugs are incompatible with specific IV fluids or other drugs when mixed; never assume compatibility — check concentration charts or pharmacy resources.
  • Label reading: always read the medication label before administration. Simple errors (e.g., saline vs. atropine vs. lidocaine) lead to catastrophic outcomes. Verify the medication, dose, route, and expiry.

Isotonic, Hypertonic, and Hypotonic Solutions

Solution Type Common Examples Physiologic Effect Clinical Use
Isotonic 0.9% NaCl (Normal Saline), Lactated Ringer’s Osmolarity approximates plasma; no net fluid shift across cell membranes. Normal blood pH ranges 7.35–7.45; isotonic fluids should not substantially alter blood pH. Volume resuscitation, maintenance fluid in many settings
Hypertonic 3% NaCl, high‑concentration dextrose solutions Pulls water into the vascular compartment from cells and interstitium via osmotic gradient. Treat cerebral edema, reduce edema. Use with caution—risk of fluid overload and hypernatremia; contraindicated in CHF without close monitoring.
Hypotonic 0.45% NaCl (half‑normal saline) Drives water out of the vascular system into the interstitial and intracellular spaces; can worsen edema. Treat intracellular dehydration, hyperosmolar states. Not appropriate for patients at risk for increased intracranial pressure or hypovolemia without careful monitoring.

Because hypertonic solutions draw fluid into the vascular space, they can precipitate circulatory overload in patients with compromised cardiac function, potentially leading to acute respiratory distress and code blue situations. Always consider patient comorbidities such as CHF before initiating hypertonic therapy.

Drug Categories Frequently Administered via IV

IV technicians will encounter a variety of medication classes. Below is a non‑exhaustive list with nursing/technical considerations.

Medication Class Examples Key IV Considerations
Analgesics Opioids (morphine), NSAIDs (ketorolac) Monitor for respiratory depression, hypotension; titrate slowly per order.
Antiemetics Ondansetron Watch ECG changes at high doses (QT prolongation).
Antibiotics Vancomycin, ceftriaxone Infusion rate matters (vancomycin red man syndrome). Follow recommended infusion times.
Vasoactive Agents Norepinephrine, dopamine, epinephrine Require close monitoring; extravasation can cause severe tissue injury—use central lines when indicated and follow extravasation protocols.
Chemotherapeutics Cisplatin, doxorubicin Vesicants vs irritants classification is essential. Specialist authorization and usually central venous access needed. Strict safety handling and disposal per oncology protocols.
Immunosuppressants Cyclosporine, tacrolimus (IV formulations require monitoring) Therapeutic drug monitoring often required. Careful labeling and infusion rates.
Anesthetics/Local Lidocaine (IV for arrhythmias or topical infiltration) Systemic toxicity (CNS, cardiac) with overdosing. Pay attention to concentration and total dose.
Anticholinergics Atropine Used for bradycardia; watch for tachycardia and anticholinergic effects.

Always be aware of look‑alike/sound‑alike drug names. The simple instruction “read the label” cannot be overstated. Distinguish saline from atropine and lidocaine visually and by checking the label and concentration before connecting to a patient. When in doubt, stop and ask. For students or medical assistants, confirm with a supervising nurse or pharmacist.

Infusion Rates, Rapid Infusion Risks, and Clinical Monitoring

Infusion rate determines the rate of pharmacologic effect and fluid redistribution. Rapid infusions in fragile patients can precipitate acute decompensation.

  • Rapid infusion risks: cardiovascular overload (manifested as sudden increase in heart rate and blood pressure, shortness of breath, hypoxia), pulmonary edema, and decompensation leading to code blue events. Monitor vital signs before, during, and after rapid infusions, especially in elderly patients or those with preexisting cardiac or renal disease.
  • Signs of fluid overload: increased jugular venous pressure, crackles on lung auscultation, peripheral edema, rising respiratory rate, desaturation. Notify licensed clinician immediately on detection.
  • When administering IV boluses or rapidly infusing large volumes, use infusion pumps when available to control rate precisely. Gravity infusions are imprecise and risk overinfusion.

Example monitoring parameters

  • Baseline vitals before administering large boluses or vasoactive drugs.
  • Continuous pulse oximetry when indicated.
  • Frequent assessment of infusion site and patient tolerance (every 1–5 minutes during acute boluses, then per policy).

Remember: if a patient develops increased heart rate, increased blood pressure, shortness of breath, or low oxygen saturation during infusion, suspect cardiovascular overload or anaphylaxis depending on context, and initiate emergency protocols while calling for immediate clinical support.

Complications: Recognition, Immediate Actions, and Prevention

Complication recognition is a critical skill for IV technicians. The window for intervention can be short.

Infiltration and Extravasation

Infiltration is leakage of non‑vesicant fluid into surrounding tissues. Extravasation is leakage of vesicant/irritant medication that can cause tissue necrosis.

  • Signs: swelling, pallor, pain, cool or blanched skin, absence of blood return, resistance on flush.
  • Immediate steps: stop infusion, disconnect tubing, aspirate residual medication from catheter if possible, elevate limb, notify clinician, and follow facility extravasation protocol which may include antidote administration.
  • Prevention: choose appropriate catheter size and site, confirm blood return before administration, use central access for vesicant drugs when indicated.

Infection and Phlebitis

  • Local infection and phlebitis: erythema, warmth, tenderness, purulent drainage. Systemic catheter-related bloodstream infections (CRBSI) may present with fever or sepsis.
  • Prevention: strict asepsis on insertion and dressing changes; chlorhexidine skin prep with appropriate contact time; avoid touching the site after antisepsis; replace dressings per policy.
  • Documentation: chart time, gauge, location, dressings applied, and patient response — these records are legal protection and continuity of care.

Air Embolism

Air introduced into the venous system can travel to the pulmonary circulation and is life‑threatening. Prevention includes priming tubing properly, clamping catheters when disconnected, and using air detection on infusion pumps or closed systems.

Resistance on Flush

If you experience resistance on flush, stop. Resistance suggests extraluminal placement or a kinked catheter. Do not force the syringe; forcing can cause catheter rupture or tissue damage. Reassess, consider removal, and notify the supervising clinician.

Blood Draws from Lines and Timing after Medication Doses

Lines that have been used to infuse medications require caution before drawing blood samples. Some medications may contaminate samples and lead to inaccurate laboratory results.

  • Follow institutional policy for drawing blood from catheterized limbs or ports. Many facilities recommend drawing from a peripheral site when the line has recently been used for medication infusion.
  • After a medication‑dosed IV infusion, allow an appropriate dwell/flush and time before drawing blood if using the same line — check pharmacy or laboratory protocol for specific recommended wait times. Some agents require conservatively waiting several minutes after a saline flush and using discard volumes before sampling; others require peripheral venipuncture only.
  • Do not apply a tourniquet on an arm that has an active IV or an infusion running without specific direction — tourniquets may distort flow and dislodge catheters or concentrate local drug exposure.

Geriatric Considerations: NCAD, NIA, and Age-Specific Pharmacology

Older adults have physiologic changes that alter pharmacokinetics and increase risk during IV therapy: decreased cardiac output, reduced renal and hepatic clearance, altered body composition (less lean mass, more adipose), and fragile skin/veins. Integrate evidence and resources from the National Center for Aging and Development (NCAD) perspective and the National Institute on Aging (NIA) for geriatric best practices.

  • Venous fragility: consider smaller gauges (22–24G), use of stabilization devices, and more gentle tourniquet application.
  • Dosing adjustments: many drugs require dose reductions or slower titration due to decreased clearance. Monitor for accumulation and adverse effects.
  • Fluid balance: elderly patients are susceptible to both dehydration and fluid overload. Tonicity selection requires consideration of cardiovascular status.
  • Skin antisepsis: allow appropriate contact time for chlorhexidine; be mindful of fragile skin when securing dressings.

Use NIA resources for geriatric assessment and medication management strategies: NIA. For aging and development educational frameworks, reference NCAD principles in individualized care planning.

Charting, Legal Documentation, and Professional Responsibility

Charting is not administrative fluff — it is legal protection and a clinical communication tool. Accurate documentation should include time of insertion or intervention, catheter gauge and device type, insertion site, any immediate complications or patient symptoms, and the patient’s response to procedure or medications. Document any patient education provided and the name and role of the person performing the procedure.

Key documentation elements:

  • Time and date of insertion or medication administration.
  • Gauge, catheter type, and insertion site with laterality (e.g., “right cephalic vein, forearm”).
  • Medication name, dose, infusion rate, and route.
  • Patient response and any adverse events.
  • Name and credentials of the person performing the procedure.

For student nurses and novice practitioners, charting thoroughly and accurately demonstrates competent practice and provides defense in legal or disciplinary proceedings. When in doubt, chart the facts and immediate supervisor notifications.

Scope of Practice, Supervision, and Ethics

Every IV technician must function within their defined scope. Medical assistants and other trainees should consult supervisors for tasks that are beyond their training.

  • Admit when you lack knowledge. Seeking supervision is an ethical duty and patient safety imperative.
  • When a physician’s authorization is required (e.g., chemotherapy, immunosuppressants), ensure appropriate orders are present before initiating therapy.
  • Never administer medication or perform procedures contraindicated by your license or facility policy.

Special Populations: Pediatrics, Oncology, and Veterinary Considerations

Pediatrics: smaller vessels and lower circulating volume demand smaller gauge catheters and precise dosing. Use appropriate dilution and infusion rates. Pediatric patients may require topical anesthetics, distraction, or sedation strategies. Always verify pediatric dose calculations independently.

Oncology: many chemotherapeutic agents are vesicants or severe irritants. Central venous access (ports, PICCs) is preferred for some agents. Strict safe handling, PPE, and waste disposal are required. Verify drug classification (vesicant vs irritant) before peripheral administration.

Veterinary techs: animal IV access requires familiarity with species‑specific anatomy and behavior. Positioning and stabilization differ, and many drugs used systemically in animals have different dosages and safety profiles. Veterinary techs should coordinate with veterinarians for dosing and access decisions.

Instructor Guidance: Preparing the Next Generation

For instructors teaching IV therapy and pharmacology, success requires preparation, passion, and patience. Managing classroom dynamics and ensuring safe skill acquisition demands a structured approach.

  • Preparation: create clear learning objectives, competency checklists, and simulation scenarios. Ensure clinical partners and preceptors understand performance expectations.
  • Passion: model professional behavior and emphasize the clinical reasoning behind steps, not just the steps themselves. Enthusiasm improves retention and instills professional pride.
  • Patience: learners acquire psychomotor skills at different rates. Provide constructive feedback, deliberate practice, and progressive complexity in scenarios.
  • Classroom dynamics: manage risk by maintaining low student-to-instructor ratios for hands‑on skills. Use simulation to replicate rare but critical complications (e.g., air embolism, extravasation). Encourage peer observation and reflection.
  • Continuous learning: stay current with guidelines from the CDC, NIH, and other authorities and integrate evidence into curricula.

Recommended institutional and national resources for instructors and clinical educators include the CDC and NIH guidance on infection prevention and medication safety: CDC, NIH, and drug information via the National Library of Medicine: NLM.

Erikson’s Psychosocial Development: Applying Adult and Pediatric Developmental Principles to Teaching and Patient Care

Erik Erikson’s eight stages of psychosocial development provide a lens to tailor communication and education strategies for diverse age groups. As an IV technician and educator, understanding these stages improves rapport, consent processes, and adherence to instructions.

Erikson Stage Clinical/Educational Application
1. Trust vs. Mistrust (infancy) Use soothing techniques, parental presence, and gentle explanations. For infants requiring IV therapy, parents’ trust is critical.
2. Autonomy vs. Shame (toddler) Offer limited choices (which arm) to support autonomy and cooperation during IV placement.
3. Initiative vs. Guilt (preschool) Provide simple, empowering explanations (“You are helping your blood find its way”) and praise.
4. Industry vs. Inferiority (school-age) Explain the process, enlist cooperation, and use distraction and rewards for compliance.
5. Identity vs. Role Confusion (adolescence) Respect privacy, ask permission, and provide clear, honest explanations about procedures and body image.
6. Intimacy vs. Isolation (young adult) Address concerns about independence and schedule coordination; provide full informed consent details.
7. Generativity vs. Stagnation (middle adult) Discuss how treatment supports life roles (work, family), and involve patients in planning their care.
8. Integrity vs. Despair (older adult) Respect life experience; explain the rationale for interventions and be sensitive to fears about decline and loss of autonomy.

Integrate Erikson’s stages into patient teaching and into mentorship strategies for student nurses, anesthesia techs, veterinary techs, and dentists who teach or supervise allied health staff. Tailor communication to developmental needs and cultural context.

Practical Medication Safety Tips for the IV Technician

  • Always perform the “five rights”: right patient, right drug, right dose, right route, right time.
  • Verify high‑risk medications and look‑alike vials with a second clinician if required by policy.
  • Use barcode scanning and smart pumps when available for additional error reduction.
  • Never assume a medication is saline simply because the bag is clear — read the label. Be vigilant for look‑alike vials (saline vs. atropine vs. lidocaine), different concentrations, and pre‑filled syringes.
  • When preparing lines for blood draws after infusion therapy, follow facility protocols for discard volumes and wait times. When in doubt, use a peripheral stick to avoid contamination of lab samples.

Education and Continuing Competency Resources

Ongoing education is essential. Several organizations provide guidelines, certification, and training resources particularly relevant to phlebotomy and IV therapy:

  • PCT Institute of Healthcare — programs and training resources for IV and allied health personnel.
  • Phlebotomy Career Training — training and certification pathways for phlebotomy and IV skills.
  • National phlebotomy and IV competency organizations and associations such as NAPTP and other national training associations provide standards and competency frameworks.
  • Federal and evidence‑based resources: CDC, NIH, NLM, and NIA.
  • Professional testing and credentialing bodies: consult national standards and exam boards such as NAPTP and related authorities for certification pathways and competency maintenance.

Documentation Table: What to Chart Immediately

Item Why It Matters
Time of cannulation or medication Provides temporal record for medication onset and line dwell time.
Catheter gauge and device Important for later troubleshooting and infusion compatibility.
Exact insertion site Tracks site complications and allows for targeted assessments.
Patient response and vitals Early documentation of adverse events informs rapid interventions and legal record.
Education provided Proof of informed consent and patient teaching.

Final Practical Reminders for Student Nurses, Nurses, Anesthesia Techs, Veterinary Techs, and Dentists

  • Always obtain and confirm physician authorization for therapies like chemotherapy and immunosuppressants.
  • Use chlorhexidine antisepsis with proper contact time — a minimum of approximately one minute is standard teaching; adhere to facility policy.
  • Insert needles bevel up at 15°–28°. Watch for flashback and do not force the catheter through the vein.
  • Recognize signs of infiltration, extravasation, infection, and air embolism; stop infusion and escalate per protocol when these occur.
  • Read labels carefully — the differential between saline, atropine, and lidocaine is critical. Double‑check medications prior to administration.
  • Do not apply tourniquets on arms with active IV lines unless specifically directed by policy; tourniquets may compromise flow and displace devices.
  • Chart thoroughly: time, gauge, location, and patient response are essential both clinically and legally.
  • Students and non‑licensed staff should consult supervisors for unfamiliar situations — admitting knowledge limits and seeking guidance protects patients and careers.

For additional professional development and certification pathways, consult training entities such as PCT Institute of Healthcare, Phlebotomy Career Training, and the national and federal resources listed above for evidence‑based protocols and updates.

Ready to Earn Your National IV Certification?

The National IV Association (NIVA) offers nationally recognized certification programs for nurses, EMTs, paramedics, and other licensed healthcare professionals. Train online, test when ready, and earn credentials that employers trust.

For foundational training in healthcare careers, visit the PCT Institute of Healthcare or explore certification options at Phlebotomy Career Training.
Enroll Now →

Categories
Uncategorized

Step-by-Step Guide to Peripheral IV Insertion: Technique, Tips, and Best Practices

Step-by-Step Guide to Peripheral IV Insertion: Technique, Tips, and Best Practices

By Nancy Kimmel, MSN, FNP, RN, PhD CHMM, MSN-FNP-BC — National IV Association

Preface: Who this guide is for

This in-depth, clinical guide is written for student nurses, nurses, anesthesia techs, veterinary techs, and dentists who perform or supervise peripheral intravenous (IV) therapy. It is also written for nurse educators and clinical instructors who teach IV insertion competency. I draw on evidence-based practice, bedside experience, and contemporary teaching strategies to provide a comprehensive, step-by-step reference that addresses technique, troubleshooting, pharmacologic considerations, patient populations (including geriatric care), documentation, legal responsibilities, and educator responsibilities.

Why IV therapy matters — brief clinical context

Intravenous therapy is central to modern healthcare. IV access is used for blood collection, chemotherapy, immunosuppressants, vitamin therapy, administration of crystalloids and colloids, antibiotics, and emergency resuscitation. Because fluids and medications delivered intravenously circulate rapidly and directly into the intravascular compartment, errors can produce systemic harm — from localized cellulitis to life-threatening air embolism or extravasation-induced tissue necrosis. Before initiating or performing IV insertion, ensure physician authorization or appropriate standing order per facility policy. Sterile technique and adherence to protocols are non-negotiable.

Anatomy and tissue layers traversed

Understanding anatomy helps the clinician select an appropriate site and anticipate potential complications. A peripheral IV cannula traverses the following layers:

  • Epidermis — the outermost protective layer of skin.
  • Dermis — contains capillaries, nerve endings, and connective tissue that affect pain and bleeding during insertion.
  • Hypodermis (subcutaneous adipose tissue) — thickness affects insertion angle and catheter length required.
  • Venous tunica — the vein’s intima, media, and adventitia form the vascular wall into which the catheter is placed.

Equipment checklist

Before any IV attempt, assemble all equipment to maintain asepsis and minimize interruptions:

  • Appropriate peripheral IV catheter (gauge selection table below)
  • Tourniquet, disposable gloves (sterile or non-sterile per facility policy), gauze
  • Antiseptic agent: chlorhexidine (perform a chlorhexidine, 1 min cleanse at the site when indicated)
  • Tape, transparent dressing, stabilization device
  • Normal saline flush (0.9% NaCl) labeled correctly, extension set or IV tubings as required
  • Sharps container, biohazard disposal bag
  • Tape measure / marker for site selection, patient identification materials, documentation tools

Catheter gauge selection

Gauge selection is driven by therapy type, vein size, and patient condition. The table below summarizes common gauges and typical uses.

Gauge Typical use Clinical notes
14–16G Rapid fluid resuscitation, trauma, blood transfusion Large bore; use only in large veins (antecubital fossa). Risk of vessel trauma.
18G Trauma, major surgery, blood products Common in ED and OR; good balance between flow rate and vessel trauma.
20G Most adult medical infusions, contrast injections Versatile; first choice for many adult medical patients.
22G Older adults, small veins, pediatrics (older children) Lower flow rates; reduces infiltration risk in fragile veins.
24–26G Pediatrics, neonates, very fragile veins Low flow; use microbore tubing. Increased risk of occlusion.

Site selection and vein mapping

Vein selection requires clinical judgment. Common peripheral sites include veins of the antecubital fossa (cephalic, basilic, median cubital) and the dorsal hand veins. General principles:

  • Prefer distal-to-proximal progression: attempt distal veins first to preserve proximal sites for future access.
  • Trace a selected vein at least an inch to ensure a straight segment for catheter placement — “trace veins for an inch.”
  • Avoid the hands and legs when possible, particularly in patients with diabetes or those at higher risk for infection and poor wound healing.
  • Avoid areas of flexion (wrist, antecubital crease) for long-dwelling catheters if possible; if necessary, secure with a stabilization device and transparent dressing.
  • Avoid limbs with compromised circulation, lymphedema, arteriovenous fistulas, or recent mastectomy on that side.

Patient preparation and informed consent

Explain the procedure using language appropriate to the patient’s developmental stage and cognitive status. For student nurses, anesthesia techs, veterinary techs, and dentists learning or refreshing skills, emphasize the importance of communication. Obtain informed consent per institutional policy; for nonverbal or cognitively impaired adults, follow surrogate decision-making protocols.

Integrating Erikson’s psychosocial stages into patient teaching

Erikson’s eight stages of psychosocial development can shape how you teach and comfort patients and students. For example:

  • Infancy (trust vs. mistrust): Use parent-centered communication and gentle touch for neonates and infants.
  • Early childhood (autonomy vs. shame): Offer simple choices (left or right arm) to increase cooperation.
  • School age (industry vs. inferiority): Provide clear explanations and encourage questions to foster mastery.
  • Adolescence (identity vs. role confusion): Respect privacy and offer involvement in decision-making.
  • Young/middle adulthood (intimacy, generativity): Address practical concerns around work and caregiving responsibilities.
  • Older adulthood (integrity vs. despair): In geriatric care, incorporate life history and autonomy; align consent with the patient’s values.

Using this framework helps instructors and clinicians tailor education to the patient’s developmental needs and improves adherence and satisfaction—essential in high-stress procedures such as IV insertion.

Sterile technique and infection prevention

Sterile technique reduces the risk of local and systemic infections. Key practices include:

  • Hand hygiene before and after any contact with the insertion site.
  • Use of chlorhexidine with a chlorhexidine, 1 min cleanse for adult patients unless contraindicated (e.g., neonates, allergy). Allow to air dry.
  • Avoid touching the cleaned site. If contamination occurs, re-cleanse and restart preparation.
  • Use sterile gloves per facility policy and consider addition of mask and drape for high-risk patients.
  • Apply transparent dressings to allow visualization of the site and change dressings per protocol or if soiled/loose.

Remember: IV therapy always requires situational awareness. Fluids and medications circulate rapidly; errors can cause systemic issues including infections, tissue necrosis, and air embolisms.

Step-by-step peripheral IV insertion technique

1. Verify order and patient identity

  • Confirm physician authorization or standing order, check indication (e.g., blood collection, chemotherapy, vitamin therapy), allergies, and relevant labs (coagulation status).
  • Confirm patient identity using two identifiers and explain the procedure.

2. Gather supplies and prepare the patient

  • Prepare equipment as listed above to maintain asepsis and avoid interruptions during the attempt.
  • Position patient comfortably with the selected limb supported and the site slightly below heart level if feasible to facilitate venous filling.
  • Apply a tourniquet proximal to the intended site. Do not use a tourniquet on an arm that already has an IV line in place.

3. Vein selection and visualization

  • Inspect and palpate veins. Warmth and gravity (dependent positioning) can improve venous prominence. Consider a warm pack for 5–10 minutes if veins are not visible.
  • Trace veins for at least one inch to ensure a straight course for catheter advancement.
  • Avoid areas with signs of infection, prior infiltration, hematoma, or venous sclerosis from repeated attempts.

4. Skin antisepsis

Perform the chlorhexidine, 1 min cleanse unless contraindicated. Use back-and-forth friction; allow to air-dry completely. Do not fan or blow on the site; this increases contamination risk.

5. Insertion angle and technique

Use an insertion angle of approximately 15–28 degrees with the bevel up. This shallow angle facilitates entry into the lumen while minimizing the risk of puncturing through the opposite wall. The steps:

  • Stabilize the vein with non-dominant hand — gently pull the skin taut below the insertion site.
  • Hold the catheter with dominant hand; insert the needle bevel up, advancing steadily.
  • Watch for flashback in the catheter hub or chamber. Flashback indicates venous entry. Maintain your angle until you see adequate blood return.
  • After flashback, advance the catheter slightly, then lower the angle and advance the catheter into the vein while retracting the needle.
  • If you feel a sudden give or “pop” and excessive blood returns, you may have passed through the vein — withdraw and apply pressure, then select a new site.

6. Securing the catheter and confirming patency

  • Connect prefilled saline flush or extension tubing. Do not force flush. Resistance on flush indicates the catheter or needle is not intravascular — stop, clamp if present, and reassess.
  • Flush gently with normal saline. Observe for patency and absence of swelling or pain. If infusion is painful or swelling occurs, suspect infiltration or extravasation and stop infusion immediately.
  • Secure catheter with adhesive stabilization and a transparent dressing to allow site visualization.

Recognizing flashback and preventing through-and-through puncture

Flashback is the visual return of blood into the catheter hub and confirms intraluminal entry. When you see flashback:

  • Do not push the catheter forcefully. Advance the catheter smoothly while withdrawing the needle.
  • If you push too hard initially, you may perforate the posterior wall and miss the lumen — the lecture notes caution: “Don’t push too hard or you’ll go through the vein.”
  • If there is no flash and you encounter resistance, withdraw slightly and re-angle or select a different site.

Infusion solutions, osmolarity, and physiologic considerations

Understanding solution characteristics is essential. Briefly:

  • Normal saline (0.9% NaCl) is isotonic. Per the clinical points to emphasize: “Normal saline (0.9% NaCl) is isotonic, matches body pH (7.35-7.45).” Be aware of facility policies and product specifics when choosing fluids.
  • Hypertonic solutions pull water into the vascular space and can reduce edema but may precipitate circulatory overload in patients with heart failure.
  • Hypotonic solutions shift fluid into the intracellular and interstitial spaces and are helpful for cellular dehydration but may worsen edema if used inappropriately.

Always read labels carefully — for example, saline vs. atropine vs. lidocaine — because medications can have significantly different vessel and systemic effects. Labeling errors can be catastrophic.

Drip rates and medication administration risks

Infusion rate must be individualized. Rapid infusion in fragile patients can precipitate cardiovascular overload resulting in signs such as increased heart rate, elevated blood pressure, shortness of breath, and hypoxemia — clinically this can escalate to a code blue. The practitioner must monitor patients receiving large-volume or rapid IV infusions, especially older adults and those with heart failure.

When administering medication via a peripheral IV:

  • Confirm medication compatibility with the IV solution and the catheter size.
  • Use appropriate dilution and infusion pumps for precise rates.
  • Observe for signs of extravasation (pain, swelling, blanching), and be ready with antidotes (e.g., phentolamine for vasoconstrictors) per protocol.

Flushing and drawing blood from IV lines

Flush technique:

  • Use a push-pause technique to create turbulent flow and reduce biofilm formation.
  • Use prefilled saline syringes when available to reduce contamination.
  • If drawing blood through an IV line, follow facility protocols regarding discard volumes and timing. For medication-dosed IVs, “wait appropriate times for medication-dosed IVs before drawing blood” to avoid sample contamination; when in doubt, consult pharmacy or lab services.

Troubleshooting common insertion and maintenance problems

Infiltration and extravasation

Signs: swelling, coolness, pain at the site, slowed or stopped infusion. Extravasation involves vesicant drugs and can cause tissue necrosis. Management:

  • Stop infusion immediately and disconnect tubing.
  • Aspirate residual drug from the catheter if possible, per protocol.
  • Elevate limb, apply warm or cold compress as indicated by the agent involved, and consult pharmacy/specialist.

Phlebitis

Signs: redness, tenderness, warmth, palpable cord along the vein. Management includes removing the catheter, applying warm compresses, and documenting. For infectious phlebitis, obtain cultures and treat per protocol.

Occlusion

Causes include thrombus, valve interference, kinking, or precipitate. Do not force flush. Assess, reposition, and consider a fibrinolytic lock per policy.

Air embolism

Although rare, air embolism is life-threatening. Prevent by ensuring all lines are clamped before disconnecting and that empty spaces in tubing are filled. If suspected, position patient in left lateral decubitus and head-down (Durant’s maneuver) and call for emergency support.

Special populations and considerations

Geriatric patients

Older adults have fragile veins, decreased skin turgor, and comorbidities that increase complication risk. Integrate guidance from geriatric authorities such as the National Center for Aging and Development (NCAD) and the National Institute on Aging (NIA) when planning IV care. Practical considerations:

  • Use smaller gauge catheters (e.g., 22G) and secure carefully to prevent dislodgement.
  • Consider stabilization devices and extra padding to protect fragile skin.
  • Perform more frequent site assessments and document findings. Use gentle cleansing agents and be mindful of chlorhexidine contraindications in certain geriatric skin conditions.

For geriatric resources, see NIA: https://www.nia.nih.gov/.

Pediatrics

Adjust technique and equipment size for children and neonates. Use distraction, parental involvement, and age-appropriate explanations. For neonates, chlorhexidine use is limited or modified and specialized microbore equipment and smaller gauges are required.

Veterinary considerations

Veterinary techs must account for species differences in vein anatomy, sedation level, and behavior. Principles of aseptic technique and catheter care are similar, but device sizes and securement strategies differ. Veterinary techs should follow local veterinary protocols and seek supervision when learning human-based techniques.

Documentation and legal/professional responsibilities

Charting is both a clinical and legal safeguard. Document:

  • Time of insertion and number of attempts
  • Catheter gauge and length
  • Exact location (include laterality and anatomic landmark)
  • Patient response to procedure and any analgesia used
  • Type and amount of flush, dressing applied, and any complications
  • Education provided and the patient’s understanding

Accurate documentation (time, gauge, location, response) provides legal protection and continuity of care.

Scope of practice and delegation

Know your scope of practice. Medical assistants (MAs) and students must consult supervisors and follow institutional policies. If a task exceeds your credentials or comfort, seek supervision and admit when you lack knowledge—this is a professional responsibility that protects patients.

Education and instructor best practices

As an educator, combine technical skill instruction with cognitive and affective learning strategies. The instructor page of any IV training curriculum should emphasize three Ps: preparation, passion, and patience.

Preparation

  • Prepare a detailed lesson plan that includes equipment lists, demonstration steps, common complications, and assessment criteria.
  • Set up simulation stations to mimic clinical reality and provide repeated deliberate practice opportunities for student nurses, nurses, anesthesia techs, veterinary techs, and dentists.

Passion

Demonstrate enthusiasm for safe practice. Students learn through role modeling; positive, authoritative teaching builds learner confidence and emphasizes the importance of patient-centered care.

Patience and classroom dynamics

Managing classroom dynamics requires patience. Tailor feedback to learner level—novices may need stepwise instruction, while advanced learners benefit from scenario-based challenges. Encourage questions and cultivate a psychologically safe learning environment where learners can admit mistakes and learn from them.

Continuous learning and competency maintenance

IV therapy skills require ongoing assessment. Encourage participation in refresher courses and use competency checklists. Recommend reputable training partners for continuing education such as PCT Institute of Healthcare and Phlebotomy Career Training for phlebotomy and peripheral IV skill development.

Teaching learners using Erikson’s framework

When instructing student nurses and other learners, adapt instructional strategies to their developmental and professional stage—applying Erikson’s stages in the classroom:

  • Encourage trust building in novices through mentorship (trust vs. mistrust).
  • Offer opportunities for autonomy with supervised practice (autonomy vs. shame).
  • Promote mastery through repetitive skills labs and summative assessment (industry vs. inferiority).
  • For adult learners (identity and generativity stages), emphasize the role of clinical competence in professional identity formation and patient advocacy.

Calculating drip rates and pump settings — practical notes

Infusion calculations must be accurate. Use volumetric infusion pumps for high-risk medications and pediatric infusions. When calculating manual drip rates, know the tubing drop factor and use the formula:

mL/hr ÷ 60 min × drop factor (gtt/mL) = gtt/min

When in doubt, use a pump. Rapid infusion can cause volume overload — monitor vulnerable patients closely and know the signs of decompensation (increased HR, BP, shortness of breath, low O2 saturation).

Communication with the interdisciplinary team

IV therapy involves interdisciplinary coordination. Inform pharmacy when initiating vesicant infusions or when medication compatibility is uncertain. Notify physicians for any unresolvable access failure, suspected complications, or patient deterioration. For student nurses and novice practitioners, escalating early is safer than attempting repeated blind attempts.

When to seek help and escalation policies

Escalate when:

  • Multiple unsuccessful attempts have occurred (follow facility policy for maximum attempts).
  • There is uncontrolled bleeding, signs of systemic infection, unexpected hypotension or hypoxia, or suspected air embolism.
  • There is uncertainty about medication compatibility, flushing procedures, or blood draw timing after medication infusion.

Documentation templates and sample charting language

Use concise, objective entries. Example:

“08:30 — Peripheral IV insertion, right median cubital vein, 20G x 1.25″, single attempt. Site prepped with chlorhexidine, 1 min cleanse; sterile gloves. Patency confirmed with 5 mL NS flush; no pain or swelling. Secured with transparent dressing. Patient tolerated procedure well. Plan: monitor q2h per IV policy. — N. Kimmel, MSN, RN”

References and additional resources

Authoritative resources for IV therapy, infection control, and geriatric care include:

Key takeaways for practice

  • Always confirm orders and patient identity before starting IV therapy.
  • Use aseptic technique and perform a chlorhexidine, 1 min cleanse when appropriate.
  • Select veins conservatively and trace veins for an inch to ensure a straight path for catheter advancement.
  • Insert the catheter at 15–28 degrees with the bevel up and watch for flashback; do not push too hard to avoid through-and-through puncture.
  • Read medication labels carefully (e.g., saline vs. atropine vs. lidocaine) and respect compatibility and timing for blood draws after medication-dosed IVs.
  • Document time, gauge, location, and patient response; documentation is legal protection.
  • Students and MAs should consult supervisors and never perform procedures beyond their scope of practice—admit when you lack knowledge.
  • Instructors: emphasize preparation, passion, patience, classroom management, and continuous learning. Use Erikson’s psychosocial stages to adapt teaching and patient education.
  • For geriatric patients, incorporate NCAD and NIA guidance — fragile veins and skin require modified technique and increased monitoring.

Appendix: Quick checklists

Pre-insertion checklist

  • Order verified and indication confirmed
  • Patient identity verified; consent obtained
  • All equipment prepared and within reach
  • Site selected and traced for at least 1 inch
  • Skin cleaned with chlorhexidine, 1 min cleanse if appropriate
  • Tourniquet applied (not on limb with existing IV)

Post-insertion checklist

  • Patency confirmed with gentle saline flush (no resistance)
  • Securement and dressing applied
  • Documentation completed (time, gauge, site, response)
  • Patient education delivered (what to report, activity restrictions)
  • Plan for monitoring and dressing changes communicated

For hands-on practice, structured curricula, and certification opportunities, consider resources such as PCT Institute of Healthcare and Phlebotomy Career Training. These platforms provide foundational and advanced training relevant to student nurses, nurses, anesthesia techs, veterinary techs, and dentists whose scope includes peripheral IV access.

Ready to Earn Your National IV Certification?

The National IV Association (NIVA) offers nationally recognized certification programs for nurses, EMTs, paramedics, and other licensed healthcare professionals. Train online, test when ready, and earn credentials that employers trust.

For foundational training in healthcare careers, visit the PCT Institute of Healthcare or explore certification options at Phlebotomy Career Training.
Enroll Now →

Categories
Uncategorized

NIVA Code of Ethics and Scope of Practice for IV Technicians

NIVA Code of Ethics and Scope of Practice for IV Technicians

By Nancy Kimmel, MSN, FNP, RN, PhD CHMM, MSN-FNP-BC

This comprehensive resource provides an in-depth, clinically focused examination of the National IV Association (NIVA) Code of Ethics and Scope of Practice for IV technicians. It is written for student nurses, nurses, anesthesia techs, veterinary techs, and dentists who perform or supervise intravenous (IV) procedures, and for educators who train them. The content synthesizes core IV clinical principles, procedural safety, professional responsibilities, and educational methods while integrating foundational psychosocial theory (Erikson) and geriatric care considerations (National Center for Aging and Development and the National Institute on Aging).

Overview: Purpose and Audience

NIVA’s Code of Ethics and Scope of Practice exists to protect patients and the public, to define the professional boundaries that maintain safe practice, and to support ongoing competency-based education. This article is designed to be a practical reference for student nurses, nurses, anesthesia techs, veterinary techs, and dentists, and for the instructors who teach them.

Why a Code of Ethics and Defined Scope Matter

IV therapy is powerful: fluids and medications delivered intravenously circulate systemically within seconds. Errors are not localized—they produce systemic effects. The misuse of IV routes can cause infections, tissue necrosis, infiltration/extravasation, air embolisms, volume overload leading to cardiopulmonary decompensation, and medication errors. An explicit Code of Ethics and a clearly defined Scope of Practice set expectations for clinical competence, patient safety, communication, documentation, and interprofessional collaboration.

The NIVA Code of Ethics: Principles and Practical Applications

The following ethical principles are central to NIVA’s Code of Ethics and must be interpreted in the context of bedside IV care, education, and interprofessional practice.

1. Respect for Patient Autonomy

Patients have the right to informed consent, to refuse IV treatments, and to receive information about risks, benefits, and alternatives. IV technicians should provide clear, age- and developmentally appropriate explanations and escalate consent issues to the supervising nurse or physician when necessary. Student nurses and trainees must be supervised while obtaining consent and performing invasive procedures.

2. Beneficence and Non-maleficence

Do good; avoid harm. For IV technicians this includes strict adherence to sterile technique (e.g., chlorhexidine skin antisepsis with a one-minute frictional scrub where indicated), careful vein selection, correct catheter selection and securement, proper labeling and checking of infusion solutions (read the label carefully—saline vs atropine vs lidocaine), and immediate response to signs of complication. Never push through resistance during insertion or during a flush; resistance frequently means you are not intravascular.

3. Competence and Scope Awareness

Stay within your authorized scope. Medical assistants and IV technicians must consult supervising nurses or physicians when any aspect of the procedure, medication administration, or patient condition exceeds their training. Admit when you lack knowledge. Chart thoroughly (time, gauge, location, patient response) for legal protection and continuity of care.

4. Confidentiality and Professional Boundaries

Maintain patient privacy and avoid dual relationships that could impair clinical judgment. In education settings, model professional boundaries for student nurses and other trainees.

5. Veracity and Accountability

Accurate documentation and truthful communication are non-negotiable. Report errors and near misses through institutional channels and participate in root cause analyses and quality improvement. Ethical practice includes advocating for patient safety and system improvements.

6. Justice and Fairness

Provide equitable IV care without discrimination. This includes allocation of limited resources (e.g., ultrasound devices) based on clinical need and ensuring vulnerable populations—older adults, pediatrics, individuals with disabilities—receive appropriate assessment and accommodations.

Scope of Practice: What IV Technicians May and May Not Do

NIVA’s Scope of Practice delineates authorized tasks, required supervision levels, and activities that must be performed by licensed clinicians.

  • Authorized tasks (typical): peripheral IV insertion, peripheral IV maintenance, dressing changes, peripheral IV discontinuation, basic troubleshooting (e.g., unclamping tubing, checking flow), saline flushes per protocol, documentation, and appropriate escalation.
  • Require direct supervision or a licensed provider: medication administration beyond flushes (depends on state/agency), blood product administration, central line insertion/management, drawing arterial blood gases, advanced troubleshooting for suspected extravasation of vesicants.
  • Prohibited unless separately credentialed: central venous catheter insertion, peripherally inserted central catheter (PICC) insertion, infusion of chemo agents or other high-risk medications without credentialing, independent changes to prescribed infusion rates or solutions.

Medical assistants (MAs) must consult supervisors and must never exceed their authorized scope. The ethical duty to “do no harm” requires immediate consultation when patient condition changes, when there is uncertainty, or when equipment or medication labels are unclear.

Clinical Foundations: Principles of Safe IV Therapy

Understanding the clinical foundations is essential for ethical, competent practice. The following sections summarize critical technical knowledge.

Indications for IV Access

Common indications include blood collection, chemotherapy, immunosuppressant infusion, vitamin therapy, fluid resuscitation, administration of parenteral medications, and emergent access for unstable patients. All IV therapy requires appropriate physician authorization or delegated provider order per institutional policy.

Vein Selection and Anatomy

Choose veins that maximize catheter longevity and minimize complications:

  • Antecubital fossa veins (cephalic, basilic, and median cubital) are common initial choices for adults. Trace a vein for an inch to ensure continuity and suitable caliber before cannulation.
  • Avoid hands and legs unless necessary. Avoid legs especially in diabetics and patients with peripheral vascular disease due to venous stasis and thrombotic risk.
  • In pediatric or geriatric patients, superficial veins on the dorsum of the hand may be used cautiously; however, elder skin fragility and venous fragility require smaller-gauge catheters and atraumatic technique.

Insertion Technique

Key technical points every student nurse, nurse, anesthesia tech, veterinary tech, and dentist who performs venipuncture must master:

  • Position the patient and site for comfort and visibility. Use appropriate lighting and a stable platform.
  • Apply a tourniquet and palpate the vein. Do not leave a tourniquet on arms that already have an IV line in situ for blood draw or other procedures—this is a safety rule.
  • Perform antisepsis with chlorhexidine (or approved alternative) and allow the frictional scrub to dry; the recommended one-minute cleanse (or manufacturer’s guidance) reduces pathogen transmission.
  • Insert the catheter at a 15–28 degree angle with the bevel up. Lower the angle as you approach the vein. Watch for flashback; flashback indicates intraluminal entry. Do not “push through”—if you push too hard you’ll go through the opposite wall of the vein and create infiltration or extravasation.
  • After insertion, stabilize the catheter, flush gently with normal saline. Resistance on flush indicates malposition or infiltration—do not force. If resistance occurs, stop and reassess.

Layers Traversed and Vascular Structure

A cannula or needle traverses the epidermis, dermis, hypodermis (subcutaneous tissue), and then the venous tunica. Understanding this layered anatomy helps explain potential complications—bleeding under the skin (hematoma), infiltration into subcutaneous layers, and vessel wall trauma.

Needle and Catheter Selection

Needle gauge selection balances flow needs against vessel trauma. Use the smallest gauge that safely delivers the ordered therapy. The table below summarizes typical gauge selection and clinical uses.

Gauge Common Uses Pros/Cons
14–16G Rapid transfusion, trauma resuscitation High flow; increased vessel trauma risk
18G Surgery, blood products Good balance of flow and safety
20–22G General IV therapy, medications, blood draws Most common for adults
22–24G Pediatrics, fragile veins, elderly Less trauma; slower infusion rates

IV Fluids: Physiology and Clinical Effects

Understanding fluid tonicity and osmotic effects is essential for safe IV therapy.

Solution Type Primary Effect Clinical Indications / Cautions
Isotonic (e.g., Normal Saline 0.9% NaCl) Stays predominantly in the vascular space Used for volume resuscitation and maintenance. Normal saline is isotonic. Note: normal plasma pH is 7.35–7.45; choose fluids mindful of acid-base status and institutional protocols.
Hypertonic Draws water into the vascular compartment from cells Used to reduce cellular edema (e.g., cerebral edema). Can precipitate volume overload—high risk for congestive heart failure (CHF) patients.
Hypotonic Pushes water out of vasculature into tissues and cells Used for intracellular dehydration. Can worsen hypotension or cause edema if used improperly.

Rapid infusion in fragile patients may precipitate cardiovascular overload, pulmonary edema, and acute decompensation—manifested by increased heart rate, elevated blood pressure, shortness of breath, and low oxygen saturation, which can escalate to a code blue situation.

Medication Considerations and Drip Rates

Drip rates and medication administration require careful calculation and monitoring. IV technicians must confirm orders, double-check medication labels (saline vs atropine vs lidocaine), and follow institutional protocols for medication admixture and administration rates.

  • Some medications are vesicants or irritants—extravasation can cause tissue necrosis. Treat vesicants per institutional policy and call for licensed provider intervention immediately for suspected extravasation.
  • Allow appropriate dwell time and flush protocols between medication-dosed IV infusions and subsequent blood draws. Institutional policies dictate specific wait times and flushing volumes; always follow the supervising clinician’s orders.

Complications of IV Therapy and Early Recognition

Early recognition and timely interventions reduce morbidity. Common complications include:

  • Infiltration/extravasation: swelling, pain, coolness at site; stop infusion and follow extravasation protocol.
  • Phlebitis: pain, erythema, warm along vein; remove catheter and treat per policy.
  • Infection/bacteremia: fever, erythema, drainage; maintain strict sterile technique to reduce risk.
  • Hematoma: bruising at site due to vessel puncture—apply pressure and monitor.
  • Air embolism: sudden respiratory distress, hypotension—prevent by eliminating air in lines and using air-elimination techniques; treat emergently.
  • Fluid overload/pulmonary edema: monitor at-risk patients (CHF, renal failure) closely for increased HR, elevated BP, shortness of breath, low O2 sat.

Documentation and Legal Protection

Comprehensive charting is essential both for patient safety and legal protection. Document the following elements consistently:

  • Time of insertion/removal
  • Gauge and catheter type
  • Exact location (e.g., “right antecubital fossa — cephalic vein”)
  • Number of attempts
  • Patient response and condition (e.g., pain, swelling)
  • Flush volumes used and response to flush (note resistance or free flow)
  • Medications administered through the line and timing
  • Education provided to patient/family and consent status

Accurate documentation protects the clinician and supports continuity of care. Student nurses should have supervised practice in documenting IV procedures until competency is demonstrated.

Interprofessional Collaboration and Communication

IV technicians, nurses, student nurses, anesthesia techs, veterinary techs, and dentists must practice clear handoffs and immediate reporting of adverse events. Use standardized communication tools (e.g., SBAR—Situation, Background, Assessment, Recommendation). When in doubt—consult. For MAs and other non-licensed staff, the expectation is timely escalation to a supervising nurse or provider.

Education and Instructor Responsibilities

Instructors who train IV technicians and student nurses must embody the principles of the Code of Ethics and adapt their teaching to diverse learners and clinical contexts. Key instructor competencies include:

Preparation

Develop structured lesson plans, simulation scenarios, and objective competency checklists. Integrate evidence-based guidelines and current infection-prevention standards. Provide learners with pre-class materials and assessment rubrics.

Passion

Model enthusiasm for patient safety and clinical excellence. Passion sustains learner engagement and fosters a culture of continuous improvement. Passionate educators inspire curiosity and adherence to best practices.

Patience

Skill acquisition for IV procedures requires repeated practice, feedback, and time. Recognize varying learner paces and provide remediation. Use deliberate practice and reflective debriefs after simulated or clinical encounters.

Managing Classroom and Clinical Dynamics

Maintain a psychologically safe learning environment. Balance didactic content, demonstration, and hands-on practice. Mitigate bullying or humiliation—these behaviors are antithetical to professional development and ethical practice.

Continuous Learning

Promote ongoing competency assessments, continuing education, and interprofessional learning. Keep curricula aligned with national guidance from agencies like the Centers for Disease Control and Prevention (CDC) and the National Institutes of Health (NIH).

Integrating Erikson’s Psychosocial Stages into IV Education and Patient Care

Erik Erikson’s eight stages of psychosocial development provide a framework to tailor communication and teaching strategies for both patients and learners. Below is an applied map of the eight stages and recommended approaches for IV technicians and instructors.

Erikson Stage Developmental Task (Brief) Application to Patient Education and Learner Teaching
Infancy: Trust vs Mistrust Establish trust through consistency and care Use calm, reassuring tones; involve caregivers. For student learners, create a safe initial practice environment.
Toddlerhood: Autonomy vs Shame Encourage independence while providing boundaries Offer small choices (which arm) when appropriate. Allow learners to try simple tasks with supervision.
Preschool: Initiative vs Guilt Foster initiative Explain procedures playfully and positively to children. For learners, encourage initiative with guided projects.
School-age: Industry vs Inferiority Develop competence Provide concrete explanations and involve school-age patients in choices. Use competency checklists for students.
Adolescence: Identity vs Role Confusion Support identity formation Respect autonomy and privacy; offer clear rationales for IV therapy. For students, support professional identity formation.
Young Adulthood: Intimacy vs Isolation Develop meaningful relationships Encourage open communication and involve partners when appropriate. Use mentorship models for early-career clinicians.
Middle Adulthood: Generativity vs Stagnation Contribute to future generations Engage experienced clinicians in teaching and quality improvement; model lifelong learning.
Late Adulthood: Integrity vs Despair Reflect on life with a sense of fulfillment For older adults receiving IV care, provide dignity, clear explanations, and involvement in decision-making. Address legacy concerns and comfort.

Using Erikson’s model helps student nurses, nurses, anesthesia techs, veterinary techs, and dentists tailor communication strategies across the lifespan. For example, older adults in the “integrity vs despair” stage may value autonomy and clear explanations—align education accordingly. Learners at different stages of professional development also respond better to approaches congruent with their psychosocial needs.

Geriatric Considerations: NCAD and NIA Guidance

IV therapy in older adults requires particular attention. The National Center for Aging and Development (NCAD) and the National Institute on Aging (NIA) emphasize comprehensive assessment and individualized care plans.

Key geriatric considerations include:

  • Fragile skin and veins: Use smaller gauge catheters (e.g., 22–24G), gentle tape removal techniques, and consider stabilization devices.
  • Polypharmacy and altered pharmacokinetics: Be mindful of medication selection and infusion rates; consult pharmacy when necessary.
  • Comorbid cardiac or renal disease: Monitor fluid status closely. Avoid aggressive hypertonic infusions in CHF patients.
  • Hydration status: Many older adults have baseline dehydration or impaired thirst perception; isotonic fluids may be preferred for volume resuscitation.
  • Cognitive impairment: Use clear, calm explanations and involve caregivers. Ensure consent criteria are satisfied and document surrogate decision-maker involvement when required.

Specialized Contexts: Veterinary and Dental IV Access

Veterinary techs and dentists performing IV procedures operate in specialized contexts but must adhere to the same ethical, sterile, and safety principles. For veterinary practice, anesthesia techs and veterinary techs should ensure species-specific anatomy and behavior are accounted for, and consult supervising veterinarians for sedated or anesthetized patients. Dentists sometimes obtain venous access for procedural sedation—this requires competency, adherence to institutional sedation policies, and immediate availability of resuscitation equipment.

Training Resources and Certification Pathways

Ongoing education and credentialing strengthen practice. Consider the following training resources and organizations to support competency development:

  • PCT Institute of Healthcare — a resource for allied health education and career development: PCT Institute of Healthcare
  • Phlebotomy Career Training — targeted programs for phlebotomy and venipuncture skills: Phlebotomy Career Training
  • National Association of Phlebotomy Training Programs (NAPTP) for program standards
  • National Testing Associates (NTA)—credentialing and testing resources: NTA
  • Evidence-based infection prevention and clinical guidance from government sources: CDC, NIH, and the National Library of Medicine

Quality Assurance, Reporting, and Continuous Improvement

Quality assurance programs should include competency verification, ongoing audits of sterile technique, monitoring of complication rates (phlebitis, infection, infiltration), and reviews of documentation completeness. When errors occur, non-punitive reporting systems encourage transparency. Participate in root cause analyses and corrective action planning.

Case Studies and Practical Scenarios

Scenario 1: Resistance on Flush

A 68-year-old patient with CHF has a newly placed peripheral IV for fluid administration. During the initial saline flush, the IV technician experiences resistance. What to do?

  • Stop flushing immediately—do not force.
  • Assess the site for swelling, tenderness, blanching (signs of infiltration), and assess for any kinks or clamped tubing.
  • Notify the supervising nurse or provider. If infiltrated or malpositioned, discontinue and re-site per policy.
  • Document findings and patient response (time, catheter gauge, location, response).

Scenario 2: Rapid Infusion Signs of Overload

A frail patient receives a bolus of isotonic saline. Shortly thereafter the patient exhibits tachycardia, dyspnea, and low O2 saturation. Actions:

  • Stop the infusion and place the patient upright if tolerated.
  • Call for immediate nursing/medical assistance; this may be evolving into pulmonary edema.
  • Administer oxygen and monitor vitals. Prepare to support airway and circulation per protocol.
  • Document the event thoroughly, including pre-event vitals, infusion type and rate, and actions taken.

Ethical Dilemmas and Decision-Making

The NIVA Code of Ethics equips IV technicians to identify and navigate ethical dilemmas. Common dilemmas include requests to perform procedures beyond scope, conflicts between patient wishes and medical orders, and balancing trainee autonomy with patient safety. Apply ethical principles—beneficence, non-maleficence, autonomy, justice—and institutional policies to guide actions. When in doubt, escalate and document the consultation.

Teaching Recommendations for Instructors

Instructors should incorporate multi-modal teaching strategies, including:

  • Didactic sessions covering anatomy, fluid physiology, medication safety, and ethics.
  • Simulation-based mastery learning with standardized checklists and deliberate practice.
  • Supervised clinical experiences with progressive responsibility for student nurses and trainees.
  • Reflective debriefs that integrate Erikson’s psychosocial stages to discuss patient communication and professionalism.
  • Assessment tools that measure skills (insertion technique, aseptic practice), knowledge (fluids and medications), and professional behaviors (communication, documentation).

Documentation Tools and Suggested Charting Language

Use clear, standardized language. Examples:

  • “08:35 — Peripheral IV inserted, right antecubital fossa (cephalic vein), 20G catheter. One attempt. Flush with 10 mL normal saline—patent, no resistance. Dressing applied. Patient tolerated procedure without complication. — N. Kimmel, RN (supervisor: Dr. Smith present)”
  • “14:10 — Assessed IV site: mild erythema, no drainage. Patient reports 2/10 discomfort. Catheter removed per protocol; site compressed, dressing applied. Notified supervising RN. Documented in EHR.”

Regulatory and Institutional Considerations

State boards of nursing, the Centers for Medicaid & Medicare Services, and institutional policies define permissible activities for IV technicians. Always confirm local regulations and institutional policies. Credentialing bodies like NAPTP and NTA provide programmatic standards and testing that support compliance and competence.

Practical Tips and Reminders for Clinicians and Students

  • Always read the medication/fluid label before connecting to the IV. Mistaking saline for another medication (e.g., atropine, lidocaine) is a preventable error.
  • Remember the insertion angle: 15–28 degrees, bevel up, monitor for flashback. Lower the angle as you enter the vein.
  • Trace a chosen vein for at least an inch to ensure adequate length and caliber.
  • Do not routinely use hands or legs for IVs unless necessary; diabetics and patients with peripheral vascular disease have higher complication rates in lower extremities.
  • Allow the antiseptic solution to dry fully—following a one-minute frictional scrub with chlorhexidine where indicated—before insertion.
  • If you meet resistance on flush, stop; reassess and escalate if necessary.
  • Document—time, gauge, location, response—every intervention accurately for legal protection and continuity of care.
  • MAs and other support staff must consult supervisors with any uncertainty and must not perform tasks beyond delegated authority.

Resources and Further Reading

Authoritative resources for continued learning and policy reference include:

Appendix: Checklists and Competency Tools

Pre-Insertion Checklist

  • Confirm order and indication for IV access.
  • Verify patient identity using two identifiers.
  • Explain procedure, obtain consent, and address questions.
  • Assemble equipment; verify expiration dates and integrity of packaging.
  • Perform hand hygiene and don appropriate PPE.
  • Palpate and select appropriate vein; avoid compromised limbs.
  • Apply antiseptic and allow to dry (one-minute scrub with chlorhexidine where indicated).

Post-Insertion Competency Checklist

  • Catheter secured and dressing applied per protocol.
  • Flush performed and patency confirmed without resistance.
  • Infusion set-up completed and checked for rate and compatibility.
  • Patient comfort assessed and education provided.
  • Documentation completed: time, gauge, location, response, supervising clinician.

Final Notes on Professionalism and Lifelong Learning

Professionalism in IV practice emerges from a synthesis of technical skill, ethical clarity, and interprofessional collaboration. Student nurses, nurses, anesthesia techs, veterinary techs, and dentists must commit to continuous learning, seek supervision when needed, and maintain meticulous documentation. The NIVA Code of Ethics and Scope of Practice are living documents: they require active engagement, regular review, and thoughtful application in real-world clinical and educational contexts.

Ready to Earn Your National IV Certification?

The National IV Association (NIVA) offers nationally recognized certification programs for nurses, EMTs, paramedics, and other licensed healthcare professionals. Train online, test when ready, and earn credentials that employers trust.

For foundational training in healthcare careers, visit the PCT Institute of Healthcare or explore certification options at Phlebotomy Career Training.
Enroll Now →

Categories
Uncategorized

IV Therapy in Pediatric Patients: A Complete Clinical Guide

IV Therapy in Pediatric Patients: A Complete Clinical Guide

By Nancy Kimmel, MSN, FNP, RN, PhD CHMM, MSN-FNP-BC

Introduction: The Critical Role of IV Therapy in Pediatrics

Intravenous (IV) therapy is a foundational clinical skill across multiple disciplines: pediatrics, emergency medicine, oncology, perioperative care, and ambulatory settings. For student nurses, nurses, anesthesia techs, veterinary techs, and dentists who may encounter pediatric patients, mastery of pediatric IV therapy is essential for safe, effective care. IV therapy in children supports blood collection, administration of chemotherapy and immunosuppressants, parenteral vitamin therapy, hydration, and urgent medication delivery. All IV orders must be authorized by a licensed physician or other prescriber as defined by institutional policy and local scope of practice.

Indications and Authorization

IV therapy indications common in pediatric practice include:

  • Blood collection for laboratory evaluation and culture.
  • Administration of chemotherapeutic agents and immunosuppressants (requires strict authorization and monitoring).
  • Vitamin and nutritional therapy, including parenteral fluids and electrolytes.
  • Fluid resuscitation, maintenance fluids, and medication delivery (antibiotics, analgesics, vasoactive drugs).

Remember: high-risk therapies such as chemotherapy and immunosuppressants require prescriber authorization, chemo-certified personnel when required, and adherence to institutional chemotherapy safety policies. Errors in IV therapy circulate rapidly and can cause systemic complications including infections, tissue necrosis from extravasation, and, in severe cases, air embolisms or systemic toxicity. Sterile technique and correct verification of medication labels are non-negotiable elements of safe practice.

Anatomy and Vein Selection for Pediatric IVs

Successful peripheral IV insertion begins with anatomic understanding and careful site selection. Pediatric vascular anatomy differs from adults in caliber, position, and accessibility. Vein selection should consider patient age, diagnosis, mobility, and planned therapy duration.

Common Peripheral Sites

  • Antecubital fossa veins: cephalic, basilic, and median cubital veins — often the most palpable and visible veins.
  • Dorsum of the hand — commonly used but should be avoided when possible in infants and toddlers if there are better alternatives.
  • Scalp veins — useful in neonates and infants where peripheral access is limited; use with caution and securement.
  • Foot veins — acceptable when upper extremity access is contraindicated, but avoid in ambulatory children unless necessary.

When selecting a vein, “trace the vein for an inch” to confirm continuity and avoid sites that are tortuous, near flexion points, or have prior infiltration or phlebitis. For patient populations such as diabetics, avoid lower extremity sites when possible due to increased risk of infection and impaired healing. For central access considerations, consult the prescriber and vascular access team.

Pediatric Considerations

In children, vein size is smaller and more collapsible; choose the smallest gauge that accommodates therapy. Use warm compresses, gentle tapping, gravity, or a mild tourniquet to enhance vein fill. In infants, the scalp or dorsum of the hand may be the most reliable. Always balance ease of access with long-term vascular preservation.

Layers Traversed During Insertion

A peripheral IV catheter traverses several tissue layers from skin to vein:

  • Epidermis
  • Dermis
  • Hypodermis (subcutaneous tissue)
  • Venous tunica (vein wall)

Understanding the tissue planes helps clinicians anticipate depth, resistance, and potential complications such as infiltration or extravasation.

Technique: Preparation, Sterile Practice, and Insertion

Proper preparation is the cornerstone of pediatric IV success. This section integrates teaching points for student nurses, nurses, anesthesia techs, veterinary techs, and dentists who may participate in IV-related care.

Preparation and Patient Engagement

  • Confirm the order and indication; verify allergies and current medications.
  • Assemble supplies: appropriate catheter size, chlorhexidine antiseptic, sterile gloves, tape, dressings, flush syringe, extension set, and tape securement devices.
  • Use distraction techniques, parent involvement, topical anesthetic (e.g., EMLA) when appropriate, and age-appropriate explanations. Erikson’s psychosocial stages can guide your communication (see Erikson integration section).

Sterile Technique and Skin Antisepsis

Sterile technique minimizes systemic complications. Use chlorhexidine for skin antisepsis when appropriate; rub for at least 1 minute per evidence-based guidance to reduce surface microbes and improve line safety. Note: in neonates and certain sensitive patients, consult institutional protocols regarding chlorhexidine use and contact precautions.

Insertion Angle and Catheter Advancement

Approach the vein at a 15–28 degree angle with the catheter bevel up. A shallow angle reduces the risk of transfixing the vein. Watch for a reliable flashback in the catheter hub or chamber; this confirms venous entry. Advance the catheter just enough to seat it in the lumen and then lower the angle and advance the plastic catheter off the needle into the vein. If you feel a sudden loss of resistance or a brisk flash then loss of flash when advancing, you may have passed through the vein—withdraw and reassess.

Do not “push too hard” during advancement; forcing the catheter increases the risk of through-and-through perforation and infiltration. After insertion, secure the catheter firmly and test with a gentle flush. Resistance on flush usually indicates the catheter is not fully intravascular or that the tip is against a vessel wall—do not infuse under high pressure.

Catheter Selection and Gauges

Select catheter gauge by therapy type and patient age:

Age/Use Suggested Gauge Comments
Neonates/Infants 24–26G Use smallest possible; consider scalp or foot veins; secure carefully.
Young children 22–24G Balance flow needs and vessel preservation.
Older children/adolescents 20–22G May permit faster infusions; consider future medication viscosity.
Rapid resuscitation (if necessary) 18–20G Use only when rapid volume replacement is clinically indicated.

Complications and Their Recognition

Complications can be local or systemic and may present rapidly in pediatric patients due to smaller circulating volume and higher metabolic demand.

Local Complications

  • Infiltration — IV fluid leaking into subcutaneous tissue; presents with swelling, coolness, and decreased flow.
  • Extravasation — leakage of vesicant medication causing tissue necrosis; requires immediate intervention and physician notification.
  • Phlebitis — inflammation of the vein with pain, redness, and warmth along the vessel.
  • Catheter occlusion — inability to flush; may be due to thrombus or catheter kinking.

Systemic Complications

  • Systemic infection (catheter-related bloodstream infection) — fever, tachycardia, hypotension.
  • Air embolism — sudden respiratory distress, hypotension, neurologic changes; risk with central lines but possible with peripheral lines if not handled properly.
  • Fluid overload/pulmonary edema — particularly in fragile patients with rapid infusion.

Rapid infusion in fragile pediatric patients can precipitate acute cardiovascular decompensation. Clinical signs include increased heart rate, elevated blood pressure, shortness of breath, and falling oxygen saturation — a potential progression to code blue if not recognized and treated emergently.

Fluids, Osmolality, and pH: Clinical Implications

Understanding fluid types and physiological effects is critical when choosing IV fluids for children. Use clear labeling and read every medication label carefully — saline, atropine, lidocaine, and other agents have different indications and risks. Wait the appropriate institutional-specified time after administering medication through an IV before drawing blood from that same line for laboratory accuracy.

Fluid Types

Fluid Classification Physiologic Effect Clinical Use / Cautions
Normal saline (0.9% NaCl) Isotonic Matches intravascular osmolality; commonly used for replacement and maintenance Common first-line fluid. (Lecture note: Normal saline (0.9% NaCl) is isotonic, matches body pH (7.35–7.45) — clinicians aim to maintain physiologic pH.)
Hypertonic solutions (e.g., 3% NaCl) Hypertonic Pulls water into the vascular space from interstitial/cellular compartments Used to treat severe hyponatremia, cerebral edema; risky in heart failure due to volume shifts.
Hypotonic solutions (e.g., 0.45% NaCl) Hypotonic Pushes fluid into cells and interstitial compartments Used cautiously for cellular dehydration; avoid in at-risk patients for cerebral edema.

Note: The classification of a fluid’s effect on body compartments (isotonic, hypertonic, hypotonic) guides the clinician’s choice in treating edema, dehydration, and electrolyte disturbances. Hypertonic solutions can reduce interstitial edema by drawing fluid into the vascular system, but in conditions such as congestive heart failure (CHF) this can precipitate volume overload. Hypotonic fluids move water into tissues and cells, which can be therapeutic in dehydration but dangerous if cerebral edema is present.

Drip Rates, Calculations, and Pediatric Fluid Management

Precise calculation of drip rates is essential in pediatrics because small volume differences are clinically important. Understand microdrip versus macrodrip systems, mL/hr, and gtt/min calculations. Microdrip sets typically deliver 60 gtt/mL; macrodrip sets vary (10, 15, 20 gtt/mL).

Maintenance Fluid Formula (4-2-1 Rule)

Use the 4-2-1 rule to estimate hourly maintenance fluid requirements for children:

  • 4 mL/kg/hr for the first 10 kg
  • 2 mL/kg/hr for the next 10 kg (10–20 kg)
  • 1 mL/kg/hr for each kg >20 kg

Example: A 15 kg child → (4 mL x 10 kg) + (2 mL x 5 kg) = 40 + 10 = 50 mL/hr maintenance.

Drip Rate Calculation Example

Parameters Values
Ordered 50 mL/hr
IV set Microdrip 60 gtt/mL
Formula gtt/min = (mL/hr × gtt/mL) ÷ 60
Calculation (50 × 60) ÷ 60 = 50 gtt/min

Document clearly and confirm pump settings. For rapid infusions, use a controlled infusion pump when available and monitor for signs of circulatory overload — tachycardia, hypertension, respiratory distress, crackles on auscultation, and decreased oxygen saturation.

Medication Safety: Reading Labels and Timing with Blood Draws

Always read medication labels out loud and confirm the “Five Rights” (right patient, right drug, right dose, right route, right time). Saline, atropine, and lidocaine are examples of agents often encountered near IV access — each has distinct indications and adverse effect profiles; be vigilant. Some medications can contaminate blood draws or alter laboratory values; institutional policies guide how long to wait after medication administration before drawing blood from the line and how much wasted volume to discard. If in doubt, draw peripheral blood or consult pharmacy or lab for guidance.

Important operational note: do not apply a tourniquet proximal to an arm that contains an active IV line. Tourniquet application on the same limb may alter infusion dynamics and risk infiltration or interstitial injection if applied improperly.

Monitoring and Documentation: Professional Responsibilities

Accurate documentation is both a patient safety measure and legal protection. Chart the following elements at minimum:

  • Time of insertion and removal
  • Catheter gauge and length
  • Site (specific location, e.g., right antecubital fossa, cephalic vein)
  • Number of attempts and personnel who performed procedure
  • Patient response and tolerance
  • Patency checks and flush records
  • Any complications and interventions implemented

For student nurses and allied personnel such as anesthesia techs, veterinary techs, and dentists involved in IV procedures, documentation demonstrates clinical reasoning and adherence to standards. Medical assistants and other support staff must consult supervisors and remain within their institutional scope of practice. If you lack knowledge or are unsure, admit it and seek assistance — this is a professional ethical responsibility that protects patients and clinicians alike.

Special Populations: Neonates, Infants, and Adolescents

Pediatric patients span a broad developmental range and require age-specific modifications in approach, equipment, and communication. From neonates to adolescents, consider growth, body composition, and psychosocial stage when planning IV therapy.

Neonates and Infants

  • Use the smallest gauge feasible; constant monitoring for infiltration and catheter stability is imperative.
  • Scalp veins can be an acceptable site in infants; secure well and protect from parental hair pulling.
  • Chlorhexidine use in neonates has special considerations—adhere to facility protocols.

Older Children and Adolescents

  • Incorporate the adolescent into decision-making; assent is developmentally appropriate along with parental consent.
  • Consider patient preferences for site and securement where possible to enhance cooperation.

Teaching, Supervision, and Erikson’s Psychosocial Stages

Teaching IV skills to student nurses and instructing caregivers or older pediatric patients requires not only technical instruction but also an understanding of human development. Erikson’s eight stages of psychosocial development can be integrated into teaching strategies to enhance patient and learner receptivity.

Erikson Stage Age Range Teaching Strategy for IV Care
Trust vs. Mistrust Infancy Establish soothing presence; involve caregiver for comfort; use gentle touch and predictable routines.
Autonomy vs. Shame/Doubt Toddler Offer simple choices (e.g., which hand) to support autonomy; use distraction and brief, clear instructions.
Initiative vs. Guilt Preschool Use play, role modeling with dolls, and praise to encourage cooperation.
Industry vs. Inferiority School Age Explain procedures in concrete terms; involve the child in preparation and allow them to “help” as appropriate.
Identity vs. Role Confusion Adolescence Respect privacy and autonomy; provide clear rationale and let adolescents ask questions and participate in decisions.

Applying psychosocial principles enhances trust and adherence. When teaching student nurses, instructors should mirror these principles with learners — foster trust, encourage autonomy and initiative, and support learners through stages of competence.

Instructor Concepts: Preparation, Passion, Patience

For educators teaching IV therapy to student nurses, nurses, anesthesia techs, veterinary techs, and dentists, core instructor attributes improve learner outcomes:

  • Preparation — have equipment and scenarios ready; pre-brief and set clear objectives.
  • Passion — model enthusiasm and clinical excellence to motivate learners.
  • Patience — allow repeated practice and provide constructive feedback.
  • Managing classroom dynamics — set safety norms, debrief after simulations, and ensure psychological safety for learners to make and learn from errors.
  • Continuous learning — update curricula with current evidence and guidelines from agencies such as the CDC and NIH.

Geriatric Considerations and Relevant Resources

Although the focus of this article is pediatric IV therapy, it is important for clinicians who care for multiple age groups to recognize geriatric differences. Elderly patients commonly have fragile, tortuous veins, thin skin, and comorbidities like CHF and renal impairment that affect fluid selection and infusion rate. The National Center for Aging and Development (NCAD) and the National Institute on Aging (NIA) provide resources to inform practice in older adults; cross-referencing geriatric guidance can inform safe care transitions and mixed-age clinical settings.

Relevant resources for evidence-based practice include:

Procedural Variations: Central Lines, PICCs, and Intraosseous Access

Not all vascular access is peripheral. In pediatrics, central venous catheters, peripherally inserted central catheters (PICCs), and intraosseous access serve specific clinical needs:

  • Central venous access — for long-term vesicant therapy, total parenteral nutrition (TPN), and hemodynamic monitoring; increased risk of systemic infection and air embolism; requires provider authorization and sterile insertion technique.
  • PICC lines — often used for medium- to long-term therapy; may be placed by trained nursing teams or interventional radiology; securement and flush protocols are essential.
  • Intraosseous (IO) access — emergency access route for rapid fluid and medication administration in life-threatening situations when peripheral access cannot be obtained.

Emergency Recognition and Response

Rapid recognition of deterioration during IV therapy is critical. Signs of fluid overload and pulmonary edema — increased heart rate, elevated blood pressure, tachypnea, shortness of breath, diminished oxygen saturation — require immediate cessation of infusion, elevation of the head of bed, administration of oxygen, and prompt notification of the provider; in severe cases, activate the emergency response system.

Quality Assurance, Infection Control, and Institutional Policies

IV therapy safety is governed by institutional policy and national guidance. Regular competency assessments, adherence to sterile technique—chlorhexidine skin antisepsis for at least 1 minute per the lecture notes—proper line maintenance, and timely catheter removal when no longer indicated reduce risk. Nursing documentation (time, gauge, location, patient response) serves as both a continuity-of-care tool and legal protection. For allied clinicians and learners, review facility-specific competency checklists and collaborate with vascular access teams.

Pediatric-Specific Communication Strategies

Communicate with children at their developmental level. For toddlers and preschoolers, use simple, concrete language; for school-age children, explain the reason and steps; for adolescents, provide privacy and detailed rationales. Caregivers are partners — involve them as appropriate to reduce anxiety and improve cooperation.

Documentation and Legal Considerations

Chart accurately. Entries should include:

  • Who performed the procedure and when.
  • How many attempts were made; document complications or interventions.
  • Catheter specifics: gauge, length, and exact anatomic site.
  • Patient tolerance and education provided to caregiver and child.

Good documentation is the frontline defense in medicolegal situations and critical for continuity of care across care teams including student nurses, nurses, anesthesia techs, veterinary techs, and dentists who may be involved per institutional policies.

Training Pathways and Resources for Clinicians

Clinicians seeking competency in IV therapy can pursue classroom and hands-on training from accredited programs. Recommended educational partners include:

  • PCT Institute of Healthcare — coursework and clinical skills training relevant to phlebotomy, IV therapy, and allied health roles.
  • Phlebotomy Career Training — focused programs for phlebotomy and vascular access fundamentals useful for student nurses and allied staff.

Interprofessional education that includes student nurses, nurses, anesthesia techs, veterinary techs, and dentists helps build a culture of safety, shared protocols, and mutual respect for scope of practice boundaries.

Simulation and Competency-Based Assessment

Simulation-based education allows repeated, risk-free practice. Create scenarios that incorporate complications such as infiltration, extravasation, air embolism, and rapid decompensation. Use objective structured clinical examination (OSCE) checklists to assess insertion technique, sterile field maintenance, labeling, and documentation. Instructors should emphasize preparation, passion, and patience when supervising learners during simulation and bedside practice.

Practical Tips and Pearls for Clinical Practice

  • Always verify the IV order is current and authorized before initiating therapy.
  • Use the smallest gauge that will safely deliver therapy; preserve future access sites.
  • Perform chlorhexidine skin prep with a one-minute scrub when indicated and per facility policy.
  • Insert at a 15–28 degree angle with bevel up; observe for flashback to confirm venous entry.
  • Avoid pushing forcefully; if resistance on flush occurs, stop and reassess for proper placement.
  • Do not use the limb with an active IV for blood pressure cuff application or proximal tourniquet use.
  • When administering vesicants or irritants, monitor closely for extravasation and have an institutional extravasation protocol available.
  • Document time, gauge, site, number of attempts, complications, and patient response — this provides legal protection and continuity of care.
  • Admit knowledge gaps and consult supervisors or vascular access specialists when needed.

Frequently Asked Questions for Learners and Clinicians

Q: How long should I scrub the skin before IV insertion?

A: Use chlorhexidine as recommended and perform a vigorous scrub for approximately 1 minute before allowing skin to air dry. Follow institutional protocol regarding antiseptic choice for neonates and patients with contraindications.

Q: When is it safe to draw blood from an IV line that has been used to administer medications?

A: Follow facility-specific policy. Some medications require waiting periods, specific waste volumes, or avoidance of line draws altogether. If uncertain, draw from a peripheral site or consult pharmacy/laboratory for guidance.

Q: What if I get resistance when I try to flush an IV?

A: Stop the flush. Assess for kinking, catheter migration, infiltration, or a thrombotic occlusion. Do not force a flush. Repositioning the limb or gentle aspiration may help; consult prescriber if occlusion cannot be resolved.

Q: What are early signs of fluid overload in children?

A: Increased respiratory rate, tachycardia, hypertension, crackles on lung auscultation, and decreasing oxygen saturation are early indicators. Stop infusion and escalate care immediately.

Key References and Resources

For clinical updates, evidence reviews, and practice guidelines consult the following:

  • CDC — infection control and vascular access guidance.
  • NIH — clinical research updates and guidelines.
  • NLM — medical literature and drug information resources.
  • NIA — resources specific to aging and geriatric considerations relevant to mixed-age practice settings.
  • NAPTP — phlebotomy training resources and standards.
  • NTA — testing and certification resources.
  • PCT Institute of Healthcare — educational programs for allied health clinicians.
  • Phlebotomy Career Training — phlebotomy and IV practice resources.

Final Practical Scenarios for Learners

Students and clinicians should rehearse scenario-based learning:

  • A febrile infant requiring blood culture and IV antibiotics — practice site selection, sterile preparation, and careful documentation.
  • An adolescent receiving outpatient chemotherapy — review authorization, central versus peripheral access decisions, vesicant safety checks, and home-care education.
  • A dehydrated toddler needing maintenance fluids — calculate maintenance rate using 4-2-1, select appropriate microdrip settings, and monitor for tolerance.
  • An infant with collapsed peripheral veins — strategize alternative access including scalp veins, intraosseous access in emergencies, and early involvement of vascular access specialists.

This clinical guide integrates technical procedure, pharmacologic awareness, psychosocial teaching strategies, and professional responsibilities. It is designed for student nurses, nurses, anesthesia techs, veterinary techs, and dentists who require a comprehensive reference for pediatric IV therapy in varied clinical contexts. For hands-on training and certification pathways, consider the PCT Institute of Healthcare and Phlebotomy Career Training resources listed above.

Ready to Earn Your National IV Certification?

The National IV Association (NIVA) offers nationally recognized certification programs for nurses, EMTs, paramedics, and other licensed healthcare professionals. Train online, test when ready, and earn credentials that employers trust.

For foundational training in healthcare careers, visit the PCT Institute of Healthcare or explore certification options at Phlebotomy Career Training.
Enroll Now →

Categories
Uncategorized

IV Therapy in Elderly Patients: Special Considerations and Best Practices

IV Therapy in Elderly Patients: Special Considerations and Best Practices

By Nancy Kimmel (MSN, FNP, RN, PhD CHMM, MSN-FNP-BC)

Introduction

Intravenous (IV) therapy is a cornerstone of modern medical care — used not only for fluid resuscitation but for blood collection, chemotherapy, immunosuppressants, vitamin therapy, antibiotic delivery, electrolyte correction, and many other indications. In elderly patients, IV therapy requires heightened clinical awareness. Physiologic changes of aging, comorbid disease (e.g., heart failure, renal impairment, diabetes), polypharmacy, and fragile skin and veins increase the risk of complications and demand precise technique, careful selection of fluids and devices, and meticulous documentation.

This comprehensive article is written for student nurses, nurses, anesthesia techs, veterinary techs, and dentists — and for educators preparing clinicians working with older adults. It integrates clinical lecture concepts, professional responsibilities, infusion science, geriatric principles guided by organizations such as the National Institute on Aging (NIA) and the National Center for Aging and Development (NCAD), and pedagogical and psychosocial frameworks (including instructor strategies and Erikson’s stages) to support both clinical practice and teaching.

Why the Elderly Need Special Consideration

Older adults present unique challenges for IV therapy:

  • Vein fragility and decreased skin turgor increase risk of infiltration, extravasation, and catheter dislodgement.
  • Altered fluid balance and decreased cardiac and renal reserve increase sensitivity to rapid infusion and risk of fluid overload.
  • Higher prevalence of peripheral vascular disease, diabetes, and lymphedema influences site selection (avoid lower extremities/legs when possible).
  • Polypharmacy increases interaction risk and requires careful line management, scheduling, and flushing.
  • Cognitive impairment and sensory deficits may limit cooperation and necessitate clear communication and different positioning techniques.

Indications and Authorization

IV therapy is employed for many purposes in the elderly: blood collection for laboratory testing, administration of chemotherapy and immunosuppressants, vitamin therapy, emergency fluids, antibiotics, vasoactive medications, and transfusions. Because IV therapy can cause rapid systemic effects, authorization by a licensed provider (physician, advanced practice provider) is required. Always verify orders, indications, prescribed fluid type and rate, and medication compatibility prior to initiation.

Fundamentals and Anatomy for Safe Insertion

Understanding surface anatomy and the layers traversed by an IV catheter helps reduce complications. From superficial to deep, the layers include:

  • Epidermis
  • Dermis
  • Hypodermis (subcutaneous tissue)
  • Venous tunica (venous wall layers)

Common peripheral vein choices are located in the antecubital fossa: the cephalic, basilic, and median cubital veins. For a safe and patent peripheral IV, trace the vein for at least an inch to ensure a straight path and adequate length for catheter stabilization. Hands and lower limbs (legs) are generally avoided in the elderly unless necessary — legs are particularly contraindicated in patients with diabetes or peripheral arterial disease due to impaired healing and infection risk.

Technique: Positioning, Cleansing, and Insertion

Preparation and sterile technique are non-negotiable. The following steps summarize best practice:

  • Explain the procedure in plain language appropriate to the patient’s cognition (integrate Erikson’s reassuring approach for older adults — see later section).
  • Hand hygiene and appropriate PPE.
  • Apply tourniquet only to aid vein visualization — but never apply a tourniquet on an arm that already has an IV line.
  • Use chlorhexidine for skin antisepsis and clean for at least 1 minute at the insertion site to reduce local and bloodstream infection risk; allow to dry completely before insertion.
  • Choose site carefully: prioritize forearm veins; antecubital fossa veins (cephalic, basilic, median cubital) are appropriate when long dwell or bigger gauge is required; avoid the dominant arm for patients with dialysis fistulas.
  • Stabilize the vein and insert the catheter with the bevel up at an angle of about 15–28 degrees; lower the angle as you approach the lumen to reduce the risk of puncturing the posterior vein wall.
  • Watch for flashback (blood return) to confirm vessel entry. Do not advance so forcefully that you “go through” the vein.
  • If resistance is encountered while flushing, assume the catheter is not intravascular — stop, reassess, and remove if warranted.

Practical Tips for Fragile Veins

  • Consider smaller-gauge catheters (22–24 gauge) for fragile veins; refer to the catheter gauge table below.
  • Use stabilization devices, soft dressings, or anchoring techniques to reduce catheter movement.
  • Warm the extremity to dilate veins when appropriate; gravity and gentle stroking may help visualize a vein.
  • If peripheral access is not possible, evaluate risk/benefit of ultrasound-guided peripheral IV, midline catheter, or central access, keeping elderly physiologic reserve in mind.

IV Fluids and their Physiologic Effects

Choice of fluid matters. Fluids are classically described as isotonic, hypertonic, or hypotonic relative to plasma osmolarity and affect the distribution of water between intravascular and interstitial compartments.

Fluid Type Common Examples Physiologic Effect Common Indications / Elderly Considerations
Isotonic Normal saline (0.9% NaCl), Lactated Ringer’s Does not cause net movement of water between compartments; expands intravascular volume. Note: 0.9% NaCl is isotonic relative to plasma; body pH is 7.35–7.45 (though normal saline’s pH is slightly acidic, it is commonly used due to isotonicity and compatibility). Used for resuscitation, maintenance fluids. In the elderly, monitor for fluid overload, especially with CHF or renal impairment.
Hypertonic 3% NaCl, hypertonic saline mixtures Pulls fluid into the intravascular space from interstitium and cells; increases circulating volume and serum sodium. Used for severe hyponatremia or to reduce cerebral edema. Use caution: can precipitate volume overload in heart failure.
Hypotonic 0.45% NaCl (half-normal saline) Pushed fluid into cells and interstitial spaces from the vasculature; may cause edema. Used for cellular dehydration (e.g., hypernatremia). Avoid in patients at risk for increased intracranial pressure or with low vascular volume.

Rapid infusion in elderly, frail patients increases risk of cardiovascular decompensation: sudden increases in heart rate and blood pressure, shortness of breath, hypoxia — potentially precipitating pulmonary edema or a “code blue” event. Always consider reduced infusion rates and closer monitoring for older adults with compromised cardiac or renal function.

Drip Rates, Infusion Pumps, and Medication Safety

Precise control of infusion rate is essential in elderly patients. Infusion pumps with programmable rates are preferred for medications with narrow therapeutic ranges or for continuous infusions. For gravity drips, calculate drops-per-minute carefully and cross-check with a second clinician when doses are critical.

Key medication safety points:

  • Always read labels and verify the correct solution and medication — confusing saline with atropine, lidocaine, or other drugs can cause catastrophic outcomes. Ensure two-person verification when administering high-risk drugs.
  • Be aware of hypertonic vs hypotonic effects and how they interact with patient comorbidities (e.g., CHF, renal failure).
  • Allow appropriate dwell/clearance times for medication-dosed IVs before drawing blood samples from the same line to avoid contamination and inaccurate laboratory results. Follow institutional policy; commonly an infusion is paused and the line is flushed and discarded (a waste volume is withdrawn) before sampling, or blood is drawn from a different venipuncture site.
  • Do not use the same IV port for incompatible medications without flushing and verifying compatibility. Reference institutional medication compatibility guides and pharmacy when in doubt.

Signs of Infusion-Related Complications

Clinicians must be able to identify early signs of systemic and local complications:

  • Fluid overload: increased HR, rising blood pressure, shortness of breath, oxygen desaturation, jugular venous distension, crackles on lung auscultation.
  • Air embolism: sudden dyspnea, chest pain, hypoxia, hypotension — occurs with central line manipulations but may occur with poorly primed peripheral tubing.
  • Infiltration and extravasation: pain, swelling, coolness, blanching at the insertion site; extravasation of vesicant drugs can cause tissue necrosis.
  • Catheter-related bloodstream infection (CRBSI): fever, chills, localized erythema, purulence at insertion site — strict aseptic technique and timely catheter removal help prevent infection.
  • Phlebitis: erythema, warmth, tenderness along vein path; may be chemical (due to irritant solution), mechanical (catheter movement), or infectious.

Device Selection and Catheter Gauge Guidance

Selecting the proper catheter gauge balances the need for flow rate and vein size. The table below provides common guidance for peripheral IV catheter selection in the elderly.

Gauge (Fr) Typical Use Elderly Consideration
14–16G Major trauma, rapid blood transfusion, emergency resuscitation Rarely used in elderly unless emergent; large bore may damage fragile veins.
18G Surgery, blood transfusion Use cautiously; if blood transfusion required, choose site with adequate vein caliber.
20G General IV therapy, antibiotics Common choice when vein quality allows.
22G Infusions for smaller veins, longer-term peripheral access Often ideal for frail older adults with small, fragile veins.
24G Infusions for neonates, frail elderly with minimal flow needs Useful when veins are very fragile; limit to low-viscosity fluids.

Site Management, Dressings, Securement, and Changing Policy

Proper site care reduces mechanical and infectious complications:

  • After insertion, secure the catheter with an appropriate securement device and a transparent semipermeable dressing that allows inspection. Change dressings per institutional policy or sooner if soiled, loose, or wet.
  • Assess the site at least every shift and before any medication administration: look for erythema, warmth, swelling, and drainage; palpate for tenderness or cord formation.
  • Peripheral IVs should be removed and re-sited if signs of phlebitis, infiltration, or infection occur, or if they are no longer needed.

Drawing Blood from an IV: Timing and Technique

Drawing blood from an existing IV line can be convenient but carries risks of contamination and inaccurate values if done improperly. Important points:

  • Never draw from a line that is infusing medications known to alter test results unless the infusion is paused and a validated protocol is followed.
  • Wait appropriate times for medication-dosed IVs before drawing blood — follow hospital policy: often this involves stopping the infusion, waiting a specified time (commonly several minutes), flushing with saline, discarding a waste volume, and then drawing test samples from a port proximal to the infusion. When in doubt, obtain a fresh venipuncture sample.
  • Do not draw blood through tubing that contains incompatible medications or hypertonic solutions.

Professional Responsibilities, Documentation, and Scope

Proper documentation serves both clinical continuity and legal protection. Chart the following elements consistently:

  • Time and date of insertion
  • Catheter gauge and type
  • Exact anatomical location (e.g., right antecubital fossa, cephalic vein, 2 cm proximal to antecubital crease)
  • Number of attempts and complications
  • Patient response (pain, distress) and analgesia or comfort measures used
  • Type and rate of fluids/meds ordered, infusion pump settings, and any changes
  • Assessment findings at dressing changes and routine site checks

Medical assistants (MAs), student nurses, and other trainees must work within their local scope of practice. If an assignment requires skills beyond your credentialing — for example, initiating an IV when it is out of scope for your role — consult your supervisor immediately. Professional integrity includes admitting when you lack knowledge and seeking appropriate oversight. This preserves patient safety and reduces risk.

Complication Management

Infiltration and Extravasation

Signs: swelling, coolness, pain, or burning at site; decreased or stopped infusion flow.

Actions:

  • Stop infusion immediately.
  • Disconnect tubing and remove catheter cautiously per policy.
  • Elevate limb, apply warm or cold compress depending on solution (follow local extravasation protocol; vesicants often require specific antidotes and cold/warm therapy).
  • Document treatment and notify prescribing clinician for potential further actions, including antidote administration.

Suspected Air Embolism

Signs: sudden respiratory distress, chest pain, hypotension, altered mental status. Actions: place patient in left lateral decubitus and Trendelenburg if a central line is involved, call for emergency help, administer oxygen, and prepare for advanced resuscitation.

Catheter-Related Bloodstream Infection

Maintain high suspicion with fevers, chills, and sepsis signs. Remove device if infection suspected, obtain blood cultures (both peripheral and from catheter if available), and start empiric antibiotics per protocol after consulting the prescriber.

Calculating Drip Rates: Practical Example and Safety Checks

When gravity infusion is used, calculate drops-per-minute carefully. Example:

  • Order: 500 mL normal saline over 4 hours.
  • Rate in mL/hr = 500 mL / 4 hr = 125 mL/hr.
  • If tubing drop factor is 20 drops/mL: drops/min = (125 mL/hr × 20 drops/mL) / 60 min = 41.7 ≈ 42 drops/min.

Verify calculations with a second clinician for critical infusions. For elderly patients, consider using pumps for controlled, constant rates and incorporate alarms for occlusion or air-in-line detection.

Education and Communication Strategies for Older Adults

Effective communication and patient-centered care are especially important for older adults, many of whom may have sensory, cognitive, or psychosocial needs. Use plain language, allow time for questions, speak slowly, and verify understanding. For patients with cognitive impairment, involve caregivers and follow advance directives.

Integrating Erikson’s Psychosocial Stages into Teaching

Erikson’s eight stages of psychosocial development offer a useful framework for tailoring education and communication to older adults. The final stage — integrity vs. despair — is particularly relevant in geriatrics. Older adults may be reflecting on life achievements and losses; clinicians and educators who acknowledge life perspective can enhance trust and adherence.

Practical application for clinicians and instructors:

  • Show respect for life experience and dignity — validate concerns and autonomy.
  • Acknowledge fears about invasive procedures and potential loss of independence.
  • Offer choices where possible (e.g., which arm to use, comfort measures) to preserve a sense of control.
  • For student nurses and trainees, integrate Erikson’s framework into patient education role-plays to practice empathy and motivational communication.

Teaching and Instructor Principles: Preparation, Passion, Patience

For educators teaching IV therapy — whether to student nurses, nursing assistants, anesthesia techs, veterinary techs, or dentists expanding skills — the instructor role is multifaceted. Instructor best practices include:

  • Preparation: create clear learning objectives, structured demonstrations, and competency checklists. Ensure simulation equipment and supplies are available and working.
  • Passion: model enthusiasm and professional commitment; students are more engaged when instructors demonstrate real-world relevance.
  • Patience: skill acquisition takes time. Scaffold learning from theory to supervised practice to independent performance.
  • Managing classroom dynamics: encourage peer-assisted learning, manage time effectively, and address anxiety in learners by normalizing mistakes and focusing on corrective feedback.
  • Continuous learning: maintain currency with evolving guidelines (CDC, NIH, NLM resources), and promote evidence-based practice among learners.

Geriatric Guidance and Evidence Sources

Clinical decisions for IV therapy in older adults should integrate evidence and guidelines. Reliable resources include:

  • CDC — infection prevention and safety guidelines
  • NIH — research and clinical practice updates
  • NLM (National Library of Medicine) — literature searches and clinical resources
  • NIA (National Institute on Aging) — aging-specific clinical considerations and patient education
  • Professional societies such as the NAPTP and the NTA provide specialty-specific guidance (verify site-specific acronyms and resources).
  • Geriatric-development organizations like the National Center for Aging and Development (NCAD) provide geriatric-specific care frameworks and resources for educators and clinicians.

Audience-Specific Considerations

Although many principles are universal, some professions require tailored instruction and scope awareness. Below are practical notes for student nurses, nurses, anesthesia techs, veterinary techs, and dentists.

Student Nurses

  • Focus on mastering aseptic technique, anatomy, and safe insertion angles (15–28 degrees, bevel up).
  • Document meticulously: time, gauge, location, and patient response are critical entries for legal protection and continuity.
  • Seek supervised practice and recognize the importance of admitting limitations; escalate to preceptors when needed.

Nurses

  • Maintain competency with ongoing training and simulation; be the team resource for IV troubleshooting and venous assessment in elderly patients.
  • Use clinical judgment for site selection — avoid hands and legs when possible, especially for diabetic patients or those with lymphedema.

Anesthesia Techs

  • Coordinate with anesthesia providers for vascular access needs, especially intraoperative fluid requirements and vascular access for hemodynamic monitoring.
  • Be comfortable with rapid infusion equipment, tubing setup, and ensuring that lines are primed to avoid air embolism.

Veterinary Techs

  • While human anatomy differs, the clinical principles of asepsis, vein selection, and careful site management are applicable — especially in geriatric veterinary patients with fragile veins.
  • Adapt communication strategies for owners and use Erikson-inspired approaches when discussing end-of-life or complex treatment choices for older animals’ human caregivers.

Dentists

  • Dentists engaged in sedation or IV medication administration must be proficient in IV safety, emergency recognition (e.g., aspiration, allergic reactions), and cardiopulmonary resuscitation (CPR).
  • Use clear policies regarding who may place IVs in dental settings and ensure credentialing and ongoing competency.

Special Considerations for Diabetic and Vascular Disease Patients

Diabetes and peripheral vascular disease increase the risk of infection, delayed healing, and poor outcomes from IV site complications. Prefer upper extremity forearm veins, avoid lower extremities (legs), and carefully assess for neuropathy and arterial insufficiency. When in doubt, consult vascular or wound care specialists and involve multidisciplinary teams.

Quality Assurance, Competency, and Continuous Learning

Organizations and healthcare facilities must maintain competency-based training programs, including simulation labs, skills checklists, and periodic recertification. Encourage clinicians to review current literature via the NLM/NIH and to use reputable training programs for foundational venipuncture and IV skills, such as the PCT Institute of Healthcare and Phlebotomy Career Training for foundational phlebotomy and IV competencies. Links for reference:

Legal, Ethical, and Documentation Imperatives

Accurate documentation is not optional — it is a legal safeguard. Chart insertion details (time, gauge, location), number of attempts, patient tolerance, and any interventions taken for complications. If a complication occurs, document the clinical findings, notification of the prescriber, and the instructions received. When teaching clinicians, emphasize that documentation is essential professional behavior and a cornerstone of patient safety and risk management.

Practical Checklists and Protocols

Consider adopting procedural checklists to ensure no steps are missed. A basic IV insertion and monitoring checklist for elderly patients could include:

  • Confirm written order and indication.
  • Gather supplies; verify catheter size and sterile dressing availability.
  • Perform hand hygiene and don PPE.
  • Assess both arms; select site avoiding hand/leg when possible; trace vein for ≥1 inch.
  • Apply tourniquet temporarily (not on arm with existing IV).
  • Cleanse with chlorhexidine for 1 minute and allow to dry completely.
  • Insert at 15–28° with bevel up; observe for flashback.
  • Stabilize catheter, secure dressing, and label with date/time/gauge/initials.
  • Set infusion device or calculate drip rate; verify with second clinician for critical infusions.
  • Document insertion details and plan for reassessment.

Integration with Hospital Policies and Multidisciplinary Teams

IV therapy in the elderly benefits from multidisciplinary oversight. Pharmacy consultation for medication compatibility and dosing adjustments, nursing leadership for training and policy, and collaboration with geriatric specialists, wound care, and vascular access teams improve outcomes. Use facility policies and evidence-based protocols when deciding on midline or central catheter placement versus repeated peripheral attempts.

Teaching Tools for Instructors: Applying Pedagogy to Clinical Skill Teaching

Instructors should build lesson plans that incorporate:

  • Demonstration followed by deliberate practice with feedback.
  • Simulation scenarios reflecting common geriatric complications (e.g., fluid overload, phlebitis, fragile veins that infiltrate).
  • Reflection sessions integrating Erikson’s psychosocial principles and the emotional aspects of care for older adults.
  • Assessment rubrics that include both technical skill and communication (e.g., informed consent, demonstration of empathy).

Resources and Further Reading

Reliable resources for best practice include the Centers for Disease Control and Prevention (CDC), the National Institutes of Health (NIH), the National Library of Medicine (NLM), and the National Institute on Aging (NIA). Professional training organizations and accredited phlebotomy programs such as the PCT Institute of Healthcare and Phlebotomy Career Training offer competency-based courses that reinforce safe technique and documentation practices.

Appendix: Quick Reference Tables

Common Complications and Immediate Actions

Complication Key Signs Immediate Action
Infiltration Swelling, coolness, decreased infusion Stop infusion, remove catheter, elevate limb, document, notify prescriber
Extravasation (vesicant drug) Severe pain, tissue blanching, blistering Stop infusion, leave catheter in place (for antidote), consult prescriber/pharmacy, follow extravasation protocol
Phlebitis Redness, warmth, palpable cord Remove catheter, elevate limb, apply warm compress, document
Air embolism Sudden dyspnea, hypotension, chest pain Call emergency response, position patient left lateral decubitus/Trendelenburg if appropriate, administer oxygen
Fluid overload Dyspnea, crackles, hypoxia, JVD Slow/stop infusion, assess vitals, notify provider, administer diuretics as ordered

Checklist for Safe IV Practice in Elderly Patients

Step Yes/No
Order confirmed and indication appropriate
Patient identification and informed consent obtained
Supplies prepared and checked
Chlorhexidine used for 1 minute and allowed to dry
Catheter inserted at 15–28° with bevel up; flashback confirmed
Catheter secured, dressing applied, labeled with date/time/gauge
Infusion pump settings verified and second-checked for critical meds
Documented: time, gauge, location, patient response

References and Further Training

Clinicians and educators should maintain an evidence-informed bibliography drawn from peer-reviewed journals, institutional policy manuals, and authoritative public health sources. Consult the CDC, NIH, NLM, and NIA for updates and training materials. For competency-based phlebotomy and IV training programs, consider reputable training providers such as the PCT Institute of Healthcare and Phlebotomy Career Training to support foundational skills for student nurses, MAs, and novice clinicians.

Throughout all practice and teaching activities, remember the cardinal rules: use sterile technique, select the appropriate device and site for the individual patient, monitor closely for complications, document thoroughly, and consult when care is beyond your scope. These principles protect our elderly patients’ safety and dignity while supporting clinicians — student nurses, nurses, anesthesia techs, veterinary techs, and dentists — in delivering high-quality, compassionate IV care.

Ready to Earn Your National IV Certification?

The National IV Association (NIVA) offers nationally recognized certification programs for nurses, EMTs, paramedics, and other licensed healthcare professionals. Train online, test when ready, and earn credentials that employers trust.

For foundational training in healthcare careers, visit the PCT Institute of Healthcare or explore certification options at Phlebotomy Career Training.

Enroll Now →

Categories
Uncategorized

Immunization Administration: Expanding Your Scope of Practice as an IV Tech

Immunization Administration: Expanding Your Scope of Practice as an IV Tech

By Nancy Kimmel (MSN, FNP, RN, PhD CHMM, MSN-FNP-BC)

As an experienced clinician and educator, I have guided many allied health professionals through the transition from task-based procedural roles to expanded clinical responsibilities. This article is written for IV technicians who seek to expand into immunization administration, and for the professional audiences that partner with IV techs: student nurses, nurses, anesthesia techs, veterinary techs, and dentists. The material that follows blends the clinical mechanics of vascular access and IV medication/fluid management with the unique demands, legal responsibilities, and educational principles required to add immunization administration competently and safely into your scope of practice.

Why IV Techs Are Well Positioned to Add Immunizations

IV technicians already possess several foundational competencies that overlap with immunization administration:

  • Patient assessment and vascular access skills, including palpation and vein selection.
  • Sterile technique, aseptic preparation (including appropriate skin antisepsis), and injection mechanics.
  • Competence with medication labels, concentration, and routes of administration — habits that translate into safe vaccine handling and administration.
  • Familiarity with charting, documentation standards, and infection control policies.

However, vaccines have unique storage, documentation, legal, and patient education requirements. Expansion of practice must be deliberate, governed by facility policy, state scope of practice regulations, and appropriate education — often including competency assessments, certification, and physician authorization or standing order protocols.

Clinical Foundation: IV Therapy Principles That Inform Safe Immunization Practice

Many of the principles learned in IV therapy apply directly to immunization administration, but there are also important differences to be understood and respected.

Sterile Technique: From Chlorhexidine to the One-Minute Cleanse

Aseptic preparation is non-negotiable. In IV therapy, we use chlorhexidine gluconate for skin antisepsis and allow the site to air dry thoroughly. For IV insertion, many training protocols specify a one-minute (60 second) contact time for chlorhexidine to achieve optimal skin antisepsis prior to cannulation. This same respect for contact time applies when preparing sites for intramuscular (IM) or subcutaneous (SC) vaccine injections. Always follow manufacturer and facility policy — but the concept is the same: appropriate antiseptic agent and adequate dwell/contact time reduce the risk of local infection and downstream systemic complications.

Vein and Injection Site Selection

IV insertion teaches you to palpate and “trace” a vein for approximately one inch to confirm continuity and direction. For IVs, common antecubital fossa veins include the cephalic, basilic, and median cubital veins. For vaccine administration (mostly intramuscular), the common adult sites are the deltoid muscle (preferred for most adult immunizations), the anterolateral thigh for infants and young children, or the dorsogluteal or ventrogluteal sites where indicated. IV techs expanding into immunizations must learn muscle anatomy, appropriate landmarking, and dosage limits for each site.

Needle Mechanics: Angle, Bevel, Flashback, and Prevention of Complications

Typical IV catheter insertion requires a 15–28 degree angle with the bevel up. You watch for flashback to confirm vessel entry. The lesson here has direct bearing on injection technique: understand and respect the angle appropriate for the route (e.g., 90 degrees for intramuscular injections in most adults, 45 degrees for subcutaneous injections in thin patients when indicated). Don’t push too forcefully; when inserting an IV you risk going through the vein if you push too hard — the same attention to tactile feedback is necessary for injections to avoid penetrating unwanted tissue planes.

Resistance on Flush Equals You Are Not in the Lumen

A quick, simple rule: if there is resistance when you attempt to flush, you are not in the vein (or you have an occlusion). IV techs are accustomed to this check; it becomes an immediate safety check when administering medications and when verifying that an IV is patent prior to vaccine-related procedures or drawing labs. For vaccine administration specifically (IM or SC), this rule translates into aspirating when indicated by facility policy (aspiration prior to injection is generally not recommended for routine immunizations, per CDC guidance, unless specified) and observing for patient pain or resistance that might indicate incorrect needle placement.

Fluids, Drip Rates, and Medication Knowledge: Avoiding Harm When Managing Therapy

IV therapy teaches the consequences of incorrect solution selection or infusion rate. As IV technicians expand into vaccine administration, many of these principles remain essential — especially when caring for patients who are concurrently receiving IV fluids, chemotherapy, or immunosuppressants.

Isotonic, Hypertonic, and Hypotonic Solutions — Practical Implications

Solution Type Examples Primary Physiologic Action Clinical Use and Risk
Isotonic 0.9% Sodium Chloride (Normal Saline) Matches extracellular osmolarity; minimal net fluid shift Used for volume resuscitation; generally safe. Note: verify label carefully (NaCl vs other meds).
Hypertonic 3% NaCl, Albumin (concentrated) Pulls fluid from intracellular/interstitial compartments into vascular space Treats edema and hyponatremia in controlled settings; risky in CHF and fragile patients — can precipitate fluid overload.
Hypotonic 0.45% NaCl (Half Normal) Pushes fluid into cells and interstitial space Used in dehydration with hypernatremia; can worsen hypotension and cellular edema if misused.

Rapid infusion in fragile patients can precipitate acute cardiovascular compromise — increased heart rate, increased blood pressure, shortness of breath, hypoxia, pulmonary edema — events that can escalate to a code blue. IV techs must be vigilant when immunizing patients who are receiving IV fluids or medications. For example, drawing a patient from a chair to initiate an immunization when they are actively receiving a hypertonic bolus is unsafe without physician approval.

Label Literacy: Read Every Label — Saline vs. Atropine vs. Lidocaine

One of the key safety habits is to read medication labels aloud when preparing a medication or vaccine. Confusing similar-looking vials or syringes can have catastrophic consequences. Drugs such as atropine and lidocaine carry cardiovascular and neurologic implications if administered in error. Vaccines have distinct labeling and storage requirements. This is a discipline that IV techs already practice with IV medications — apply the same diligence to vaccine preparation.

Compatibility and Timing: When to Draw Blood and When to Administer Vaccines

Coordinate with the care team. Some medications are dosed through an IV that can contaminate blood draws (e.g., certain vasoactive agents). The lecture notes emphasize “wait appropriate times for medication-dosed IVs before drawing blood.” Similarly, facility policy will specify when to stop an infusion before drawing serology or vaccine titers — often to avoid contamination by IV medications. When possible, draw labs from a separate site or after stopping the infusion and flushing per policy and manufacturer guidance. Never apply a tourniquet to an arm with an active IV line — it can cause retrograde infiltration and alter medication delivery.

Immunization-Specific Clinical Skills for IV Techs

Administering vaccines requires more than the mechanical ability to push a syringe. It demands knowledge of vaccine storage/handling (the cold chain), routes of administration, contraindications, and emergency response to vaccine reactions (e.g., anaphylaxis). Below are the essential competencies.

Vaccine Storage and Handling (Cold Chain)

Vaccines are biological products that require precise temperature control. Improper storage can render a vaccine ineffective or dangerous. As an IV tech expanding scope into immunizations, become conversant with:

  • Refrigeration temperatures (commonly 2–8°C for many vaccines) and freezer requirements for some formulations.
  • Continuous temperature monitoring, documentation, and response to excursions.
  • Proper transport and handling for off-site clinics or mobile immunization events.

Resources such as the CDC Vaccine Storage and Handling Toolkit (link below) are indispensable for establishing facility protocols and for your own learning. See CDC guidance for details: CDC.

Routes of Administration and Landmarking

Vaccine Route Common Sites Needle Angle & Gauge (Typical) Clinical Considerations
Intramuscular (IM) Deltoid (adults), Anterolateral thigh (infants/young children) 90°; gauge 22–25 (age and site dependent) Do not give in gluteal muscles for infants; use proper landmarking for deltoid to avoid radial nerve injury.
Subcutaneous (SC) Posterior upper arm, anterolateral thigh 45°; gauge 23–25 Used for select vaccines (e.g., MMR in some protocols); avoid excessive massage post-injection.
Intradermal (ID) Inner forearm (Mantoux) 10–15°; small-gauge tuberculin syringe Used for TB testing and select experimental vaccine protocols; requires specialized training.

Contraindications and Special Populations

Some immunizations are contraindicated or require caution:

  • Severely immunocompromised patients should not receive live attenuated vaccines. Many patients on chemotherapy or high-dose corticosteroids fall into this category — consult the treating physician and refer to NIH/NIAID resources when in doubt.
  • Acute moderate-to-severe illness with or without fever is a precaution for vaccination until recovery.
  • History of severe allergic reaction (anaphylaxis) to a vaccine component is a contraindication.

These considerations are especially pertinent when administering vaccines to patients receiving IV chemotherapy, immunosuppressants, or other treatments that affect immune function — areas IV techs commonly encounter. Work collaboratively with prescribers and refer to authoritative sources, including NLM and NIH.

Recognition and Immediate Management of Vaccine Adverse Reactions

Be prepared for acute reactions, including anaphylaxis. The basics:

  • Observe vaccine recipients for the recommended post-vaccination period (typically 15 minutes; 30 minutes for those with prior severe allergic reactions).
  • Know the location and dosing of emergency medications, especially intramuscular epinephrine; understand airway management basics, oxygen administration, and when to call for higher-level support.
  • Document the event meticulously and notify the supervising clinician immediately.

Scope of Practice, Legal Responsibilities, and Professional Documentation

Expanding scope of practice to include immunizations requires an understanding of legal boundaries, institutional credentialing, and meticulous documentation. This section covers the professional responsibilities that protect both the patient and the practitioner.

Authorization and Supervision: Know Your Limits

Physicians, advanced practice providers, and facility leadership determine who is authorized to administer vaccines. Many facilities use standing orders or protocol-based authorizations that allow trained IV techs to vaccinate under defined conditions. However:

  • Always verify state and facility regulations. Some states require certification or licensure beyond basic IV technician training to administer vaccines.
  • Medical assistants (MAs) and other allied health personnel must consult supervisors when questions arise that exceed their training.
  • Admit when you lack knowledge. Saying “I don’t know” and seeking clarification from a nurse, pharmacist, or physician is professional and protective.

Charting: Time, Gauge, Location, Response — Your Legal Shield

Charting is not a bureaucratic task; it is legal protection and continuity of care. When you administer an immunization, document:

  • Vaccine name, manufacturer, lot number, expiration date.
  • Route, site, needle gauge and length, and the exact anatomical location (e.g., “Left deltoid, 2 cm below acromion”).
  • Time and date of administration.
  • Patient response: immediate observations during the post-vaccination observation window and any adverse reactions.
  • Authorization source: physician order, standing order, or protocol name/ID.

Attentive documentation is particularly important when immunizations occur in complex clinical contexts — for example, a patient who is also receiving IV chemotherapy or immunosuppressant infusions. Charting that you checked for active IV infusions, that you didn’t apply a tourniquet to an arm with an IV line, and that you verified medication labels prior to preparation will be essential if questions or adverse events arise.

Practical Teaching and Instructional Design for IV-Tech-to-Immunizer Training

If you are an instructor training IV techs to administer vaccines, adopt a learner-centered approach that emphasizes preparation, passion, patience, classroom management, and continuous learning. These are not soft skills; they are core instructional competencies that improve patient safety.

Preparation

Prepare curriculum that includes didactic content (vaccine science, routes of administration, contraindications), skill labs (landmarking, injections on simulators), emergency response drills, and competency checklists. Integrate resources like the CDC immunization schedules and facility-specific protocols.

Passion

Demonstrate enthusiasm for lifelong learning. Your attitude models professional behaviors that learners will emulate — from respect for infection control to meticulous documentation.

Patience

Learners develop technical competence at different paces. Allow repeated practice in a low-risk setting and provide constructive, objective feedback.

Managing Classroom Dynamics

Create psychologically safe learning environments. Use case-based scenarios that reflect interprofessional practice (including student nurses, nurses, anesthesia techs, veterinary techs, and dentists) so learners appreciate the broader clinical context of immunization delivery.

Continuous Learning

Immunization science evolves (new vaccines, revised schedules, and altered contraindications). Encourage learners to consult authoritative sources (CDC, NIH, NLM) and make continuing education a criterion for maintaining competency.

Integrating Erikson’s Psychosocial Theory into Vaccination Education and Patient Interaction

Erikson’s eight stages of psychosocial development provide a framework for tailoring communication and education to patients across the lifespan. As an educator or clinician administering vaccines, framing your approach using Erikson’s stages helps you meet emotional and developmental needs while ensuring comprehension and adherence.

Applying Erikson by Stage — Practical Examples

  • Trust vs. Mistrust (Infancy): For infants and parents, establish trust by explaining procedures gently, demonstrating competence, and calming caregivers. Parental trust is crucial for vaccine acceptance.
  • Autonomy vs. Shame/Doubt (Toddlers): Provide simple choices (hold my hand vs. sit on lap) to increase participation and reduce trauma.
  • Initiative vs. Guilt (Preschool): Use age-appropriate language and allow children to ask questions; play-based distraction reduces anxiety.
  • Industry vs. Inferiority (School Age): Provide praise for cooperation, explain the “why” behind vaccines in concrete terms, and use badges or stickers for positive reinforcement.
  • Identity vs. Role Confusion (Adolescents): Engage adolescents in decision-making. Respect privacy and autonomy; discuss risks/benefits candidly.
  • Intimacy vs. Isolation (Young Adults): Discuss occupational risks (e.g., for anesthesia techs and dentists), travel, and reproductive planning if relevant.
  • Generativity vs. Stagnation (Middle Adulthood): Explain how vaccination protects families and communities; address concerns that may delay immunization.
  • Integrity vs. Despair (Older Adults): Acknowledge life experience, discuss age-specific vaccines (influenza, pneumococcal, zoster), and include geriatric considerations described below.

Using Erikson’s lens transforms a routine injection into a developmentally tailored interaction that respects patient dignity and increases acceptance. This is especially relevant for student nurses and other trainees learning how to communicate effectively across age groups.

Geriatric Care Considerations: Frailty, Comorbidity, and the Older Adult

Older adults are a priority population for many vaccines, but they also present unique physiologic vulnerabilities. Integrate guidance from the National Institute on Aging (NIA) and geriatric resources like the National Center for Aging and Development (NCAD) when training or providing care.

Physiologic Changes That Affect Immunization

  • Immunosenescence: Attenuated immune response may reduce vaccine efficacy — higher-dose or adjuvanted formulations (e.g., high-dose influenza vaccines) may be recommended.
  • Skin and Muscle Changes: Decreased subcutaneous fat and thinning muscle mass may affect landmarking for intramuscular injections; needle length must be chosen carefully.
  • Polypharmacy and Comorbidities: Blood thinners, heart failure, and renal dysfunction alter risk profiles for certain vaccines or for post-injection bleeding or volume overload.
  • Mobility and Sensory Deficits: Ensure accessibility, clear communication, and sufficient time for post-vaccination observation.

For authoritative guidance on aging-related immunization policy and research, consult the NIA: NIA and review geriatric resources from NCAD when designing educational programs for IV techs who will care for older adults.

Interprofessional Considerations: Working with Student Nurses, Nurses, Anesthesia Techs, Veterinary Techs, and Dentists

Immunization programs are inherently interprofessional. IV techs who expand into immunization administration will frequently collaborate with student nurses, registered nurses, anesthesia techs, veterinary techs, and dentists. Each of these professionals brings different strengths and considerations:

  • Student nurses: Often in clinical rotations; require supervision and structured feedback. Use opportunities to teach vaccine documentation and the rationale behind immunization schedules.
  • Nurses: As clinical leaders, RNs often supervise immunization programs. Maintain clear lines of communication about competence, authorization, and patient triage.
  • Anesthesia techs: May assist in perioperative vaccination programs; understand preoperative vaccine timing and interactions with sedatives or anesthesia medications.
  • Veterinary techs: Experienced in injections for animals; while not interchangeable with human immunization training, their injection mechanics and knowledge can accelerate skill acquisition with appropriate human-focused education and legal authorization.
  • Dentists: Dental offices increasingly offer vaccines (e.g., influenza, COVID-19 in some jurisdictions). Coordinate with dentists on patient screening, emergency readiness, and documentation interoperability with public health registries.

Ensure that role clarity, credentialing, and communication protocols are established. When training interdisciplinary trainees, incorporate simulation with role-play to rehearse coordination during adverse events.

Competency-Based Curriculum: From Classroom to Clinic

Design competency-based pathways that guide IV techs from basic knowledge to independent practice under protocol. Core components should include:

  • Didactic modules: vaccine science, contraindications, storage/handling, documentation requirements, and legal aspects.
  • Skill labs: landmarking for IM/SC/ID injections, emergency response drills (anaphylaxis), using simulators for practice.
  • Supervised clinical practice: a preceptor model with defined numbers of observed and supervised vaccinations before independent practice.
  • Assessments: objective structured clinical examinations (OSCEs), written tests, and annual competency demonstrations.

For formal course options and allied health training resources, consider reputable training organizations such as PCT Institute of Healthcare and Phlebotomy Career Training, which provide curricula and certification pathways complementary to immunization training initiatives.

Quality Assurance, Reporting, and Regulatory Follow‑Up

Programmatic quality assurance ensures vaccine clinic safety and legal compliance. As part of quality processes:

  • Monitor vaccine temperature logs and maintain an inventory of lot numbers/expiry dates.
  • Report adverse events to appropriate surveillance systems per CDC and local public health guidance.
  • Participate in periodic chart audits to ensure documentation completeness and adherence to standing orders.
  • Engage in continuing education and re-certification as required by facility policy or state law.

External resources and reporting guidance are available from the CDC and related public health agencies (CDC; NLM). If your program includes phlebotomy services or specimen collection associated with immunization studies or titers, coordination with organizations such as the National Association of Phlebotomy Technicians and Professionals (NAPTP) and other professional testing bodies is advised.

Addressing Common Safety Pitfalls and Clinical Pearls

This section synthesizes the practical cautions and “nuts-and-bolts” pearls that emerge when IV techs expand into immunizations.

  • Never apply a tourniquet to an arm with an active IV line. This can cause backflow, infiltration, and inaccurate assessments.
  • Always verify that a scheduled vaccine is indicated for the patient — consult immunization schedules and the patient’s health history for prior reactions or contraindications.
  • When administering vaccines to patients receiving IV fluids or medications, communicate with the team and avoid site conflicts. For example, avoid injecting into a limb with a new IV insertion or a dialysis access site.
  • Confirm before drawing blood from a limb with an IV line; if unavoidable, follow policy for stopping and flushing infusions and document timing meticulously.
  • Observe for and be prepared to treat or escalate for allergic reactions. Establish a clear emergency action plan before starting a mass immunization clinic.
  • Maintain impeccable documentation: vaccine name, lot, expiration, route, site, time, and observation findings are essential medico-legal records.

Resources for Ongoing Education and Evidence-Based Guidance

The practice of immunization is dynamic. Below are essential resources that IV techs and their supervising clinicians should consult regularly:

  • CDC — vaccination schedules, VFC program, vaccine storage & handling
  • NIH — immunology and vaccine research resources
  • NLM — PubMed, drug information
  • NIA — aging and immunization considerations
  • NAPTP — phlebotomy/professional testing organizations
  • NTA — national testing/credentialing bodies (verify jurisdictional relevance)
  • PCT Institute of Healthcare — training resources for allied health professionals
  • Phlebotomy Career Training — phlebotomy and specimen collection training

Special Considerations for Unique Populations and Settings

Different clinical environments and populations demand adaptations in approach and policy. Consider the following examples:

Patients Receiving Chemotherapy or Immunosuppressants

These patients are simultaneously among the most in need of some vaccines (e.g., influenza) and the most vulnerable to live vaccines. Consult with the prescribing oncologist or specialty clinician. Timing is critical — vaccinate prior to initiating immunosuppression when possible, and avoid live vaccines during active immunosuppression. IV techs must develop competency in identifying immunosuppressed states and escalating to the responsible clinician.

Mass Immunization Clinics and Pop-Up Sites

Mass clinics require robust planning: cold chain logistics, emergency response readiness, adequate staffing with trained personnel (including supervising nurses), and clear documentation processes. IV techs are valuable staff members in these settings — particularly for triage, injection stations, monitoring, and documentation — but they must be supported with clinical oversight and clear protocols.

Veterinary Clinics and Dental Offices

Veterinary techs may transition to human immunization roles with formal human health training. Dental offices are increasingly offering vaccinations; dentists and their teams need training in patient screening, injection technique, and medical emergency response. Interprofessional partnerships expand access but must be accompanied by documented training and scope-of-practice clarity.

Program Development Checklist for Facilities Adding IV Tech Immunizers

Use this checklist when proposing or operationalizing a program that authorizes IV techs to deliver vaccines:

  • Confirm state and facility scope-of-practice laws and credentialing requirements.
  • Develop a competency-based training curriculum (didactic, skills lab, supervised clinical practice).
  • Establish standing orders or physician authorizations and clarify escalation pathways.
  • Create a robust cold chain and vaccine storage policy with monitored logs.
  • Standardize documentation templates: vaccine lot, site, route, time, and post-vaccination observation.
  • Plan for emergency response: medications (epinephrine), oxygen, protocols, and links to higher-level care.
  • Audit and QA processes: chart audits, temperature logs, and adverse event reporting workflows.
  • Engage in interprofessional training that includes student nurses, nurses, anesthesia techs, veterinary techs, and dentists to foster mutual understanding and respect for roles.

Case Studies — Practical Scenarios for Training and Reflection

Case 1: The Elderly Patient on Diuretics

An 82-year-old with congestive heart failure is scheduled for influenza vaccination while receiving IV normal saline for mild dehydration. As an IV tech, you must:

  • Check medication orders and consult the nurse/physician about the timing of the vaccine relative to fluid management.
  • Avoid injecting into an arm with a freshly placed IV; select contralateral deltoid or consult for alternate plan.
  • Document precisely and observe for fluid overload signs given the patient’s CHF risk.
  • Utilize Erikson’s “Integrity vs. Despair” approach — acknowledge the patient’s life context and provide clear, respectful education for consent.

Case 2: A Young Adult with Prior Anaphylaxis to Egg

A 24-year-old seeks influenza vaccination but has a documented history of anaphylaxis to eggs. Your steps:

  • Review vaccine composition and consult the supervising clinician — many modern flu vaccines are egg-free, but verification is required.
  • If proceeding, observe for 30 minutes post-vaccination and ensure emergency medications are available.
  • Document lot number, informed consent, and observation findings in detail.

Case 3: Pediatric Clinic with Student Nurses in Training

Student nurses rotate through a pediatric clinic where IV techs also administer vaccines. Best practices:

  • Use simulated practice for injection technique and communication strategies tailored to each of Erikson’s early stages.
  • Allow student nurses to observe and then perform vaccinations under direct supervision, with immediate, constructive feedback.
  • Ensure student nurses document under the supervising RN’s co-signature until competency is verified.

Final Operational Notes for IV Techs Considering This Expansion

Expanding into immunization administration is an achievable and worthwhile step for many IV technicians. The safety and efficacy of such an expansion rests on structured education, supervised practice, clear authorizations, meticulous documentation, and an interprofessional safety culture that values escalation and continuous learning. Whether you are a student nurse learning your first injections, a practicing nurse supporting IV techs, an anesthesia tech coordinating perioperative vaccinations, a veterinary tech seeking a human-health role, or a dentist integrating vaccines into an oral health practice, the principles outlined here apply: prepare, practice, communicate, and always safeguard the patient.

For further training and resources, consider the programs and reference materials linked throughout this article and the authoritative public health resources maintained by CDC, NIH, and NLM. Professional organizations such as NAPTP and credentialing bodies (e.g., NTA) can provide additional guidance on training standards and competencies.

If your institution is developing an IV-tech immunization program, partner with educational groups such as PCT Institute of Healthcare and Phlebotomy Career Training to establish aligned curricula and competency verification processes.

Ready to Earn Your National IV Certification?

The National IV Association (NIVA) offers nationally recognized certification programs for nurses, EMTs, paramedics, and other licensed healthcare professionals. Train online, test when ready, and earn credentials that employers trust.

For foundational training in healthcare careers, visit the PCT Institute of Healthcare or explore certification options at Phlebotomy Career Training.

Enroll Now →

Categories
Uncategorized

Difficult IV Access: Strategies and Techniques for Challenging Patients

Difficult IV Access: Strategies and Techniques for Challenging Patients

By Nancy Kimmel, MSN, FNP, RN, PhD CHMM, MSN-FNP-BC — National IV Association

Introduction: Why difficult IV access (DIVA) matters to patient safety and clinical practice

Difficult intravenous access (DIVA) is one of the most frequent procedural challenges across inpatient, outpatient, perioperative, emergency, and community settings. Student nurses, nurses, anesthesia techs, veterinary techs, and dentists all encounter patients with challenging vascular access—each with unique procedural and safety implications. Intravenous therapy is a powerful clinical intervention used for blood collection, administration of chemotherapy, immunosuppressants, vitamin therapy, and a wide range of medications and fluids. Because fluids and medications administered intravenously enter the circulation rapidly, any error—whether poor technique, wrong fluid selection, or misplacement—can lead to systemic consequences including infection, tissue necrosis, or rare but catastrophic events such as air embolism and cardiovascular overload. For this reason, IV therapy requires physician authorization and must adhere to strict sterile technique, careful vein selection, and accurate documentation.

Scope and audience

This extended clinical review is written for a broad clinical audience including student nurses, nurses, anesthesia techs, veterinary techs, and dentists who may perform peripheral IV placement, assist with IV medication administration, or be responsible for monitoring venous access. Wherever local regulation or scope-of-practice limits apply, healthcare assistants and medical assistants should consult supervising clinicians or their institutional policies before performing IV tasks.

Foundational physiology and safety considerations

Understanding why IV therapy is powerful — and potentially dangerous — begins with basic physiology. The intravenous route bypasses natural barriers and delivers solutions directly to the bloodstream, which means:

  • Rapid systemic distribution of drugs and fluids (onset in seconds to minutes),
  • Small errors in concentration, rate, or placement can cause systemic toxicity or local tissue injury,
  • Inserted devices provide a direct path for microbes into the vascular system unless sterile technique is rigorously applied.

Always remember: IV therapy must be authorized by a licensed provider, and practitioners must adhere to facility protocols and their professional scope of practice.

Anatomy review and vein selection strategy

Selecting an appropriate vein is the single most important step in successful IV insertion. The ideal peripheral vein is straight, adequately sized for the catheter, palpable, mobile (i.e., not tethered to tendons), and distal to any areas of injury, infection, or previous infiltration. Key anatomic sites include the antecubital fossa (cephalic, basilic, median cubital veins), forearm veins, and dorsal hand veins.

Veins commonly used for peripheral IV access

Vein Anatomic location Pros Cons
Cephalic Radial/lateral side of antecubital fossa and forearm Often large and straight; accessible for pumps May be superficial and move with arm position
Basilic Ulna/medial side of arm Often large, good for ultrasound-guided access Close to nerves, and more movement at elbow; may be uncomfortable
Median cubital Across antecubital fossa Usually prominent and stable for blood draws Not ideal for ambulatory patients due to elbow flexion
Dorsal hand veins Back of hand Easy to visualize and safe for short-term use Prone to infiltration and more painful; avoid if possible in fragile skin

Clinical pearls:

  • Trace the vein for at least an inch (2.5 cm) proximally to ensure continuity and a straight segment for catheter placement.
  • Avoid the hands and lower extremities unless there is no reasonable alternative—especially in patients with diabetes, peripheral vascular disease, or lymphedema, where leg access increases the risk of infection and vascular complications.
  • When selecting a site, consider future therapies: avoid antecubital sites if a central line or dialysis access will be needed in the same limb, and avoid sites with PICC lines or prior axillary node dissection or mastectomy (lymphedema risk).

Layers traversed during IV insertion

An appreciation of the skin and vascular layers improves technique. A peripheral insertion traverses:

  • Epidermis — the outermost layer, provides barrier function;
  • Dermis — contains sensory nerve fibers and small vessels;
  • Hypodermis (subcutaneous tissue) — the fatty layer containing deeper capillaries and loose connective tissue;
  • Venous tunica — the vessel wall (intima, media, adventitia), into which the catheter must be positioned without perforation.

Preparing for insertion: sterile technique and safety checks

Aseptic technique is non-negotiable for minimizing catheter-related bloodstream infections (CRBSIs). Elements of best practice include:

  • Hand hygiene immediately prior to the procedure;
  • Use of appropriate personal protective equipment (gloves, and mask/gown as indicated by local policy);
  • Skin antisepsis with chlorhexidine gluconate (CHG) in alcohol — scrub and allow to dry for at least one minute (1 min) per evidence-based recommendations;
  • Use of sterile dressings and securement devices after placement;
  • Confirming physician authorization for IV therapy and following facility IV orders (solution, rate, medication compatibility).

Always read medication and solution labels carefully. Mistaking normal saline (0.9% NaCl) for another solution (e.g., atropine, lidocaine) can be catastrophic. Saline 0.9% is isotonic and approximates body plasma osmolarity and pH (physiologic pH range approximately 7.35–7.45). Hypertonic solutions draw water into the vascular compartment (useful in specific clinical contexts like cerebral edema but dangerous in heart failure), while hypotonic solutions push fluid into cells and tissues (useful for dehydration but risky for cellular swelling). When drawing blood from an IV line after giving medications, be aware of timing recommendations to avoid contamination of the sample and misinterpretation of results.

Insertion technique: practical, step-by-step guidance

Basic insertion technique remains a core competency for nurses, student nurses, and supportive techs. Key steps and technical tips follow:

  • Position the patient with the selected limb supported and accessible. Explain the procedure and obtain consent when required. Use patient-centered language appropriate to the individual’s developmental stage (see Erikson integration later).
  • Apply a tourniquet proximally to distend veins for visualization and palpation. Note: do not apply tourniquets to a limb that already has an indwelling IV line in place. Do not place tourniquets on limbs with prior lymph node dissections or other contraindications.
  • Palpate and trace the vein for at least an inch to ensure a straight run. Consider warming the limb (warm compress or hand-warming techniques) for 3–5 minutes to improve vein dilation, especially in DIVA patients.
  • Prepare the skin with chlorhexidine; allow at least one minute drying time.
  • Stabilize the vein distal to the insertion site with the non-dominant hand. Stretch the skin slightly to anchor the vein and reduce its mobility.
  • Insert the catheter with the bevel up at an angle of approximately 15–28 degrees. This angle allows entry into the lumen while minimizing the risk of transfixing the posterior vessel wall.
  • Watch for the flashback of blood in the catheter hub or chamber. Once the flashback is visualized, advance the catheter a millimeter or two and then lower the angle to advance the catheter fully into the vessel without puncturing through the opposite wall.
  • If excessive resistance is encountered when flushing (resistance on flush), remove and reassess — you are likely not within the lumen, or the catheter tip may be against the vessel wall.
  • Secure the catheter with sterile dressing, label the site with date/time/gauge, and document the procedure: time, gauge, location, patient response, number of attempts, and any complications observed.

Bevel orientation, angle, and flashback

Bevel up reduces the force required to penetrate the vessel wall and improves tactile feedback. The target entry angle range 15–28 degrees is recommended to balance easy penetration with minimal risk of posterior wall puncture. Watch for flashback—this confirms intraluminal entry. If you see no flashback or the flashback is sluggish, do not forceable advance the catheter. Instead, withdraw slightly, readjust angle, and attempt again. For fragile veins (e.g., elderly skin), consider using a smaller gauge catheter and ultrasound guidance to reduce trauma.

Choosing catheter size and device type

Catheter gauge selection is clinically important—choose the smallest gauge that will accommodate therapy needs to reduce vein trauma and thrombosis risk. A quick reference:

Gauge Common uses Implications
14–16G Major trauma, rapid fluid resuscitation, blood transfusion Large bore; causes significant vessel trauma; reserved for emergencies
18G Blood products, standard IV fluids in stable adults Good balance of flow and vessel preservation
20G Most adult peripheral infusions and routine meds Standard for many adult patients
22–24G Pediatrics, elderly, fragile veins, slow infusions Smaller lumen, slower flow; gentler on veins

When peripheral access is impossible or when therapy requires prolonged venous access or vesicant agents (e.g., many chemotherapy agents), consider escalation to midline catheters, peripherally inserted central catheters (PICC), or tunneled central venous catheters in coordination with the ordering provider and vascular access team.

Advanced strategies for DIVA

Difficult IV access requires a toolbox of techniques and technologies. Effective strategies include:

  • Ultrasound-guided peripheral IV (USGPIV): Use high-frequency linear probes to locate suitable veins that are not visible or palpable. US guidance increases first-stick success in obese patients, those with chronic IV drug use, and oncology patients. Training and competence validation are needed before independent practice.
  • Vein illumination and transillumination devices: These non-invasive devices can be useful in pediatric and dark-skinned patients.
  • Warm compresses/immersion in warm water: Local warming dilates veins and improves chances of success.
  • Use of small-gauge catheters with stabilizing devices to minimize movement and phlebitis risk in fragile veins.
  • Alternative access: intraosseous (IO) access in emergencies, or central venous access for long-term needs.

Medications, fluid types, and drip rate considerations

Clinicians must understand the properties of IV fluids and medications because mismatches in fluid type, concentration, or rate can produce systemic harm.

Basic fluid categories

  • Isotonic (e.g., normal saline 0.9% NaCl): Remains primarily within the vascular space. Useful for volume resuscitation. Normal saline is isotonic and approximately physiologic in its osmolar effects.
  • Hypertonic: Higher osmolarity than plasma; pulls water into the vascular compartment—useful for cerebral edema or severe hyponatremia under close supervision. Risk: volume overload, especially in patients with heart failure.
  • Hypotonic: Lower osmolarity than plasma; shifts fluid into cells and the interstitial space—useful for dehydration with hypernatremia, but can cause cellular swelling and is dangerous in patients with potential increased intracranial pressure.

Drip rates and rapid infusion risks

Rapid infusion in fragile or compromised patients can precipitate cardiovascular overload and respiratory compromise. Signs consistent with fluid overload and decompensation include increased heart rate, elevated blood pressure, shortness of breath, crackles on auscultation, and decreased oxygen saturation (low O2). In extreme cases, rapid volume administration can precipitate pulmonary edema, arrhythmia, or a code blue situation. Always verify orders, ensure appropriate IV access for the prescribed rate, and monitor vulnerable patients closely.

Medication safety

Always read labels. Confusing similar syringes or bags (saline vs atropine vs lidocaine) is a preventable error. When administering IV medications, be mindful of compatibility, infusion rate, dilution, and whether the drug is a vesicant or can cause tissue necrosis if extravasation occurs (e.g., vasopressors, chemotherapy agents).

When drawing blood from a line after infusing a medication, ensure that you have flushed with an appropriate volume and waited the recommended time for that agent to clear the lumen to avoid contamination of specimens. Institutional policies or medication package inserts often provide guidance for dwell times and acceptable sample strategies.

Recognizing and managing complications

Complication awareness is essential for early intervention:

Complication Signs Immediate management
Infiltration Swelling, coolness, blanching, pain at site; decreased or no blood return Stop infusion, remove catheter, elevate limb, apply warm compress if non-vesicant; document and restart elsewhere
Extravasation Pain, burning, swelling, blistering; occurs with vesicant drugs Stop infusion, aspirate residual drug if possible, notify prescriber, follow extravasation protocol including antidotes and plastic surgery consult when necessary
Phlebitis Redness, warmth, tenderness along the vein Remove catheter, apply warm compresses, rotate sites for future access
Air embolism Sudden respiratory distress, hypotension, chest pain Clamp line, place patient in left lateral decubitus and Trendelenburg if tolerated, provide oxygen, call for emergency assistance
Catheter-related bloodstream infection (CRBSI) Fever, chills, erythema at insertion site, unexplained hypotension Remove catheter if indicated, obtain blood cultures per protocol, start antibiotics per prescriber

Clinical note: If you encounter resistance while flushing a recently placed catheter, suspect malposition (e.g., extravascular placement). Never force a flush. Document the event and contact the provider for further orders.

Special populations: pediatric, geriatric, oncology, and diabetic patients

Each population demands tailored strategies.

Geriatric patients

Older adults present unique vascular challenges: fragile, thin skin, decreased subcutaneous tissue, and tortuous veins. Use smaller-gauge catheters when feasible, prepare the skin carefully, and secure devices with gentleness to avoid skin tears. The National Institute on Aging (NIA) and resources from the National Center for Aging and Development (NCAD) emphasize person-centered approaches in geriatric care, including communication strategies, fall-risk assessments, and de-prescribing. When teaching older adults about their IV therapy or monitoring, take into account sensory deficits and mobility limitations. For further geriatric guidance see the NIA website.

(NIA link: National Institute on Aging (NIA))

Pediatric patients

Pediatric veins are smaller, and procedural anxiety is high. Use age-appropriate distraction, local anesthetic options (topical lidocaine-prilocaine creams), and devices such as transillumination. A dedicated pediatric vascular access team or experienced pediatric staff should place difficult catheters.

Oncology patients

Cancer patients often have DIVA due to chemotherapy exposure, repeated access, and fragile veins. Chemotherapy agents may be vesicants—extravasation can cause progressive tissue necrosis. Consider midline or central catheter placement for long-term chemo. When peripheral access is used, follow oncology-specific extravasation protocols and monitor closely.

Diabetics and limb selection

Avoid lower extremity IVs in diabetic patients unless absolutely necessary because peripheral vascular disease and neuropathy increase infection risk. Diabetic neuropathy may also reduce local symptom reporting (e.g., pain) in the presence of infiltration or infection. Prefer forearm or antecubital veins when possible.

Documentation, legal considerations, and professional responsibilities

Charting is not optional; it is both a patient-safety tool and legal protection. Document the time of insertion, catheter gauge and length, site location, number of attempts, patient response, and any immediate complications. Also document the label on the dressing and the authorization provided (e.g., order number or prescriber name).

Understand your scope of practice. Medical assistants and phlebotomy students must consult their supervisor if the situation exceeds their training. Always admit when you lack knowledge rather than attempting a technique beyond your training—this is professional responsibility and protects patients and practitioners alike.

Training, education, and the role of instructors

Teaching IV skills demands more than demonstration—it requires preparation, passion, and patience. Instructors should:

  • Provide clear stepwise instruction combined with supervised hands-on practice;
  • Emphasize safety: sterile technique (chlorhexidine 1-minute scrub), correct angles (15–28 degrees), bevel-up insertion, and verification of flashback;
  • Teach situational judgement: when to escalate to ultrasound-guided access, when to stop attempts, and when to call vascular access or the ordering provider;
  • Manage classroom dynamics by grouping students by skill level, using simulation, and ensuring immediate constructive feedback;
  • Model continuous learning—encourage trainees to consult evidence-based resources and institutional policies, and to pursue certification opportunities (e.g., vascular access certification programs).

Instructor tips for assessment and remediation:

  • Use validated checklists for competency evaluation;
  • Provide deliberate practice opportunities with task trainers and ultrasound phantoms;
  • Incorporate interprofessional education so student nurses, anesthesia techs, veterinary techs, and dentists understand each other’s roles and limitations;
  • Teach documentation practices as part of technical competency to instill the habit of legally defensible record-keeping.

Integrating Erikson’s psychosocial stages into IV teaching and patient education

Erik Erikson’s eight stages of psychosocial development are a valuable framework for tailoring communication and education to patients and learners of different ages and psychosocial needs. Below is a practical mapping of Erikson’s stages to IV-related teaching strategies for clinicians and instructors:

Erikson Stage Age Group Teaching/Communication Strategy
Trust vs. Mistrust Infancy Establish trust with caregivers; use soothing touch, brief explanations, and involve parents in comforting behaviors during IV placement.
Autonomy vs. Shame Toddler/Preschool Offer choices (e.g., which arm), simple explanations, and distraction techniques to support autonomy and reduce shame associated with distress.
Initiative vs. Guilt Early school-age Offer a simple role (e.g., hold bandage), explain procedures, and praise cooperation to encourage initiative.
Industry vs. Inferiority Late school-age Provide age-appropriate explanations, foster competence (e.g., teach child how to hold still), and validate feelings.
Identity vs. Role Confusion Adolescence Respect privacy, explain rationale for procedures in frank terms, and involve adolescents in decision-making about their care.
Intimacy vs. Isolation Young adulthood Address concerns about body image, encourage shared decision-making, and respect autonomy and confidentiality.
Generativity vs. Stagnation Middle adulthood Discuss roles at work/home, consider scheduling to avoid disruption, and engage patients in long-term care planning.
Integrity vs. Despair Older adulthood Use respectful communication, provide clear explanations and reassurance, consider sensory deficits, and allow time for questions. Tie into geriatric resources from NCAD and NIA.

Using Erikson’s stages helps tailor education: for a frail older adult (Integrity vs. Despair), slow, respectful teaching that acknowledges life experience increases cooperation and reduces anxiety. For student nurses and learners, using psychosocial approaches in simulation improves communication skills and patient-centered care.

Interprofessional practice: working with anesthesia, dental, and veterinary teams

Each clinical discipline brings distinct needs and considerations for IV access:

  • Anesthesia techs: often manage IV access in the perioperative period where rapid induction requires reliable access. Communicate intended induction rates and agents (e.g., propofol) to select appropriate gauge and site. Anticipate the need for larger bore access for emergent resuscitation.
  • Dentists: in-office sedation and certain dental surgeries occasionally require IV access for sedative or vasoconstrictor administration. Ensure that office protocols, emergency equipment, and training are in place to manage airway and vascular complications.
  • Veterinary techs: animals present unique anatomic and behavioral challenges. Techniques such as restraint, sedation, and use of specialized veterinary cannulas are standard. Many general access principles (asepsis, gentle securement, and documentation) still apply.

Regardless of setting, student nurses, nurses, anesthesia techs, veterinary techs, and dentists must follow institutional policies, understand medication properties (always read labels), and know when to seek assistance or escalate care.

Troubleshooting checklist for failed attempts

When an insertion fails or the catheter malfunctions, follow a systematic troubleshooting approach:

  • Stop attempting after facility-defined number of attempts to reduce patient harm—this number varies by institution but often ranges from 2–3 attempts by a single operator before escalation;
  • Reassess patient factors (dehydration, vasoconstriction, anxiety) and consider warm compresses or fluids to enhance vein prominence;
  • Consider ultrasound-guided access or consultation with a vascular access team;
  • For an already placed catheter with poor flow or resistance on flush: do not force; check for kinks, reposition the arm, check clamp positions, and aspirate gently; if unresolved, remove and re-site;
  • Document attempts, reasoning, and escalation pathway.

Policies and resources: where to look for evidence-based practice

Clinicians and instructors should consult authoritative guidance and institutional policies for the most current evidence-based practices. Useful resources include:

Practical protocols — sample insertion checklist for pre-procedure and post-procedure

The following checklist can be adapted by clinical educators and institutional committees to standardize practice. It is a sample and not a replacement for institutional policy.

Step Action
Order verification Confirm physician authorization for IV therapy, indication, solution, and rate.
Patient identification Verify identity, allergies, and relevant history (e.g., prior DVTs, dialysis access, mastectomy).
Equipment check Gather catheter of appropriate gauge, gloves, chlorhexidine prep, sterile dressing, saline flush, securement device, and label.
Site preparation Apply tourniquet (not on arms with existing IVs), warm compress if needed, choose vein tracing at least 1 inch, prep skin with chlorhexidine for 1 minute, allow to dry.
Insertion Bevel up, insert at 15–28 degrees, watch for flashback, lower angle and advance catheter, secure, tape and label.
Initial flush and verification Flush gently with saline; no resistance; check for pain, swelling, erythema. If resistance is present, stop and reassess.
Documentation Record time, gauge, site, number of attempts, patient tolerance, dressing label, and any complications.

Teaching and continuous professional development

Clinical competence in vascular access is achieved through deliberate practice, supervision, and reflective learning. Instructors should integrate simulation, evidence review, and competency checklists. Encourage learners to use resources such as institution-specific vascular access policies, the CDC for infection prevention, and specialized training organizations like PCT Institute of Healthcare and Phlebotomy Career Training for foundational skills and certification opportunities.

Putting it together: a practical scenario and stepwise decision-making

Scenario: A 78-year-old patient with congestive heart failure and chronic kidney disease requires IV access for diuretic therapy and blood draws. Veins are fragile and not readily visible.

Decision-making:

  • Assess the need for peripheral vs central access (short-term diuresis can usually be managed via peripheral access, but dialysis patients or those requiring multiple blood draws may need alternative strategies).
  • Choose a forearm vein if available; avoid lower extremities given diabetes or PVD risk; avoid dorsal hand if possible due to fragility.
  • Use warm compress and vein palpation; if veins remain non-palpable, consider ultrasound-guided peripheral IV or consult vascular access team.
  • Select a smaller gauge (e.g., 22G) for fragile veins, and position the limb to prevent kinking. Use securement devices to minimize movement.
  • Document thoroughly and monitor the patient for signs of fluid overload given heart failure—watch for increasing respiratory rate, hypoxemia (low O2), rising blood pressure and heart rate.

Quality improvement and institutional systems

Reducing DIVA-related complications is an institutional priority. Consider implementing:

  • Vascular access teams for complex cases;
  • Mandatory competency and re-certification for IV insertion and ultrasound-guided techniques;
  • Standardized documentation templates that capture number of attempts, catheter gauge, and site;
  • Audit and feedback cycles to monitor insertion success rates and complication incidence;
  • Easy access to evidence-based resources (links to CDC, NIH, NLM, and geriatric resources such as NIA).

Final practical reminders for every clinician

  • IV therapy must have physician authorization and follow facility policy;
  • Use chlorhexidine skin prep and allow a one-minute dry time for best antiseptic effect;
  • Trace veins for at least an inch and avoid hands/legs when possible—especially in diabetics;
  • Insert with bevel up at 15–28 degrees and watch for flashback; do not push too hard or you may perforate the posterior wall;
  • Resistance on flush indicates the catheter is not intravascular—stop and reassess;
  • Always read labels carefully (saline vs atropine vs lidocaine) and be mindful of solution tonicity and drug vesicant properties;
  • Do not apply tourniquets to arms with existing IV lines;
  • Document time, gauge, location, patient response, and any complications as legal protection and patient-safety practice;
  • Admit knowledge limitations and seek assistance when needed—scope-of-practice boundaries protect patients and clinicians.

For clinicians seeking formal training in phlebotomy and IV insertion skills, consider the educational offerings available through specialized training organizations such as PCT Institute of Healthcare and Phlebotomy Career Training. These programs can complement institutional training programs and help prepare student nurses and allied personnel for clinical practice.

Additional evidence-based resources and infection prevention guidance can be found at the CDC, research and clinical guidance via the NIH, literature through the NLM, and geriatric care resources via the NIA. For phlebotomy program accreditation and training standards, consult organizations such as NAPTP and testing guidance via relevant national testing agencies like NTA.

References and further reading

  • Institutional IV therapy policies and vascular access team protocols.
  • CDC guideline for the prevention of intravascular catheter-related infections (CDC).
  • National Institute on Aging resources for geriatric patient-centered care (NIA).
  • Selected training organizations: PCT Institute of Healthcare, Phlebotomy Career Training.

Ready to Earn Your National IV Certification?

The National IV Association (NIVA) offers nationally recognized certification programs for nurses, EMTs, paramedics, and other licensed healthcare professionals. Train online, test when ready, and earn credentials that employers trust.

For foundational training in healthcare careers, visit the PCT Institute of Healthcare or explore certification options at Phlebotomy Career Training.

Enroll Now →

Categories
Uncategorized

Central Venous Catheters vs. Peripheral IV Lines: What Every IV Tech Needs to Know

Central Venous Catheters vs. Peripheral IV Lines: What Every IV Tech Needs to Know

By Nancy Kimmel, MSN, FNP, RN, PhD CHMM, MSN-FNP-BC — an evidence-informed primer for student nurses, nurses, anesthesia techs, veterinary techs, and dentists who place, care for, teach about, or rely on intravascular access. This comprehensive article synthesizes clinical practice, anatomy, physiology, infection prevention, medication safety, and educational strategies so IV technicians and allied professionals can make safe, knowledgeable decisions at the bedside and in the classroom.

Why this matters to you

IV therapy is not “just a stick.” Fluids and medications administered intravascularly circulate systemically within minutes. That speed is a therapeutic advantage and a hazard: an insertion error, medication incompatibility, or breach in sterile technique can rapidly cause systemic infection, tissue necrosis, cardiopulmonary decompensation, or air embolism. That is why student nurses, nurses, anesthesia techs, veterinary techs, and dentists must understand the distinctions between peripheral IV lines and central venous catheters (CVCs), their indications, insertion principles, maintenance, and complication recognition.

Scope and common indications for IV therapy

IV therapy includes blood collection and infusions for:

  • Fluid resuscitation and maintenance (0.9% NaCl, balanced crystalloids)
  • Medication administration: antibiotics, analgesics, antiemetics, vasoactive drugs, atropine, lidocaine, and others
  • Chemotherapy and other vesicants
  • Immunosuppressants and biologics
  • Vitamin therapy and parenteral nutrition

All IV accesses and infusions require physician authorization per institutional policy. For clinicians who insert and manage access, documenting indication, consent, and orders is essential for safety and medicolegal protection.

Anatomy and layers traversed on cannulation

Understanding the tissues a needle crosses improves technique and complication recognition. On peripheral cannulation, the needle crosses:

  • Epidermis — outer keratinized layer; puncture causes initial pain and transient bleeding.
  • Dermis — vascular and innervated connective tissue; contains capillary plexuses.
  • Hypodermis (subcutaneous tissue) — adipose and loose connective tissue; depth varies by patient habitus and age, affecting angle of entry.
  • Venous tunica — the vein wall including tunica intima, tunica media, and tunica adventitia; the successful flashback indicates lumen entry.

Peripheral IV lines (PIVs): essentials

Definition and types

PIVs are short (typically 3/4 to 1.25 inches for adults), peripheral catheters inserted into superficial veins of the upper extremity. Midline catheters and peripherally inserted central catheters (PICCs) may be placed peripherally but behave differently; midlines end in the upper arm and are not central, while PICCs are threaded to a central location and are therefore CVCs.

Common insertion sites and vein selection

Prefer proximal upper extremity veins for diagnostic blood draws and short-term access. Important venues:

  • Antecubital fossa veins: cephalic, basilic, and median cubital — these are robust and allow easier cannulation and successful blood return.
  • Forearm veins: good for longer dwell times; stabilize catheter with securement devices and appropriate dressing.
  • Avoid hand and foot veins unless absolutely necessary — they are smaller, more painful, and have higher rates of dislodgement and phlebitis. Teams should especially avoid lower extremity access in diabetics due to peripheral vascular disease and infection risk.

When palpating a vein, “trace” it for an inch to ensure adequate length for catheter seating and to reduce chance of advance-through (through-and-through puncture).

Insertion technique (peripheral)

  • Angle: 15–28 degrees with the bevel up to enter skin and vein smoothly; decrease angle after flashback to seat the catheter and advance.
  • Watch for flashback: a brisk, free-flowing blood flash in the catheter hub indicates lumen entry. After flashback, advance catheter slightly and then advance catheter over the needle (if using over-the-needle catheter) while maintaining stabilization.
  • Do not push too hard; forcing the needle risks puncturing the posterior wall and causing extravasation or hematoma.
  • After placement, secure catheter, apply appropriate sterile dressing, and flush gently. Resistance during flush indicates the catheter is not intravascular — stop, evaluate, and do not infuse under pressure.

Dwell times and maintenance

PIVs are intended for short-term use — most institutions recommend removal or reassessment at 72–96 hours unless clinically indicated for longer use. Regular site assessments for redness, swelling, pain, and securement integrity are required.

Central Venous Catheters (CVCs): essentials

Types of central venous access

Type Where it terminates Common indications
Non-tunneled CVC Superior vena cava (SVC) Emergency access, vasopressors, central venous pressure monitoring
Tunneled CVC (e.g., Hickman) SVC Long-term chemotherapy, TPN, repeated access
Implanted port SVC via port reservoir Intermittent chemotherapy, long-term access with low infection risk
PICC (Peripherally Inserted Central Catheter) SVC (via basilic/cephalic vein) Prolonged IV antibiotics, TPN, chemotherapy

Indications for central access vs. peripheral

  • Need for high-osmolarity solutions (TPN), vesicant chemotherapy, or long-term antibiotics
  • Central venous pressure monitoring or rapid large-volume resuscitation
  • Poor peripheral venous access (multiple failed attempts)
  • Frequent blood sampling that would cause repeated peripheral sticks

Insertion principles (central)

CVC insertion — whether non-tunneled, tunneled, PICC, or port — is a higher-risk procedure. It requires imaging verification of tip position and often uses ultrasound guidance to reduce mechanical complications such as pneumothorax and arterial puncture. Key safety steps:

  • Maximum sterile barrier precautions: cap, mask, sterile gown, sterile gloves, large sterile drape.
  • Skin antisepsis: chlorhexidine with adequate contact time — scrub for at least 30 seconds and allow drying; many protocols emphasize a minimum of 1 minute of chlorhexidine skin contact for thorough antisepsis prior to insertion and dressing changes.
  • Ultrasound guidance during vessel puncture to visualize needle entry and avoid adjacent structures.
  • Radiographic confirmation of tip location before infusion of incompatible agents; immediate post-procedure chest x-ray to rule out pneumothorax when indicated.

Comparative overview: CVC vs PIV

Feature Peripheral IV Central Venous Catheter
Dwell time Short-term (days) Days to months/years (depends on type)
Insertion complexity Low — bedside, quick High — requires sterile barrier, imaging, trained providers
Permitted infusions Most isotonic meds; avoid vesicants/hyperosmolar solutions Vesicants, hyperosmolar solutions, multiple concurrent infusions
Infection risk Lower but still significant Higher risk of CLABSI; prevention bundles critical
Complications Infiltration, phlebitis, extravasation Pneumothorax, CLABSI, catheter thrombosis, air embolus

Sterile technique and infection prevention

The science behind central line-associated bloodstream infections (CLABSIs) shows that consistent application of evidence-based insertion and maintenance bundles reduces infections. Key elements every IV tech must know:

  • Chlorhexidine skin prep — scrub thoroughly; institutional policies commonly require at least a 30-second scrub with a 1-minute full contact time for maximal antisepsis.
  • Maximal sterile barrier precautions for CVC insertion.
  • Proper dressing and securement: transparent semipermeable dressings or gauze per policy; dressing changes per institutional timeframe or when soiled or loose.
  • Daily assessment of line necessity: remove any line no longer needed to reduce exposure time.
  • Use of alcohol/chlorhexidine caps and appropriate hub disinfection (“scrub the hub” for 15 seconds) prior to access.

For evidence-based guidance visit the CDC central line recommendations: CDC — Bloodstream Infection Guidelines.

Drip rates, fluid types, and physiologic consequences

Fluids are not inert carriers; their tonicity and volume kinetics have physiologic effects that must be matched to patient condition.

Crystalloid categories

Solution Tonicity and effect Clinical pearls
Normal saline (0.9% NaCl) Isotonic; approximates plasma osmolarity. Normal physiologic pH is 7.35–7.45; NS is effectively isotonic though can produce hyperchloremic metabolic acidosis if large volumes given. Safe for initial resuscitation; verify compatibility with meds and patient acid-base status.
Hypertonic saline Hypertonic — pulls fluid into the vascular space from cells and interstitium. Used for cerebral edema or severe hyponatremia correction under controlled conditions; risky in heart failure due to volume overload.
Hypotonic solutions (e.g., 0.45% NaCl) Hypotonic — shifts fluid from vascular space into interstitium and cells. Used for true water deficit; dangerous in patients at risk for cerebral edema or hypovolemia.

Rapid infusion risks

Rapid infusion in fragile patients (elderly, cardiac disease) can precipitate acute decompensation — tachycardia, hypertension, dyspnea, hypoxemia — and progress to pulmonary edema or require emergent resuscitation (code blue scenarios). Monitor vital signs and oxygenation during boluses; use controlled infusion pumps when available.

Medication administration, labeling, and safety

Medication errors during IV therapy are among the most dangerous. Every IV tech must:

  • Always read labels carefully — distinguish saline from atropine, lidocaine, or other look-alike containers. Never assume fluid identity based on bag color or shape.
  • Follow “Five Rights”: right patient, right medication, right dose, right route, right time.
  • Be aware of compatible diluents and maximum concentrations for peripheral vs central administration — some meds are vesicants and require central access.
  • Use appropriately sized syringes for flushing: generally, 10 mL syringes minimize excessive pressure on small-bore catheters that can damage them; smaller syringes can generate dangerously high pressures.
  • Know catheter-specific locking solutions (e.g., heparin lock) and institutional protocols for flushing and locking volumes.

Blood draws and medication timing

A critical practical point: when a line has been used for medication dosing, especially antibiotics or vasoactive drugs, wait an appropriate interval and flush the line thoroughly before drawing blood samples from that lumen to avoid sample contamination and spurious lab values. If sampling for therapeutic drug monitoring, follow institution-specific dwell/flush intervals to avoid erroneous results.

Tourniquet use and lines

Do not apply tourniquets proximal to or over an arm that has an IV line in place. Doing so can increase infusion pressure, risk infiltration, and cause local complications. If venous stasis is required for blood draws, use an alternate limb or follow institutional protocols that may include temporarily pausing infusions and disinfecting the hub prior to sampling.

Complications and what to look for

Peripheral line complications

  • Phlebitis: pain, erythema, warmth along vein — remove catheter if suspected and document.
  • Infiltration/extravasation: swelling, coolness, lack of blood return — stop infusion immediately; vesicant extravasation requires specialized management.
  • Hematoma: occurs with vessel puncture; apply pressure and monitor.

Central line complications

  • CLABSI: fever, chills, positive blood cultures — follow infection control protocols and reporting requirements.
  • Catheter-related thrombosis: swelling of the limb or face, catheter malfunction — manage with imaging and anticoagulation as indicated.
  • Mechanical complications: pneumothorax (decreased breath sounds, hypoxia), arterial puncture (pulsatile blood), air embolus (sudden respiratory distress, chest pain) — emergent response required.

Recognizing an air embolus

Air embolism is preventable with proper technique (clamps, occlusive dressings, patient positioning). Signs include sudden chest pain, dyspnea, hypotension, hypoxia, and neurologic changes. If suspected, lay the patient on left lateral decubitus and trendelenburg, administer high-flow oxygen, and call the emergency response team.

Troubleshooting cannulation and infusion problems

  • No flashback: reposition the angle slightly or withdraw and reattempt at a new site; do not blindly advance.
  • Flashback then resistance: if resistance occurs on flush, do not force fluids; check for kinks, securements, and reposition. If still resistant, consider catheter malposition or extravasation.
  • Blood return absent but infusion flows: evaluate for partial catheter occlusion; perform aspiration attempts per protocol and consult supervisor for management and possible imaging.

Documentation and professional responsibilities

Accurate charting is not optional — it is a legal and patient-safety imperative. Document the following each time you insert, assess, or remove an IV:

  • Time and date of insertion/removal
  • Gauge and length of catheter
  • Exact location (e.g., right forearm, cephalic vein, 10 cm proximal to wrist)
  • Number of attempts and who performed the procedure
  • Patient response, pain score, and complications (hematoma, bleeding, unusual findings)
  • Dressing type and securement used
  • Flush volumes and solutions used (e.g., 10 mL 0.9% NaCl), including any heparin locks

Good documentation protects patients and caregivers alike.

Scope of practice and when to escalate

Know your scope. Medical assistants (MAs), student nurses, and novice techs must consult supervisors for procedures outside their defined scope. If you don’t know an answer, the correct professional action is to stop, ask for help, and document the consultation. Admitting knowledge limits is professional practice and patient safety advocacy.

Special populations: geriatrics and the frail

Older adults present unique challenges: fragile skin, thin subcutaneous tissue, tortuous and fragile veins, comorbid cardiopulmonary disease, and altered fluid distribution. Applying geriatric-informed practice reduces harm.

Practical geriatric adjustments

  • Use smaller gauge catheters when clinically appropriate to reduce vessel trauma.
  • Stabilize fragile skin with gentle adhesives and protective dressings; consider transparent dressings that minimize tape trauma on changes.
  • Anticipate decreased venous reserve — choose proximal veins with good support and use ultrasound guidance when available.
  • Adjust infusion rates conservatively; monitor for signs of fluid overload.

For evidence and resources on aging and geriatric care, consult the National Institute on Aging: NIA and the National Center for Aging and Development (NCAD) for applied geriatric training material.

Teaching patients and learners: integrating Erikson’s psychosocial stages

As an instructor and clinician, I integrate Erikson’s eight stages of psychosocial development into patient and student education. Consider developmental stage when communicating:

  • Trust vs. mistrust (infants): caregivers need simple explanations and reassurance.
  • Autonomy vs. shame (toddlers): provide choices (e.g., “Which arm would you prefer?”) to enhance control.
  • Initiative vs. guilt (preschoolers): use play to explain procedures.
  • Industry vs. inferiority (school-age): explain steps, allow practice with dolls or simulation kits.
  • Identity vs. role confusion (adolescents): address privacy and autonomy; include them in decision-making.
  • Intimacy vs. isolation (young adults): respect independence and encourage informed consent.
  • Generativity vs. stagnation (adults): relate procedures to roles (work, family) and functional outcomes.
  • Integrity vs. despair (older adults): acknowledge life experience, offer dignified explanations, and address fears about loss of autonomy.

For student nurses and educators, teaching techniques that recognize psychosocial context improve consent, cooperation, adherence, and learning retention.

Instructional strategies for IV educators: preparation, passion, patience

Teaching IV skills requires more than technical demonstration. Instructors should embody the following principles:

  • Preparation — have equipment, models, and learning objectives prepped; review institutional policies, infection prevention bundles, and emergency responses (air embolus, extravasation). Include links to reputable resources such as the PCT Institute of Healthcare and Phlebotomy Career Training for supplemental curricula and simulation tools.
  • Passion — modeling professional, evidence-driven enthusiasm motivates student nurses, MAs, and allied techs (anesthesia techs, veterinary techs, and dentists) to adopt best practices.
  • Patience — learners acquire psychomotor skills at different paces. Use deliberate practice, feedback, and competency checklists. Encourage reflection on each attempt.
  • Manage classroom dynamics — set ground rules for patient simulation, ensure psychological safety, and provide tiered challenges from PIV to PICC/central line care.
  • Continuous learning — incorporate current guidelines (CDC, NIH, NLM) into curricula and require learners to demonstrate competence in sterile technique, hub disinfection, and complication recognition.

Teaching tips tied to clinical realities

  • Demonstrate scrub times with visible timers for chlorhexidine prep (simulate the 1-minute contact time).
  • Use ultrasound-guided simulation to teach sono-anatomy for vessels and adjacent structures.
  • Simulate complication scenarios (air embolus, CLABSI, extravasation) and run debriefs to reinforce early recognition and escalation.
  • Emphasize ethical practice: informed consent, documentation, and interprofessional communication — critical for student nurses, nurses, anesthesia techs, veterinary techs, and dentists alike.

Geriatric teaching — resources and integration

When instructing about IV care in older adults, incorporate resources from the National Center for Aging and Development and the National Institute on Aging to frame age-specific physiologic and psychosocial considerations. Consider using case studies of older patients with multimorbidity, and align techniques with goals of care and patient preferences.

Regulatory, professional, and credentialing resources

Continual professional development and adherence to credentialing standards are essential. Useful organizations and resources include:

Clinical pearls every IV tech should memorize

  • 15–28° angle, bevel up for peripheral insertion; reduce angle after flashback.
  • Do not force flush against resistance — catheter may be extravascular or occluded.
  • Chlorhexidine skin prep with appropriate contact/dry time; treat it as non-negotiable.
  • Isotonic 0.9% NaCl matches physiologic pH range (7.35–7.45) and is the most common crystalloid used for flushes and resuscitation.
  • Hypertonic solutions pull fluid into the vascular compartment — useful but dangerous in CHF patients.
  • Hypotonic solutions push fluid into tissues — avoid with risk of cerebral edema.
  • Always read labels — differentiate saline from lidocaine, atropine, or other agents.
  • Document time, gauge, location, number of attempts, patient response — this is legal protection.
  • Do not tourniquet over an arm with an IV; choose alternate limb or follow facility protocols.
  • Student nurses, nurses, anesthesia techs, veterinary techs, and dentists must know when to escalate — consult supervisors when outside your scope.

Practical checklist for safe IV placement and maintenance

  • Verify physician order and indication.
  • Perform hand hygiene and gather supplies.
  • Identify patient and explain procedure appropriate to developmental stage (use Erikson-informed communication).
  • Select vein and trace at least 1 inch to ensure length; avoid hands/legs when possible, especially in diabetics.
  • Apply tourniquet distal to insertion site (not over preexisting IV), palpate vein, cleanse with chlorhexidine for required time, and allow to dry.
  • Insert at 15–28° with bevel up; watch for flashback; reduce angle and advance catheter as appropriate.
  • Secure and dress per policy; flush gently and assess for patency and absence of pain or swelling.
  • Document fully: time, gauge, location, response, dressing, flush volumes.
  • Educate patient and caregivers on signs of complications and when to call for help.

Resources for continued training and certification

For structured educational programs and simulation-based competency development, consider resources such as the PCT Institute of Healthcare and Phlebotomy Career Training. These institutions provide supplemental curricula geared to phlebotomy, peripheral access, and foundational IV skills that complement formal nursing and allied health training.

References and authoritative reading

Primary guidelines and peer-reviewed literature should be consulted for protocol development and for staying current. Start with the CDC lines for prevention bundles (CDC BSI Guidelines), the NIH library resources (NIH / NLM), and geriatric materials from the National Institute on Aging. Professional organizations like NAPTP and NTA publish standards and competence frameworks that are useful for training programs and clinical governance.

Audience-specific notes

Student nurses

Focus on fundamentals — anatomy, sterile technique, patient communication, documentation, and knowing when to call your preceptor. Practice under supervision and use checklists to achieve competency.

Nurses

You are the clinical decision-makers who balance patient needs, vascular access options, and safety. Lead CLABSI prevention, mentor student nurses, and ensure accurate charting for legal protection.

Anesthesia techs

Rapid infusions and emergent vascular access are commonplace in anesthesia. Know the physiologic effects of fluid types and watch for signs of volume overload during rapid boluses.

Veterinary techs

Principles of venous access translate to animal patients, though species-specific anatomy and behavior vary. Sterile technique, dose calculations, and careful monitoring apply in all settings.

Dentists

When IV access is used in dental sedation or emergency settings, ensure you follow institutional standards, use appropriately trained personnel, and coordinate with nurses/anesthesia techs for monitoring and emergency response.

Takeaway (clinical synthesis)

Peripheral IVs and central venous catheters are complementary tools. PIVs are suitable for short-term, low-osmolarity infusions and routine blood draws. CVCs are reserved for high-risk infusions, hemodynamic monitoring, and long-term therapy. Sterile technique, chlorhexidine skin prep (with adequate contact time), correct vein selection, careful insertion technique (15–28° bevel up), and vigilant monitoring for complications are common denominators for safe practice. Documentation, scope-of-practice awareness, and continuous education — guided by principles from the CDC, NIH, NLM, and geriatric resources such as the NIA and NCAD — complete the framework for professional, safe IV therapy.

For further structured learning, explore the PCT Institute of Healthcare and Phlebotomy Career Training links embedded above, and consult regulatory and evidence-based resources from the CDC, NIH, NLM, NIA, NAPTP, and NTA to keep practice current and patient-centered.

Ready to Earn Your National IV Certification?

The National IV Association (NIVA) offers nationally recognized certification programs for nurses, EMTs, paramedics, and other licensed healthcare professionals. Train online, test when ready, and earn credentials that employers trust.

For foundational training in healthcare careers, visit the PCT Institute of Healthcare or explore certification options at Phlebotomy Career Training.

Enroll Now →

Categories
Uncategorized

Blood Transfusions and IV Therapy: Protocols, Safety, and Transfusion Reactions

Intravenous (IV) therapy and blood transfusion are cornerstone interventions across acute care, ambulatory care, perioperative settings, oncology clinics, veterinary practices, and dental surgeries. Whether you’re preparing for the National IV Exam or expanding your clinical knowledge, this guide provides a detailed, evidence-informed reference covering IV insertion, vascular access, infusion therapy, blood transfusion procedures, sterile technique, infusion physiology, transfusion reactions, documentation, and patient-centered teaching strategies. As a clinician-educator, I write specifically for student nurses, nurses, anesthesia techs, veterinary techs, dentists, and phlebotomy students to support safe IV practice and professional development.

In this guide, you’ll learn:

  • When IV therapy and blood transfusions are indicated
  • How to select veins, catheter gauges, and IV fluids for different clinical situations
  • Best practices for peripheral IV insertion, sterile technique, and medication safety
  • How to recognize and respond to transfusion reactions and infusion-related complications
  • Proper documentation, patient monitoring, and blood collection techniques
  • Scope-of-practice responsibilities and patient safety best practices

When is IV Therapy and Blood Collection Needed?

IV infusion, blood bag, and syringe preparation

IV therapy is not limited to fluid rehydration. Common clinical indications include:

  • Intravenous fluid replacement and electrolyte correction, including isotonic (e.g., normal saline), hypotonic, and hypertonic solutions.
  • Blood and blood component transfusion (packed red blood cells, platelets, plasma, cryoprecipitate).
  • Medication delivery—antibiotics, chemotherapeutic agents, immunosuppressants, analgesics, vasoactive infusions, and emergency drugs (e.g., atropine, epinephrine).
  • Chemotherapy and biologic therapies that require controlled infusion rates and central venous access in some cases.
  • Vitamin therapy and parenteral nutrition when enteral routes are inadequate.
  • Phlebotomy for diagnostic testing and therapeutic blood collection.

Critical point: IV therapy and blood product administration require physician (or authorized prescriber) authorization. Before performing IV therapy independently, all personnel—including student nurses, nurses, anesthesia techs, veterinary techs, and dentists—should understand their scope of practice, facility policies, and professional responsibilities. For more information, see the NIVA Code of Ethics and Scope of Practice.

Vascular Anatomy for Safe IV Insertion

When inserting an IV catheter you pass through multiple tissue layers before entering the lumen of a vein. From superficial to deep:
  • Epidermis — skin barrier; primary site for antisepsis.
  • Dermis — contains sensory nerves and capillary plexuses; potential for pain and bleeding.
  • Hypodermis/Subcutaneous tissue — fatty layer; provides mobility but can obscure veins.
  • Venous wall (tunica) — internal endothelial lining is fragile and must be handled with aseptic technique to prevent thrombosis and phlebitis.

Sterile Technique for Safe IV Insertion

IV therapy carries systemic risks because infused fluids and medications bypass cutaneous defenses and rapidly enter the circulation. Errors can cause systemic infections, extravasation leading to tissue necrosis, and even air embolism. Therefore:

  • Use strict aseptic technique for catheter insertion and blood product handling. (Proper sterile technique is one of the most effective ways to reduce catheter-related infections and other IV complications.)
  • Prepare the skin using chlorhexidine when available. A full 30-second to 1-minute friction scrub is recommended by many protocols for central and peripheral access sites—ensure the one-minute cleanse for optimal antisepsis when indicated.
  • Don appropriate personal protective equipment and use sterile gloves for catheter insertion per facility policy.
  • Label IV lines and tubing immediately after setup. Confirm medication names and concentrations by reading the labels aloud with a second clinician when available.

How to Choose the Best Vein for IV Insertion

Diagram of arm veins for IV insertion

The antecubital fossa remains the most accessible site for many phlebotomies and peripheral IVs. The primary superficial veins are the cephalic, basilic, and median cubital veins.

Key practical tips:

  • Trace the vein for at least one inch (2–3 cm) proximally and distally to ensure straight, patent vein length for catheter advancement.
  • Avoid hand veins and lower extremity veins unless clinically necessary—this is especially important in patients with diabetes mellitus where perfusion and healing can be compromised.
  • Consider the patient’s comfort and mobility; avoid placing IVs over joints when possible.

How to Insert a Peripheral IV Catheter

The mechanical steps of venipuncture are deceptively simple but require practice to master. For a complete walkthrough of the procedure, see our step-by-step guide to peripheral IV insertion.

  • Insertion angle: 15–28 degrees relative to the skin surface is the commonly accepted range for peripheral venous cannulation. For tighter, superficial veins, use the lower end of the angle range (15–20°); for deeper or more mobile veins, a slightly steeper angle up to 28° may be needed.
  • Bevel orientation: keep the bevel up to facilitate smooth entry and enable clear flashback visualization.
  • Flashback: observe a flash of blood in the catheter hub as confirmation of venous entry. Once the flashback is visualized, lower the angle slightly and advance only the catheter—not the needle—into the lumen.
  • Do not push too hard. Forceful advancement risks transfixing the vein and causing through-and-through puncture, hematoma, or infiltration.
  • Resistance on flush: if you encounter resistance when flushing the catheter, assume you are not optimally positioned in the vein or that there is a clot/occlusion. Stop and reassess—do not force the flush.

IV Catheter Gauges and Flow Rates Explained

Choosing an appropriate catheter gauge depends on the infusion needs (blood transfusion vs maintenance fluids vs viscous medications) and the patient’s vein size. The table below outlines common peripheral IV catheter sizes and typical uses.

Gauge (G) Internal Diameter & Flow Common Clinical Uses
14 G Very large, high-flow Trauma, massive transfusion, rapid fluid resuscitation
16 G High-flow Major surgery, large-volume transfusion
18 G Moderate-high flow Blood transfusion, contrast administration, many IV medications
20 G Moderate flow General IV fluids, blood draws in adults
22–24 G Small bore Pediatric patients, fragile elderly veins, slow infusions

Clinicians must balance the need for higher flow (e.g., for transfusion) against the risks of inserting large-bore catheters in fragile veins (common in elderly patients). When transfusing blood, an 18–20G peripheral IV is typically preferred for adults to minimize hemolysis and permit appropriate flow rates.

Types of IV Fluids: Isotonic, Hypotonic, and Hypertonic

Understanding the osmolarity and physiologic targets of IV fluids is essential for safe therapy. For a more detailed discussion of fluid selection and tonicity, see our guide to Types of IV Fluids: Isotonic, Hypotonic, and Hypertonic Solutions Explained.

  • Normal saline (0.9% NaCl) is isotonic. It closely matches extracellular osmolarity and is pH neutral relative to blood (blood pH 7.35–7.45). It remains within the vascular and interstitial compartments without significant osmotic shifts. Many resuscitation and blood administration protocols use normal saline as the carrier fluid.
  • Hypertonic solutions (e.g., 3% NaCl, hypertonic saline) pull water from the intracellular compartment into the vascular space and can reduce cellular edema. They are useful in specific scenarios (e.g., cerebral edema) but can precipitate volume overload and osmolar shifts—use cautiously in patients with heart failure.
  • Hypotonic solutions (e.g., 0.45% NaCl) promote movement of water into cells and interstitial space. They can treat dehydration due to hyperosmolar states but risk cellular swelling; avoid in patients at risk for increased intracranial pressure or with unstable hemodynamics.

IV Infusion Rates, Monitoring, and Patient Safety

Drip rates and infusion speed directly impact patient safety. Rapid infusion in fragile patients may precipitate cardiovascular overload and decompensation.

Key signs of infusion-related overload include:

  • Increased heart rate (tachycardia)
  • Elevated blood pressure
  • Acute shortness of breath and tachypnea
  • Decreased oxygen saturation (SpO2)
  • Jugular venous distension and pulmonary crackles on auscultation

Two critical transfusion-related overload syndromes:

  • TACO (Transfusion-Associated Circulatory Overload): due to rapid or excessive transfusion resulting in volume overload. Treat by stopping the infusion, providing oxygen, administering diuretics as indicated, and contacting the prescriber.
  • TRALI (Transfusion-Related Acute Lung Injury): immune-mediated lung injury associated with transfusion; presents with acute hypoxemia and bilateral pulmonary infiltrates. It requires immediate cessation of the transfusion and advanced respiratory support.

Clinicians should also be familiar with the early signs of IV complications, including phlebitis, infiltration, extravasation, catheter-related infections, and air embolism. Our guide to Recognizing and Managing IV Complications explores these complications in greater detail.

Common Blood Transfusion Reactions and How to Respond

Blood transfusions can provoke a spectrum of reactions. Prompt recognition and action are essential to minimize morbidity and mortality. The table below summarizes common transfusion reactions, their typical onset, and immediate management steps.

Reaction Typical Presentation Immediate Management
Acute Hemolytic Transfusion Reaction (AHTR) Fever, chills, flank pain, hemoglobinuria, hypotension, oliguria/anuria; occurs minutes to hours after transfusion begins. Stop transfusion, maintain IV line with normal saline, notify the blood bank and prescriber, obtain labs (bilirubin, hemoglobin, haptoglobin, direct antiglobulin test), and send the remaining blood and tubing to the blood bank.
Febrile Non-Hemolytic Reaction Fever and chills during or within hours of transfusion, often in patients with previous transfusions. Stop or slow the transfusion depending on severity, administer antipyretics, notify the blood bank, and consider leukoreduced products for future transfusions if reactions recur.
Allergic Reaction Urticaria, itching, flushing; severe cases may progress to bronchospasm or anaphylaxis. Stop the transfusion for anything beyond mild urticaria. Administer antihistamines for mild reactions. For anaphylaxis, give IM/IV epinephrine, provide airway support, and follow ACLS/anaphylaxis protocols.
Bacterial Contamination/Sepsis High fever, rigors, hypotension, and septic shock occurring minutes to hours after transfusion. Stop the transfusion, obtain blood cultures from the patient and blood bag, start broad-spectrum antibiotics, provide aggressive fluid resuscitation, and notify the blood bank and infection control.
TRALI Acute hypoxemia within 6 hours, bilateral pulmonary infiltrates, and no evidence of circulatory overload. Stop the transfusion, provide respiratory support (oxygen or ventilation), notify the blood bank, and provide supportive critical care.
TACO Dyspnea, hypoxemia, hypertension, and pulmonary edema, typically within 6 hours of transfusion. Stop the transfusion, sit the patient upright, administer oxygen and prescribed diuretics, monitor vital signs, and consider slower infusion rates or split units for future transfusions.
Air Embolism Sudden dyspnea, chest pain, hypotension, or neurologic changes during or immediately after IV line manipulation. Clamp the tubing, place the patient in the left lateral Trendelenburg position if possible, administer oxygen, activate the emergency response team, and ensure all IV connections remain secure to prevent recurrence.

IV Medication Safety and Label Verification

Healthcare professional administering IV fluids

Medication errors involving IV lines can have systemic consequences because the drug enters circulation directly. Always:

  • Read labels carefully—distinguish saline from medications such as atropine, lidocaine, dopamine, or chemotherapeutic agents. Verbalize the drug and dose when preparing to administer (two-person verification when required).
  • Confirm drug compatibility before adding medications to IV lines or piggybacks. Use compatibility charts and pharmacy consultation for central lines and continuous infusions.
  • Wait the appropriate dwell or clearance time before drawing blood from a line that has been used for medication infusion. Facility policies vary, but many require flushing the line with saline and waiting 2–5 minutes (or a specified volume/time) to avoid sample contamination—always follow your institution’s drawn-sample protocol.
  • Do not use tourniquets on arms with active IV lines or blood transfusions—tourniquets can alter local pressure, encourage infiltration, and compromise collection quality.

How to Draw Blood from Patients with an IV

Phlebotomy in the presence of IV infusions requires extra attention:

  • Whenever possible, draw blood from a site opposite the active IV. If the contralateral arm is not available, consider distal sites below the IV after stopping the infusion and flushing according to policy.
  • Document the time the infusion was stopped, the volume of saline flush used, and the interval before blood sampling. This detail is part of quality control and helps the laboratory interpret results.
  • For students and MAs, if you are outside your scope of practice, consult or defer to a supervisor. MAs must consult supervisory staff per facility policy before drawing from lines or altering infusions.

IV Therapy Documentation and Legal Responsibilities

Thorough charting is essential for patient safety and legal protection. Record:

  • Time and date of IV insertion or blood transfusion start and stop.
  • Gauge and type of catheter, exact insertion site (e.g., left antecubital, cephalic vein), number of attempts, and patient response to procedure.
  • Medication names, doses, infusion rates, and any flush volumes used.
  • Any adverse events, transfusion reactions, and actions taken including notifications, lab draws, and blood bank communications.

If you lack knowledge or experience to perform a task safely, admit that limitation and seek assistance. This is not only ethical but protects patients and your professional license. Student nurses, MAs, and allied personnel should always operate within their defined scope of practice and institutional policy. Learn more in the NIVA Code of Ethics and Scope of Practice.

Blood Transfusion Protocols and Laboratory Coordination

Nurse administering IV therapy to an older patient

Blood product administration requires coordinated steps between the clinical team and the blood bank:

  • Pre-transfusion checks: patient identification (two identifiers), product check (unit number, blood type, expiration), and baseline vital signs within the required window (often within 30 minutes) prior to starting transfusion.
  • Initial transfusion rate: many facilities begin transfusions at a slower rate for the first 15 minutes (e.g., 1–2 mL/kg/hr, or a specified mL/hr per protocol) while closely monitoring for reactions. If no reaction, escalate to the ordered rate.
  • Monitoring: document vitals at baseline, 15 minutes, 30 minutes, 1 hour, and at completion—or per facility policy and clinical status.
  • Post-reaction laboratory steps: if a reaction is suspected, obtain required labs (urine for hemoglobin, direct antiglobulin test, post-transfusion CBC, blood cultures) and send them to the lab per the transfusion service protocol.

Special Considerations for Geriatric Patients

Older adults present unique vascular and physiologic challenges. The National Center for Aging and Development (NCAD) and the NIA provide guidance emphasizing:

  • Fragile, tortuous veins with decreased subcutaneous tissue require smaller gauges (22–24 G) in many cases and careful stabilization of the catheter.
  • transfusion strategies and slower infusion rates may be appropriate.
  • Polypharmacy and altered pharmacokinetics alter responses to IV medications; consult medication reconciliation and pharmacy for dosing adjustments.
  • Always consider comorbidities (e.g., CHF, renal impairment) when planning fluid and transfusion therapy; involve interdisciplinary geriatrics or palliative services if appropriate.

For evidence-based guidance on caring for older adults, medication safety, and patient communication, clinicians can refer to the National Institute on Aging (NIA), which provides resources for healthcare professionals and patient education.

How to Manage Blood Transfusion Reactions

If a transfusion reaction is suspected, act immediately:

  1. Stop the transfusion immediately, but maintain IV access with normal saline using a new tubing set to preserve venous access for medications and emergency treatment.
  2. Assess the patient using the ABC approach (Airway, Breathing, Circulation) and provide oxygen or airway support as required.
  3. Notify the appropriate personnel, including the prescriber, blood bank, and transfusion service without delay.
  4. Follow facility protocols for post-reaction investigations, including collection of appropriate laboratory specimens (e.g., post-reaction CBC, DAT, repeat crossmatch, blood cultures) and return the implicated blood product and tubing to the blood bank.
  5. Document thoroughly, including:
    • Time of reaction
    • Signs and symptoms
    • Vital signs
    • Interventions performed
    • Communication with the prescriber, blood bank, and senior clinicians

Preventing IV Therapy and Blood Transfusion Complications

Preventing IV and transfusion-related complications requires a combination of standardized processes, clinical vigilance, and ongoing education.

Best practices include:

  • Standardize patient identification procedures and two-person verification for blood products and high-risk medications.
  • Use barcode scanning for patient identification and blood products whenever available.
  • Follow evidence-based line care, dressing changes, and infection prevention bundles.
  • Provide regular competency training and simulation exercises covering transfusion reactions, IV complications, and emergency response.

IV Therapy Scope of Practice and Professional Responsibilities

Healthcare team in an IV therapy training lab

Every healthcare professional has a responsibility to practice safely within their education, training, and legal scope of practice.

Student nurses should always work under appropriate supervision, while medical assistants and other allied health professionals must consult a supervisor before performing procedures outside their approved competencies.

As a healthcare professional, you should always:

  • Know your institution’s policies and your legal scope of practice.
  • Recognize your limitations and seek supervision whenever necessary.
  • Document accurately and completely, including:
    • Time of procedure
    • Catheter gauge
    • Insertion site
    • Patient response
    • Education provided
  • Participate in multidisciplinary communication and escalation pathways when infusion or transfusion complications occur.

Quality Improvement, Reporting, and Continuing Education

Maintaining competency in IV therapy and blood transfusion requires ongoing education and continuous quality improvement.

Healthcare professionals should:

  • Report adverse events according to institutional and national reporting requirements.
  • Participate in regular competency assessments and simulation training.
  • Stay current with guidance published by the CDC, NIH, NLM, and other recognised professional organisations.
  • Consider joining professional organizations such as the National Association of Phlebotomy and Transfusion Professionals (NAPTP) to support continuing education, professional development, and networking.

Practical Checklists for Bedside Clinicians and Students

Before the procedure:

  • Verify the order and clinical indication.
  • Obtain consent where required.
  • Assemble equipment and check expiration dates.
  • Perform hand hygiene and prepare the insertion site appropriately.
  • Select the correct vein and catheter gauge.

During the procedure:

  • Insert the catheter using the appropriate angle and technique.
  • Confirm flashback before advancing the catheter.
  • Secure and label all tubing and dressings.
  • Monitor the patient closely throughout the infusion or transfusion.

If a transfusion reaction occurs:

  • Stop the transfusion immediately.
  • Keep the IV line open with new saline tubing.
  • Notify the blood bank and prescriber.
  • Collect required laboratory specimens.
  • Document all findings and interventions.

Clinical Resources and Further Reading

Continue building your knowledge with evidence-based guidance and professional training from trusted organisations.

Clinical Guidance

  • CDC: Infection prevention, surveillance, and patient safety.
  • NIH: Clinical research and evidence-based healthcare resources.
  • NLM: Medical literature and research databases.
  • NIA: Older adult care, medication safety, and patient education.

Professional Education

Key Takeaways for Practitioners and Learners

Safe IV therapy and blood transfusion practice depends on a combination of technical proficiency, clinical judgement, and effective communication.

Healthcare professionals should always:

  • Follow aseptic technique and infection prevention protocols.
  • Select the appropriate catheter gauge and infusion rate.
  • Verify medications and blood products before administration.
  • Recognise and respond rapidly to transfusion reactions.
  • Document procedures thoroughly.
  • Practice within their legal scope while seeking supervision whenever necessary.
  • Prioritise patient safety, teamwork, and continuous professional development.

Continue Your IV Education

Whether you’re beginning your healthcare career, preparing for certification, or expanding your teaching credentials, ongoing education is essential to safe, evidence-based patient care.

Explore additional training and professional development through the National IV Association, or build your clinical skills with PCT Institute of Healthcare and Phlebotomy Career Training, offering certification-focused courses, hands-on education, and curriculum resources for aspiring and experienced healthcare professionals alike.

Categories
Uncategorized

How to Start Your Own IV Business by Becoming a Certified IV Instructor

For healthcare professionals who already love the clinical side of intravenous therapy, there is a natural next step that very few people stop to consider: turning your IV expertise into a business of your own. Becoming a certified IV instructor through the National I.V. Association (NIVA) does far more than add a credential to your resume. It gives you a teachable, marketable skill, a nationally recognized certification, and the independence to contract your services across hospitals, convalescent homes, extended care facilities, community colleges, and private training programs. In other words, it gives you the foundation to become your own boss.

If you have ever thought about stepping out of a single staff role and building something that belongs to you, the instructor pathway is one of the most direct routes in all of healthcare to get there.

From Skilled Practitioner to Professional Educator

An IV instructor is a clinician who not only knows how to start, manage, and discontinue an intravenous line but is also trained and certified to teach others to do it safely. That distinction matters. There is a meaningful difference between performing a clinical skill well and being able to break that skill into teachable steps, explain the reasoning behind each one, and guide a roomful of nervous beginners until the technique becomes second nature for them.

By the time someone becomes a NIVA instructor, they already know how to insert IVs and they are already nationally certified to do so. That is because the IV technician certification, along with all of its study material, is built directly into the instructor program. You are never asked to arrive with the clinical credential already in hand. The pathway is designed to take a capable healthcare professional and carry them all the way through to a fully credentialed teaching role.

The Two-Part Pathway, and Two National Exams

One of the things that makes the NIVA instructor route so practical is its structure. It is delivered as two complete courses, with two separate national examinations, so you build your clinical foundation first and then build your teaching foundation on top of it.

The first part is a full course dedicated to becoming nationally IV certified. It covers the clinical fundamentals: how to insert and remove an IV, how to inject fluids and electrolytes, how to manage drip medications, how to handle pediatric infusions, and the safety precautions that protect both the patient and the provider. After completing this coursework, you sit for the National I.V. Examination and earn your technician certification.

The second part is an entire course devoted to teaching itself. This is where you learn the didactic principles of instruction: how to build a syllabus, how to structure a lesson, how to read the needs of your students, and how to handle the difficult or struggling learner with patience and skill. The NIVA instructor course is 100 percent online and self-paced, and it spans 14 modules focused on real education technique, including recognizing student needs, teaching learners with learning disabilities, and the foundations of learning theory. When you finish, you take the National I.V. Instructor Certification Examination. A passing score of 78 percent or higher earns you a hardcopy certificate mailed to you, a hand-sewn patch, and a national ID that employers can use to verify your credential.

You also receive instructor attachments such as quizzes and PowerPoint presentations to help you teach and train from day one, so you are not starting your classroom from a blank page.

Why This Credential Is a Business Launchpad

Here is where the opportunity opens up. Most certifications qualify you to be hired. The IV instructor certification qualifies you to hire yourself.

Once you hold the credential, you can offer your services as an independent instructor to the very organizations that need this training the most. Hospitals need staff trained and retrained on safe IV technique. Convalescent homes and extended care facilities need qualified people to demonstrate IV starts and keep their teams current. Community colleges and post-secondary medical programs often bring in certified instructors to teach IV therapy classes. Each of those is a potential client, and each of them values a teacher who arrives already credentialed, already organized, and ready to run a class.

Because you are nationally certified rather than tied to a single employer, you control how, where, and how often you work. You can teach one contract or twenty. You can build a roster of facilities that call you back every quarter. You can grow this from a side income into a full practice on your own timeline.

Business Models You Can Build

The instructor certification is flexible enough to support several different business models, and many successful instructors blend more than one:

Independent contract instruction. Offer your services on a per-class or per-diem basis to hospitals, long term care facilities, and clinics that need IV training delivered on site. You set your rate, you set your schedule.

Your own IV training class or program. With a syllabus, a curriculum, and the teaching materials already in your toolkit, you are well positioned to launch your own IV therapy course and enroll your own students.

Mobile and on-site training. Bring the classroom to the facility. Many employers would rather pay a qualified instructor to come to them than send staff away for days at a time.

Continuing education and refresher training. IV skills require upkeep, and facilities are always looking for someone to keep their teams sharp and compliant.

The common thread is independence. The certification gives you a credential that travels with you, not one that belongs to a single workplace.

What You Can Earn

The earning potential is one of the strongest reasons to pursue this path. According to figures cited by Salary.com, certified IV training instructors can earn up to $124,000 per year working for healthcare organizations and educational institutions. The reported average sits around $105,643, with many instructors earning up to $118,263 annually. Compare that to a Level 1 registered nurse at roughly $67,190, and the value of the credential becomes clear.

When you operate independently rather than as a single salaried employee, your income is shaped by how many contracts and classes you choose to take on, which means your ceiling is largely in your own hands.

How to Get Started

The National I.V. Association was formed in 1990 to standardize accepted practice and promote patient safety in venipuncture and IV therapy, and it remains a leading certifying authority in the field. Getting started is straightforward:

  1. Register online for the IV Instructor Certification program, which includes the National I.V. Review course, the National I.V. Examination, and the National Instructor course at no additional cost for the included exam access.
  2. Complete the clinical coursework and pass the National I.V. Examination.
  3. Complete the 14-module instructor course and pass the National I.V. Instructor Certification Examination with a score of 78 percent or higher.
  4. Receive your certificate, hand-sewn patch, and national ID, and begin marketing your services.

Keep in mind that NIVA certifications are renewed every two years, which keeps your credential current and your skills sharp, exactly the kind of ongoing standard that facilities want to see in the instructors they hire.

Build Something That Belongs to You

Becoming a certified IV instructor is one of the few moves in healthcare that hands you both a respected credential and a genuine path to independence. You already have the clinical instinct. NIVA gives you the teaching skill, the national certification, and the professional standing to turn that instinct into a business you own.

Invest in your future today. Register for the National I.V. Instructor Certification program and start building a career, and a business, on your own terms. To learn more or to enroll, visit nationalivassociation.org/register or call NIVA toll free at 1-866-926-5792, and one of our certification specialists will be glad to help.