The Ultimate Guide to IV Therapy Certification
IV therapy certification guide: Learn how structured education, supervised skills practice, infection prevention, scope-of-practice awareness, and competency assessment support responsible vascular-access practice.
By Nancy Kimmel, MSN, FNP, RN, PhD CHMM, MSN-FNP-BC
Why IV Therapy Certification Matters
IV therapy certification helps eligible healthcare professionals build the knowledge, supervised technical skills, and safety habits needed for vascular-access responsibilities within their role. Requirements vary by profession, jurisdiction, employer, and procedure, so completing a course does not by itself expand a clinician's legal scope of practice.
This guide reviews core concepts including anatomy, infection prevention, complications, documentation, competency assessment, and continuing education while emphasizing current orders, facility policy, manufacturer instructions, and appropriate clinical supervision.
What This IV Therapy Certification Guide Covers
This IV therapy certification guide is an educational overview for clinicians, learners, and instructors. It covers indications, anatomy and vein selection, supervised catheter-insertion skills, aseptic practice, fluid and medication principles, complication recognition, documentation, scope-of-practice considerations, special populations, teaching strategies, and competency maintenance.
Always use current institutional policies and authoritative clinical guidance for patient-specific decisions.
Core Indications for IV Therapy
Common indications for IV therapy include:
- Blood collection and laboratory sampling
- Administration of chemotherapy and immunosuppressants, with required authorization and strict protocols
- Rapid and controlled fluid resuscitation for dehydration or hypotension
- Continuous infusion of medications such as antibiotics, analgesics, antiemetics, and vasoactive agents
- Vitamin therapy and parenteral nutrition
Physician authorization is required for many IV treatments, particularly chemotherapy and immunosuppressants, because of dosing complexity and risk. Always confirm orders, verify allergies and indications, and follow facility policy and scope of practice before initiating IV therapy.
Anatomy for IV Therapy Certification
Understanding the skin and vascular anatomy is essential for safe IV insertion. The needle and catheter traverse several layers:
Practical mastery of anatomical landmarks and superficial veins supports appropriate selection of catheter length, gauge, and insertion angle and helps reduce complications.
Vein Selection for IV Certification
Vein selection is an essential skill. The antecubital fossa veins, including the cephalic, basilic, and median cubital veins, are often large and stable and are therefore commonly used for initial IV access or blood draws. Trace the vein for at least one inch to confirm direction and stability before puncture.
Avoid selecting veins on the dorsum of the hand or lower extremities unless clinically necessary. These sites can be less comfortable and more prone to complications, and some patient populations require additional caution.
Specific Considerations
- Prefer the nondominant arm when feasible to preserve function.
- Avoid arms with existing AV fistulas, dialysis grafts, or lymphedema.
- In elderly patients, veins are fragile; select supported veins and use smaller-gauge catheters when appropriate.
Tracing and Assessing the Vein
Vein assessment should be performed using the technique taught in supervised training and required by the organization. Site selection should account for the intended therapy, vessel condition, patient factors, device characteristics, and local policy.
IV Therapy Certification Skills: Insertion Technique and Clinical Principles
A standardized approach supports consistency and reduces complications. The following reflects the existing educational content of this article and should be applied only within supervised training, current orders, facility policy, and professional scope.
Preparation
- Confirm the physician order and indications; verify patient identity and allergies.
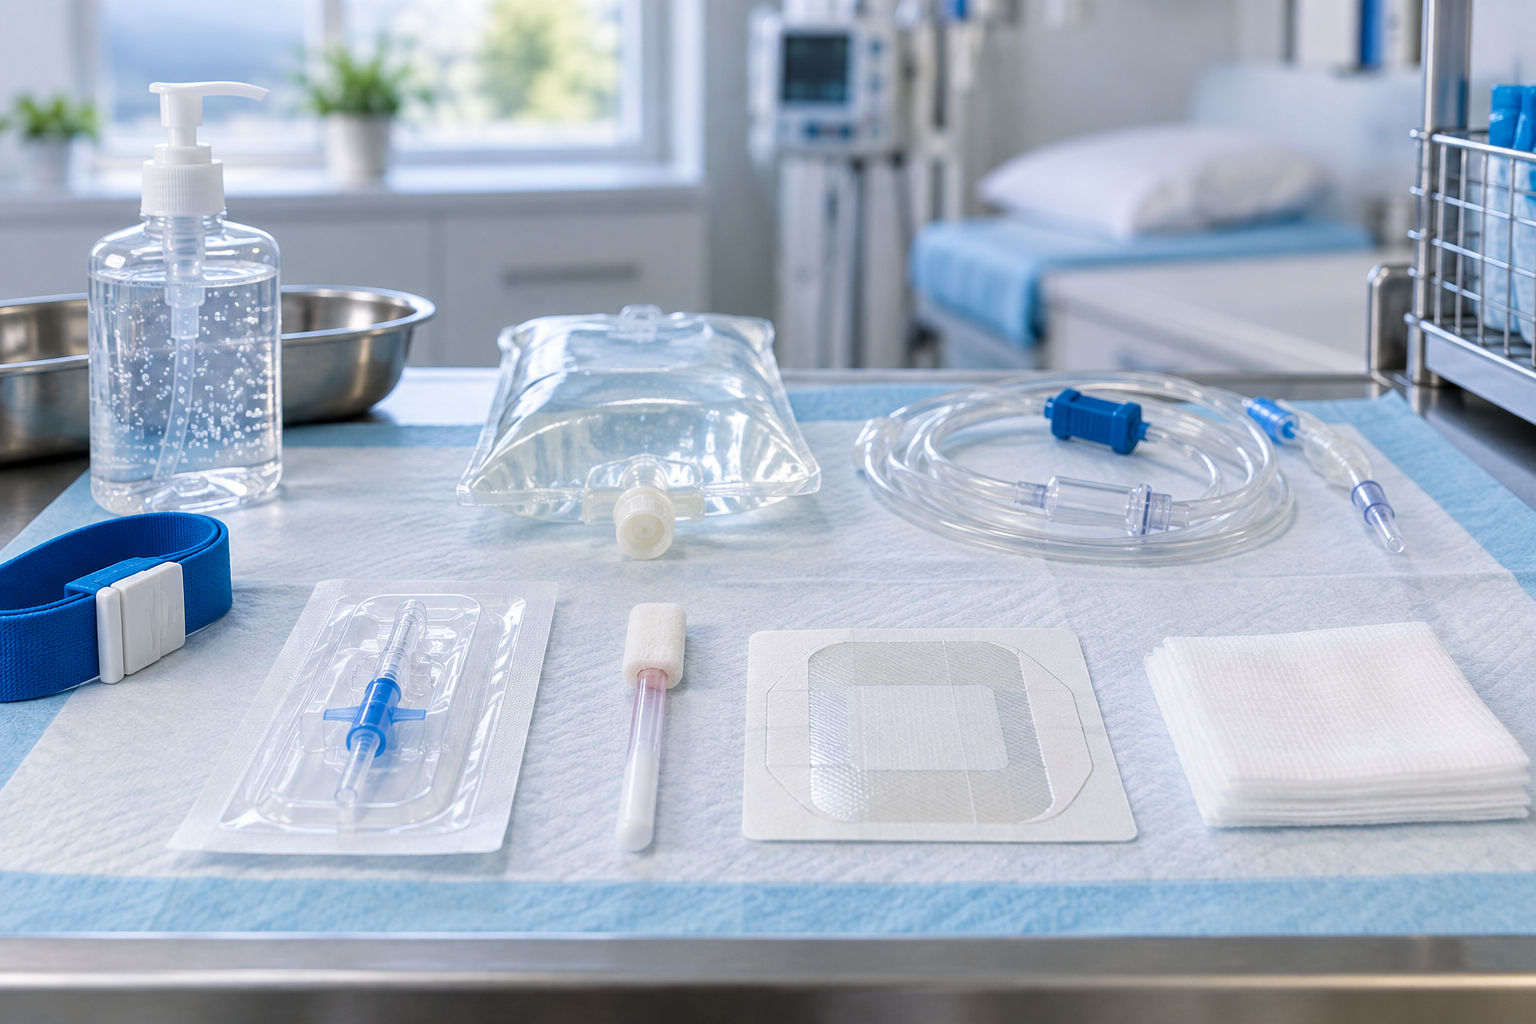
- Gather supplies and check expiration dates, including the cannula, tourniquet, antiseptic prep, gloves, dressing, gauze, flushing solution, and securement device.
- Explain the procedure to the patient and obtain informed consent when required.
Skin Antisepsis
Aseptic technique and proper skin preparation are essential. The CDC's intravascular-catheter recommendations advise preparing clean skin with an appropriate antiseptic before peripheral venous catheter insertion and allowing the antiseptic to dry according to the manufacturer's recommendation. Product choice, application method, allergy considerations, and special population precautions should follow current policy and product labeling.
Insertion Angle and Needle Orientation
Peripheral cannulation is generally performed using a shallow, controlled approach, but the exact angle and advancement technique depend on the device, patient anatomy, operator training, and local protocol. The NCBI Bookshelf review on peripheral line placement describes landmark-guided insertion at a shallow angle and emphasizes controlled advancement rather than force.
Verification and Securing
- After catheter advancement and needle removal, follow the prescribed flushing protocol to confirm patency. If resistance is encountered, stop and reassess according to current policy.
- Secure the catheter with an appropriate dressing. Transparent semipermeable dressings allow visualization of the insertion site.
Equipment: Gauges, Catheters, and Choosing the Right Device
Selection of gauge and catheter depends on the clinical need, including transfusion, blood sampling, infusion characteristics, and expected duration of therapy.
| Gauge | Typical Uses |
|---|---|
| 14–16G | Trauma, rapid blood transfusion, major surgery |
| 18G | Large-bore fluids, blood transfusions |
| 20G | General IV therapy, most adult infusions |
| 22G | Pediatric, elderly, fragile veins |
| 24G | Neonates, very fragile veins, prolonged infusion with low flow rates |
IV Therapy Certification and Infection Prevention
Infection prevention is central to professional practice. The existing article emphasizes skin antisepsis, full drying, aseptic non-touch technique for catheter and hub manipulations, dressing changes according to facility protocols, and patient education on signs of infection.
Ready to move from learning to testing?
If you are ready to take the National IV Exam, continue directly to NIVA's dedicated exam registration page.
Complications: Recognition, Immediate Actions, and Prevention
The article identifies major IV-therapy complications including extravasation or infiltration, phlebitis, catheter-related bloodstream infection, thrombosis, tissue injury with certain medications, and other device-related complications. Recognition and escalation should follow the relevant clinical protocol rather than a generic web article.
Air Embolism
Air can enter the venous system during catheter insertion, line changes, or improper connection. The current article describes sudden dyspnea, chest pain, hypotension, and cardiovascular collapse as concerning signs. If an air embolism is suspected, stop the infusion, prevent further air entry when safe, activate the organization's emergency response process, and follow the applicable protocol and authorized clinician direction.
Extravasation and Tissue Injury
Certain vesicant medications can cause serious tissue injury if they leak outside the vein. Suspected extravasation requires a medication-specific, organization-approved response pathway. For antineoplastic agents, the current ONS/ASCO guideline on antineoplastic extravasation provides an evidence-based specialty reference for management considerations.
Infiltration vs. Phlebitis
Infiltration
Leakage of non-vesicant fluid into surrounding tissue. Signs described in the article include swelling, pallor, coolness, and decreased or absent IV flow.
Phlebitis
Inflammation of the vein. Signs described include erythema, warmth, tenderness, and a palpable cord.
For both, follow current policy for stopping the infusion, catheter management, site care, escalation, and documentation.
Fluid Principles in IV Therapy Certification
IV fluids affect intravascular and interstitial volumes based on tonicity. Understanding these effects is part of safe clinical decision-making.
| Fluid Type | Osmolar / Effect | Clinical Uses Listed in the Article |
|---|---|---|
| Isotonic (e.g., 0.9% NaCl / Normal Saline) | Maintains vascular volume; osmolarity approximates plasma | Resuscitation, fluid maintenance when electrolytes are stable |
| Hypertonic (e.g., 3% NaCl) | Pulls water into vascular space from cells | Cerebral edema and hyponatremia, with caution |
| Hypotonic (e.g., 0.45% NaCl) | Shifts water into cells and interstitial space | Cellular dehydration and hypernatremia, with care |
The article notes that 0.9% sodium chloride is commonly classified as an isotonic crystalloid, while also cautioning that osmolarity, tonicity, electrolyte composition, acid-base effects, and patient-specific risks should not be oversimplified. Fluid choice should match the clinical problem and current orders, with appropriate monitoring.
Drip Rates, Infusion Pumps, and Medication Safety
Infusion rates should be prescribed and verified. The article emphasizes close monitoring for signs of volume overload and the use of infusion pumps for critical infusions where accurate flow rates and alarms are important.
Medication Safety Points from the Existing Article
- Read labels carefully and verify medication name, concentration, and expiration date.
- Double-check high-risk medications with a second clinician when required by policy.
- Follow recommended administration timing and flushing protocols for IV medications.
- Follow approved timing and sampling procedures when drawing blood after medication administration.
- Do not apply a tourniquet proximal to an active IV line when this would conflict with safe practice or facility policy.
Drawing Blood Near an Active IV or Infusion
Blood collection near an active infusion can alter specimen results through dilution or contamination. The WHO Guidelines on Drawing Blood advise against collecting blood from an existing peripheral venous access site in hospitalized patients because IV fluid and medication can affect results. When a standard venipuncture site is not available, follow the organization's laboratory-approved procedure for site selection, infusion management, timing, discard requirements, and documentation.
Charting and Professional Responsibilities
Complete and timely documentation is a legal and professional responsibility. The article identifies documentation elements such as insertion or discontinuation time, catheter gauge and length, anatomical location, number of attempts, patient tolerance, medications infused, patient response, complications, interventions, and escalation of care.
Photography should only be used through an approved clinical workflow that protects patient privacy and complies with consent and recordkeeping requirements.
Medical assistants, pharmacy technicians, students, and other personnel must know the limits of their role and seek supervision or licensed-practitioner guidance when needed.
Scope of Practice and Legal Considerations
Scope of practice varies by profession, jurisdiction, licensure status, employer policy, delegation rules, education, and demonstrated competence. NIVA certification should not be treated as independently creating legal authority to perform an IV procedure.
Other professions should use the current regulator or licensing authority that applies to their role and jurisdiction. Employer privileges and facility policy may be more restrictive than a professional license or certification.
Geriatric Considerations: Skin Fragility and Older Adults
Older adults can experience age-related skin and vascular changes that may affect assessment, securement, bruising risk, and device selection. The National Institute on Aging's Skin Care and Aging resource notes that aging skin becomes thinner and that blood vessels become more fragile.
- Select the device and site based on the patient's vessel condition, therapy, and current policy.
- Use gentle stabilization and approved securement methods for fragile skin.
- Avoid unnecessary heat or adhesive trauma to fragile skin.
- Monitor fluid status carefully when age-related comorbidities increase overload risk.
- Document baseline skin condition and reassess the site according to policy.
Teaching IV Therapy Certification: Preparation, Passion, and Patience
The article describes effective instruction as a combination of evidence-based technique, psychomotor skill development, clinical reasoning, risk management, and supportive teaching behaviors.
Preparation
Create detailed lesson plans, prepare supplies, and use standardized checklists and competency rubrics.
Passion
Model calm confidence, professionalism, and a visible commitment to safe practice.
Patience
Allow repeated practice, debriefing, reflective learning, and immediate feedback.
Psychological Safety
Build learning environments where students can acknowledge uncertainty, ask questions, and discuss errors constructively.
Managing Classroom and Clinical Dynamics
Classroom management can include staged skill stations, simulation with task trainers, progressive complexity, mentorship, and structured review of performance.
Continuous Learning and Faculty Development
IV therapy practice evolves as devices, infection-prevention strategies, and medications change. Faculty and learners should continue reviewing current guidance from public health organizations and professional associations.
Integrating Erikson's Psychosocial Theory into Teaching and Patient Care
Erikson's stages of psychosocial development are presented in the article as a framework for adapting communication and patient education to developmental needs.
Applying Erikson's Stages to Clinical Interactions
- Trust vs. Mistrust: for infants, use parental presence and age-appropriate soothing strategies.
- Autonomy vs. Shame: offer safe, limited choices to toddlers where appropriate.
- Initiative vs. Guilt: use simple explanations and play-based approaches for preschoolers.
- Industry vs. Inferiority: help school-age children understand equipment and participate safely.
- Identity vs. Role Confusion: respect privacy and involve adolescents in appropriate decision-making.
- Intimacy / Generativity: consider social roles and responsibilities for adults.
- Ego Integrity vs. Despair: acknowledge life experience and patient values when caring for older adults.
IV Therapy Certification Pathways and Exam Preparation
IV therapy certification and competency requirements vary by profession, state, employer, accrediting body, and clinical activity. Programs may combine didactic learning, simulation, supervised practice, and demonstrated competency.
- Master basic anatomy and vein-selection concepts.
- Build insertion skill through supervised simulated practice.
- Understand fluid physiology, infection control, medication compatibility, and emergency-response concepts.
- Practice thorough charting and legal documentation.
- Prepare for written knowledge testing and skills-based competency assessment where required.
Third-party training and certification programs may supplement employer-based competency verification. Learners should verify that any program aligns with their professional role, employer requirements, and applicable regulations.
Special Considerations for Veterinary and Dental Clinicians
Veterinary technicians and dental clinicians can face distinct IV-therapy requirements. Veterinary patients involve species-specific anatomy and dosing considerations, while dental clinicians who administer IV sedation may be subject to specific sedation, airway-management, emergency-preparedness, and licensure requirements.
Practical Tips: Troubleshooting Common Problems
- No flashback? Reassess angle and depth rather than forcing advancement.
- Resistance on flush? Stop and reassess; do not force fluid under pressure.
- Frequent dislodgement? Review securement and dressing technique and use approved protective measures where appropriate.
- Bleeding at the insertion site? Apply appropriate pressure, reassess risk factors, and follow local policy.
Documentation Template
The article recommends a standardized documentation template for continuity of care. Suggested fields include:
Evidence-Based Clinical Resources
Strong outbound links should take the reader to the exact guideline, review, or regulatory resource that supports the surrounding topic—not merely to an organization's home page. The following links are used as clinical, regulatory, or evidence references in this guide.
Related training/certification links: These are not being used as clinical evidence. They are included only where readers may want information about related training or certification pathways.
Clinical Scenarios and Case-Based Learning
The original article uses case-based learning to help trainees consolidate knowledge. These examples are educational and should be interpreted through current protocols, supervision, and facility policy.
Case 1: Rapid Fluid Resuscitation in an Elderly Patient
An older adult receiving IV fluid develops increasing respiratory distress, crackles, and reduced oxygen saturation. The article's teaching points include stopping the infusion, escalating care, obtaining immediate authorized clinical assessment, and documenting the event and interventions.
Case 2: Vesicant Chemotherapy in a Peripheral IV
A patient receiving chemotherapy develops burning, pain, blanching, and localized swelling at the IV site. The article emphasizes stopping the infusion, following the organization's extravasation protocol, notifying the oncology team, and documenting the event. Catheter management may depend on the specific protocol and medication.
Maintaining IV Therapy Competency: Continuing Education and Recertification
Maintaining competency can involve periodic re-evaluation, supervised practice, simulation, knowledge testing, review of updated policies and guidance, and documented remediation where performance gaps are identified.
Employer and certifying-body requirements vary. Learners should verify the specific renewal and competency requirements that apply to their role rather than assuming one universal schedule.
Final Practical Tips for Student Nurses, Nurses, Anesthesia Techs, Veterinary Techs, and Dentists
- Verify orders and indications rather than assuming.
- Use a safety-first mindset, including sterile technique, correct labeling, and appropriate double-checks.
- Know when to ask for help and disclose knowledge gaps.
- Maintain clear, precise documentation.
- Use simulation, supervised practice, and mentorship to build technical and clinical judgment.
- Stay current with authoritative guidance and relevant professional resources.
Throughout the certification journey, patient-centered communication and appropriate developmental and geriatric considerations can help support respectful, individualized care.
Frequently Asked Questions About IV Therapy Certification
What is IV therapy certification?
IV therapy certification is structured education and competency assessment related to vascular-access knowledge and skills. The exact meaning and legal effect depend on the profession, jurisdiction, employer, and certifying organization.
Does an IV therapy certification course expand scope of practice?
No course alone automatically expands a professional's legal scope. Learners must verify applicable law, licensure rules, employer privileges, delegation requirements, and procedure-specific policies before performing IV therapy.
What should a strong IV therapy certification program include?
Look for current evidence-based instruction, qualified faculty, supervised simulation or skills practice, objective competency assessment, infection-prevention content, complication recognition, documentation, and clear alignment with the learner's role.
How is IV therapy competency maintained?
Maintenance commonly includes continuing education, supervised practice, periodic skills validation, review of updated policies and guidelines, and documented remediation when a performance gap is identified.
Where can I register for the National IV Exam?
If you are ready to take the exam, continue to NIVA's National IV Exam registration page .
References and Additional Reading
These links point to the specific guideline, review, regulatory framework, or evidence page relevant to the topic cited in this article.
- CDC — Summary of Recommendations: Guidelines for the Prevention of Intravascular Catheter-Related Infections
- CDC — Strategies for Prevention of Catheter-Related Infections
- OSHA — Bloodborne Pathogens and Needlestick Prevention Standards
- NCBI Bookshelf — Peripheral Line Placement
- PubMed — Peripheral Intravenous Catheter Non-Infectious Complications: Systematic Review and Meta-Analysis
- PubMed — ONS/ASCO Guideline on the Management of Antineoplastic Extravasation
- NCBI Bookshelf — Crystalloid Solutions in Intravenous Fluid Therapy
- World Health Organization — Guidelines on Drawing Blood: Best Practices in Phlebotomy
- PubMed — Effect of Intravenous Infusions on Laboratory Results in Blood Specimens
- NCSBN — Scope of Practice Decision-Making Framework
- NCSBN — Nurse Practice Act Toolkit
- National Institute on Aging — Skin Care and Aging
Related Training and Certification Resources
- PCT Institute of Healthcare — IV Technician Certification
- NAPTP — Phlebotomy Technician National Exam
Related-provider links are included for navigation only and are not used as independent clinical evidence for the statements in this guide.
Appendix: Quick Reference — Do's and Don'ts
| Do | Don't |
|---|---|
| Use an approved skin antiseptic and allow it to dry according to manufacturer instructions. | Skip sterile preparation because of time pressure. |
| Use the technique taught in supervised competency training and required by facility policy. | Push forcefully if resistance is felt on flush. |
| Trace the vein before puncture as taught in supervised training. | Use a vein you cannot adequately assess or stabilize. |
| Document time, gauge, location, and patient response. | Leave a partial or incomplete record undocumented. |
| Stop and escalate at the first sign of extravasation or systemic compromise according to protocol. | Continue infusing despite significant burning, swelling, severe pain, or respiratory distress. |
Resources for Clinical Instructors
Instructors developing IV therapy curricula should consider integrating:
- Structured learning objectives with cognitive, psychomotor, and affective components
- Competency checklists aligned with facility policy
- Simulation scenarios that include emergency and complication recognition
- Assessment tools that include reflective practice and quality improvement
- Interprofessional learning opportunities with relevant clinical disciplines
The article also emphasizes preparation, passion, patience, and supervised learning opportunities that help learners build competence safely.
Further Reading and Continuing Education
Maintain a curated reading list built from direct sources such as the CDC's intravascular-catheter guidance, PubMed-indexed reviews, NCBI Bookshelf clinical references, NCSBN regulatory resources, WHO phlebotomy guidance, the NIA's aging resources, and specialty guidelines relevant to the learner's clinical area. When citing evidence, link to the exact guideline or article rather than an organization's general home page.
Ready to Take the National IV Exam?
Continue directly to NIVA's dedicated exam registration page. If you want structured preparation first, the IV Technician Review Course is available separately.